Related Experiment Video
Updated: Feb 10, 2026
Stereotactic Radiosurgery for Gynecologic Cancer
Published on: April 17, 2012
Hypertrophic olivary degeneration mimicking tumor recurrence after brainstem radiosurgery: A diagnostic pitfall in
Iván Andrés Freire-Figueroa1, Pablo Alfredo Vargas-Ardila1, Isabella Castaño-Rodríguez2
1Department of Neurosurgery, Hospital Militar Central, Bogotá, Colombia.

Background:
Hypertrophic olivary degeneration (HOD) is a rare trans-synaptic degeneration of the inferior olivary nucleus resulting from disruption of the dentato-rubro-olivary pathway, also known as the Guillain- Mollaret triangle. Unlike most degenerative processes, it produces olivary hypertrophy rather than atrophy. In oncology patients with prior posterior fossa or brainstem involvement, this condition can simulate tumor recurrence or radiation necrosis, leading to unnecessary interventions if unrecognized.
Case Description:
A 38-year-old woman with a history of human epidermal growth factor receptor 2-positive invasive ductal carcinoma of the breast and previously treated brainstem metastasis presented with progressive right facial paresthesias and gait instability. Neurological examination revealed dysmetria, impaired rapid alternating movements, and gait ataxia without motor or sensory deficits. Magnetic resonance imaging (MRI) demonstrated a nodular enhancing pontine lesion due to the treated metastatic lesion and a new enlargement involving the rostral aspect of the left central tegmental tract with associated hypertrophic change of the inferior olivary nucleus, consistent with unilateral HOD. Magnetic resonance spectroscopy and perfusion imaging excluded neoplastic recurrence. A multidisciplinary neuro-oncology board concluded that the findings were secondary to radiation-induced tract injury. The patient continued maintenance chemotherapy and received symptomatic management and rehabilitative therapy, with serial MRI showing stability.
Conclusion:
HOD should be considered in patients with prior brainstem surgery or radiotherapy who develop delayed cerebellar signs and characteristic MRI findings. Recognizing its benign and self-limited nature is crucial to prevent misdiagnosis as tumor recurrence and avoid unnecessary oncologic or surgical interventions. Integration of advanced MRI techniques and multidisciplinary evaluation allows precise diagnosis and tailored management, ensuring appropriate treatment and long-term follow-up.
More Related Videos
 06:15
Tumor Treating Field Therapy in Combination with Bevacizumab for the Treatment of Recurrent Glioblastoma
Published on: October 27, 2014
 06:33
Construction of a Preclinical Multimodality Phantom Using Tissue-mimicking Materials for Quality Assurance in Tumor Size Measurement
Published on: July 29, 2013
Related Concept Videos
 01:19
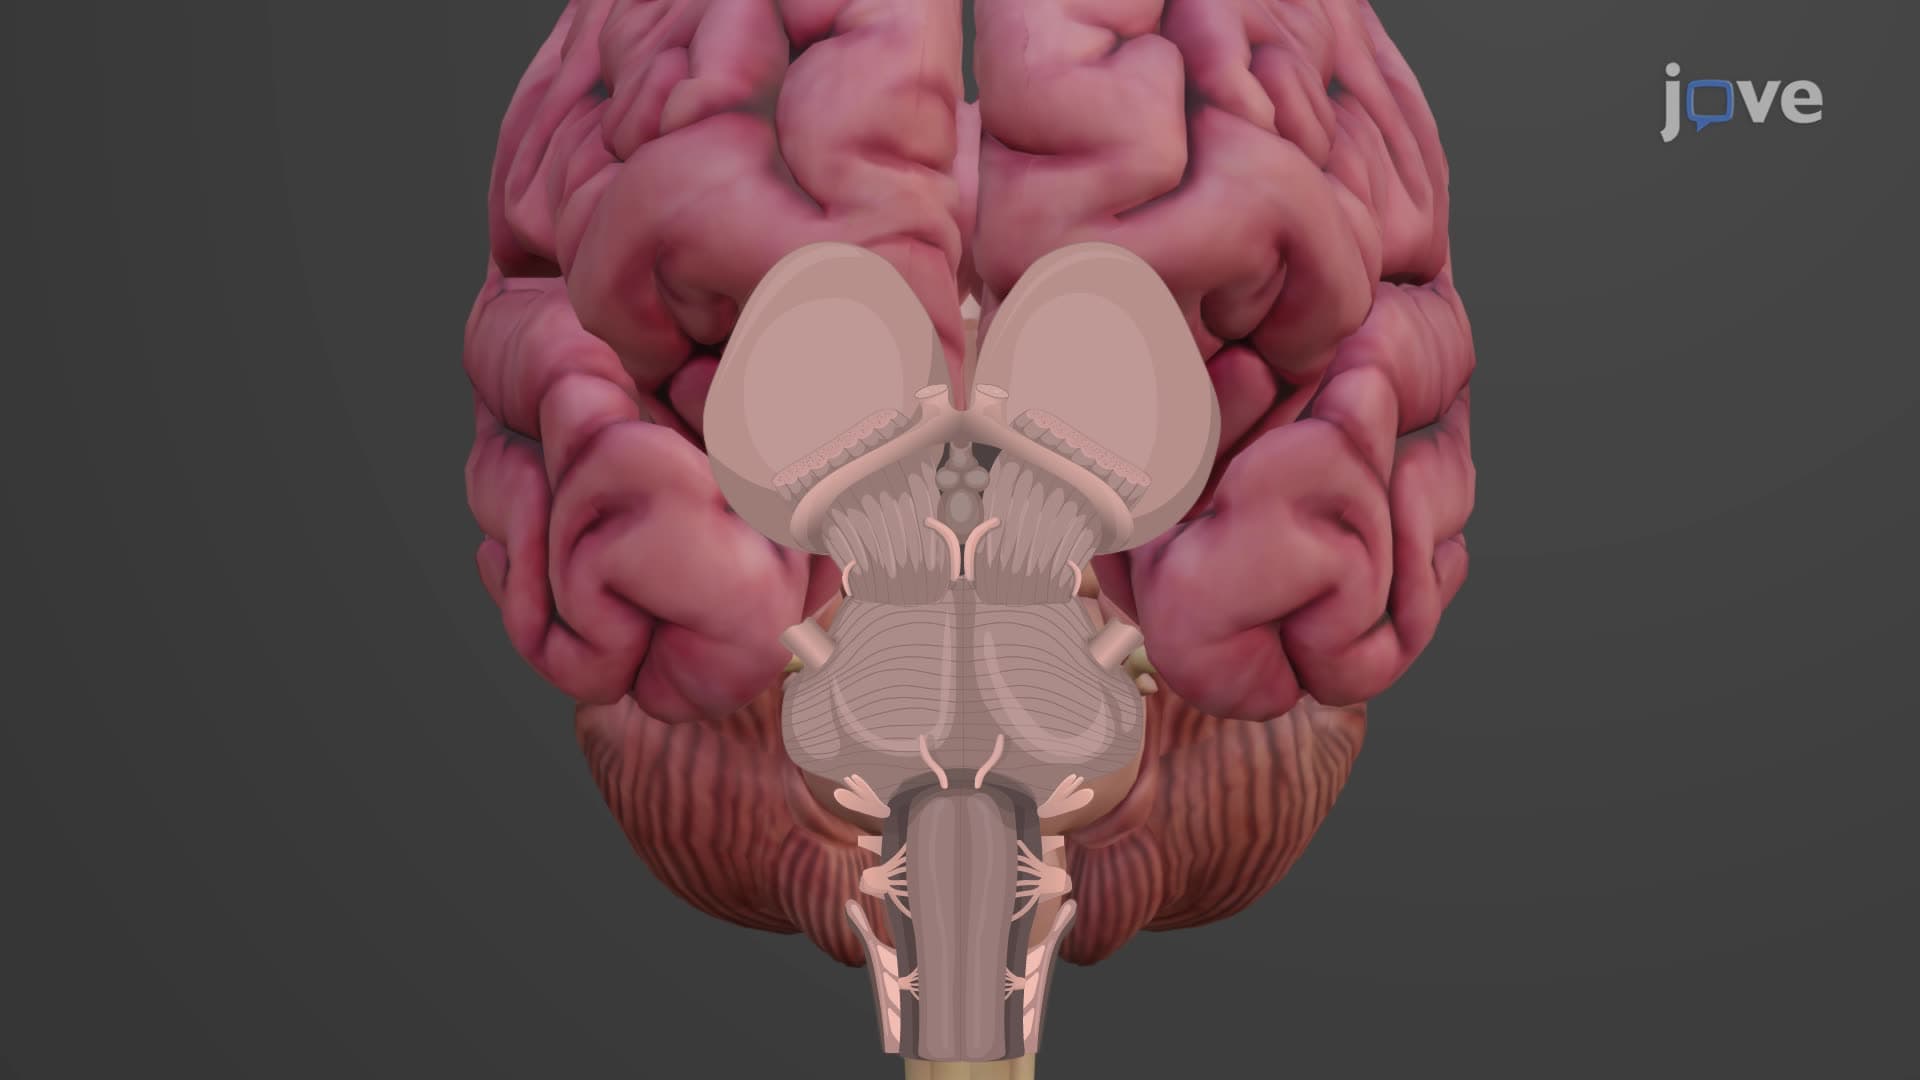
Brainstem
The Midbrain
The midbrain is located beneath the diencephalon and connects the cerebrum with the lower parts of the brain. The cerebral peduncles are prominent midbrain structures that house the...
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:21
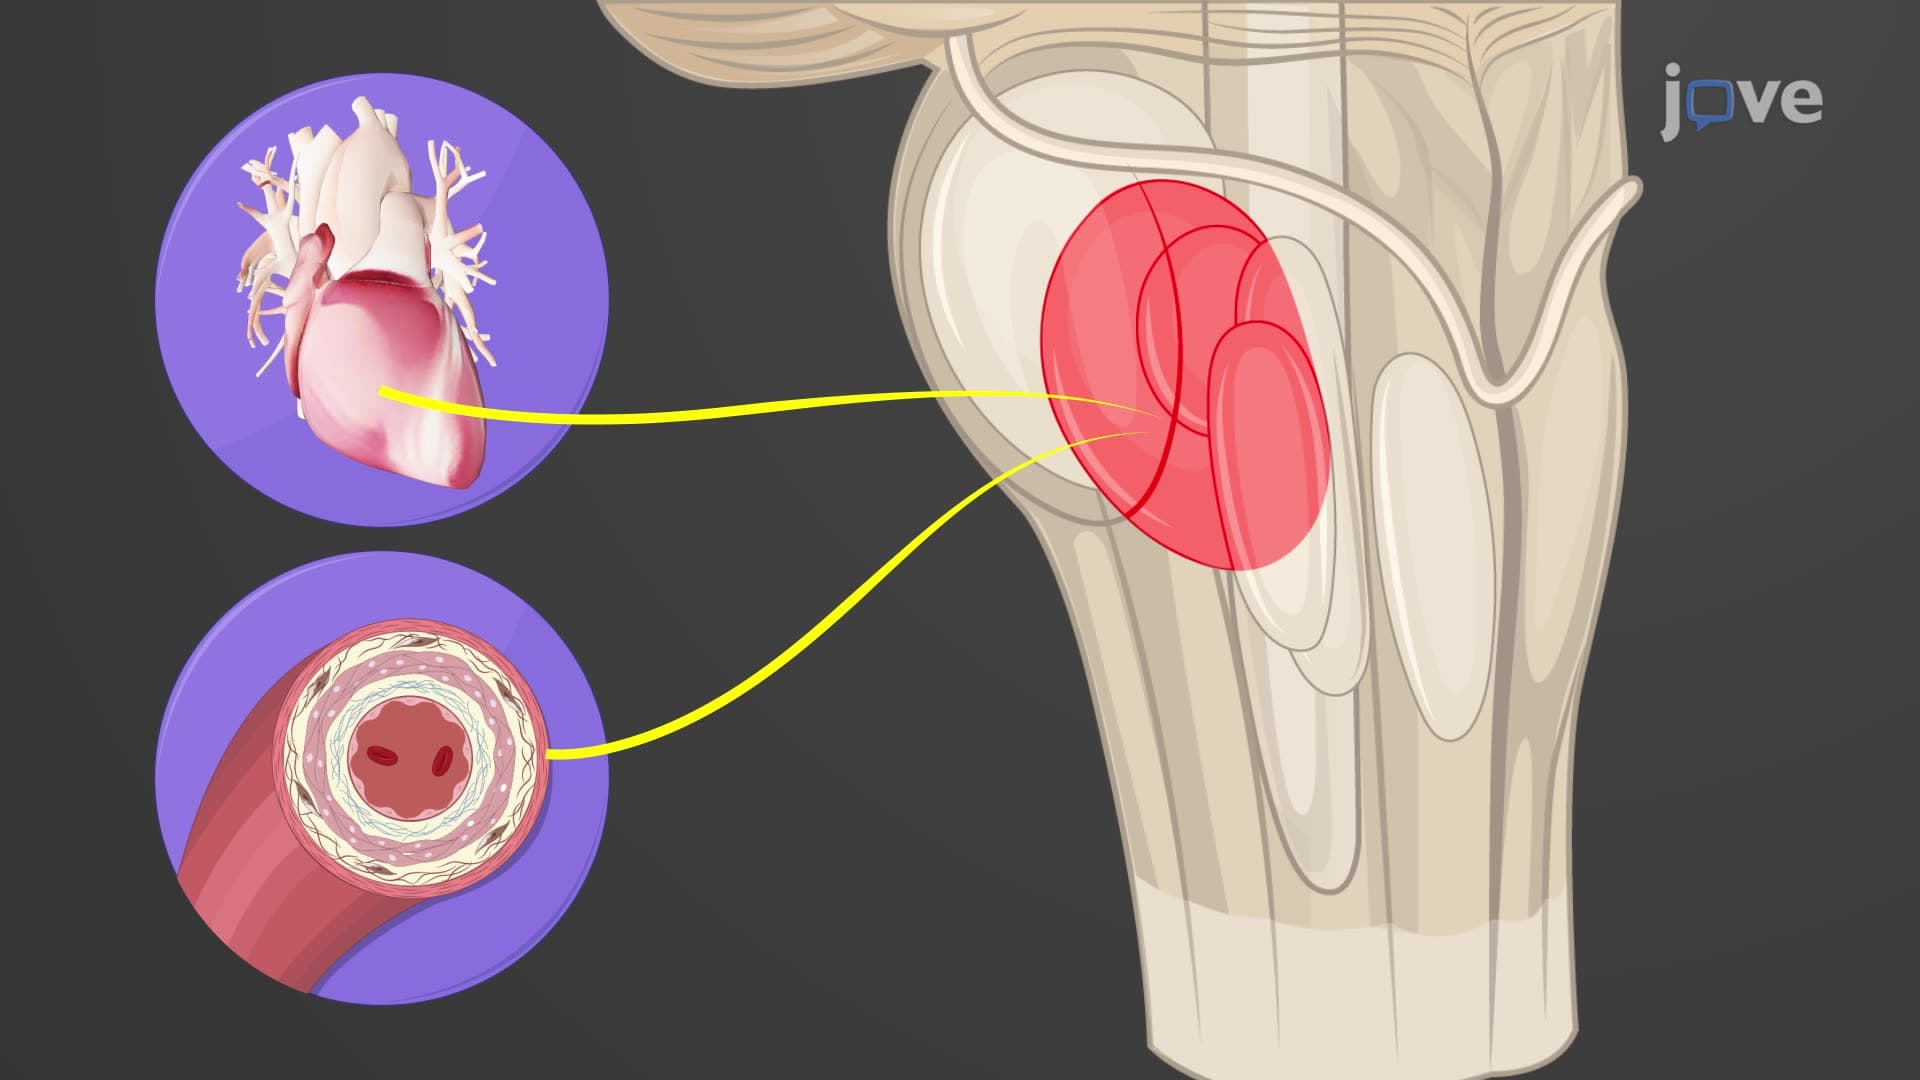
Brainstem: Control Centers of Medulla
Olivary Nucleus
The olivary nucleus, or inferior olivary nucleus, is located within the ventrolateral part of the medulla oblongata. It is primarily involved in motor coordination and motor learning. The olivary nucleus receives input from the spinal cord, cerebellum, and motor...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes: