Related Experiment Video
Updated: Feb 11, 2026

Mouse Model of Surgically-induced Endometriosis by Auto-transplantation of Uterine Tissue
Published on: January 6, 2012
Vulvar Necrosis Following Uterine Artery Embolisation for Uterine Fibroid Treatment: A Case Report and Literature
Hesham Mahmoud1, Doaa Mohammed2, Iheoma Amaechi3
1Obstetrics and Gynaecology, Medway Maritime Hospital, Gillingham, GBR.

Uterine artery embolisation (UAE) is a recognised minimally invasive treatment for symptomatic uterine fibroids, with a generally favourable safety profile. Although post-embolisation complications are well documented, vulvar necrosis is exceptionally rare. We report the case of a 50-year-old woman of Black African heritage who developed severe vulvar symptoms eight days after UAE was undertaken for symptomatic multiple fibroids. She presented with intense vulvar pain, swelling, erythema, ulceration, and right-sided gluteal skin changes, alongside numbness in the lateral right leg. Examination revealed ulceration and sloughing of the right vulva, with progression to gluteal necrosis over seven days. CT and MRI imaging demonstrated inflammatory changes and infarction of the subcutaneous fat in the right buttock, consistent with non-target embolisation. Multidisciplinary assessment concluded that the findings were due to extravasation of embolic material into the gluteal region. The patient received broad-spectrum intravenous antibiotics, neuropathic pain management, and multidisciplinary care involving gynaecology, surgery, interventional radiology, pain management, neurology, and tissue viability teams. She underwent surgical debridement of the necrotic vulvar tissue, achieving full healing. The gluteal necrosis was managed conservatively with spontaneous resolution. At three-month follow-up, she was asymptomatic from a gynaecological perspective; at two years, she was diagnosed with right leg pain syndrome, possibly piriformis-related. Vulvar necrosis following UAE is an exceptionally rare but clinically significant complication. This case highlights the need for early recognition of post-procedural vulvar or gluteal changes and rapid multidisciplinary intervention to optimise outcomes. Increased reporting of such cases may help clarify risk factors, refine preventive strategies, and guide management.
Uterine artery embolisation (UAE) is a recognised minimally invasive treatment for symptomatic uterine fibroids, with a generally favourable safety profile. Although post-embolisation complications are well documented, vulvar necrosis is exceptionally rare. We report the case of a 50-year-old woman of Black African heritage who developed severe vulvar symptoms eight days after UAE was undertaken for symptomatic multiple fibroids. She presented with intense vulvar pain, swelling, erythema, ulceration, and right-sided gluteal skin changes, alongside numbness in the lateral right leg. Examination revealed ulceration and sloughing of the right vulva, with progression to gluteal necrosis over seven days. CT and MRI imaging demonstrated inflammatory changes and infarction of the subcutaneous fat in the right buttock, consistent with non-target embolisation. Multidisciplinary assessment concluded that the findings were due to extravasation of embolic material into the gluteal region. The patient received broad-spectrum intravenous antibiotics, neuropathic pain management, and multidisciplinary care involving gynaecology, surgery, interventional radiology, pain management, neurology, and tissue viability teams. She underwent surgical debridement of the necrotic vulvar tissue, achieving full healing. The gluteal necrosis was managed conservatively with spontaneous resolution. At three-month follow-up, she was asymptomatic from a gynaecological perspective; at two years, she was diagnosed with right leg pain syndrome, possibly piriformis-related. Vulvar necrosis following UAE is an exceptionally rare but clinically significant complication. This case highlights the need for early recognition of post-procedural vulvar or gluteal changes and rapid multidisciplinary intervention to optimise outcomes. Increased reporting of such cases may help clarify risk factors, refine preventive strategies, and guide management.
More Related Videos
 05:21
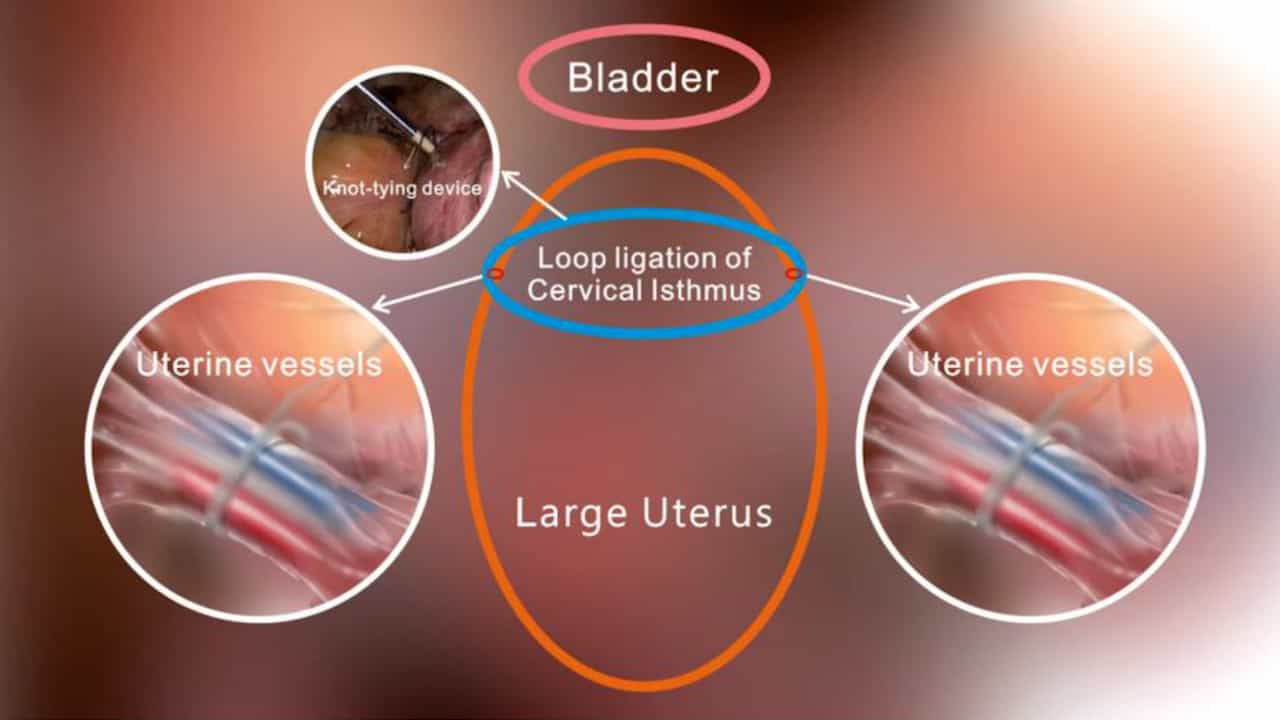
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
 08:07
Author Spotlight: Advancing Labor Management Through Electromyometrial Imaging for Understanding Uterine Contractions
Published on: May 26, 2023
Related Concept Videos
 01:16
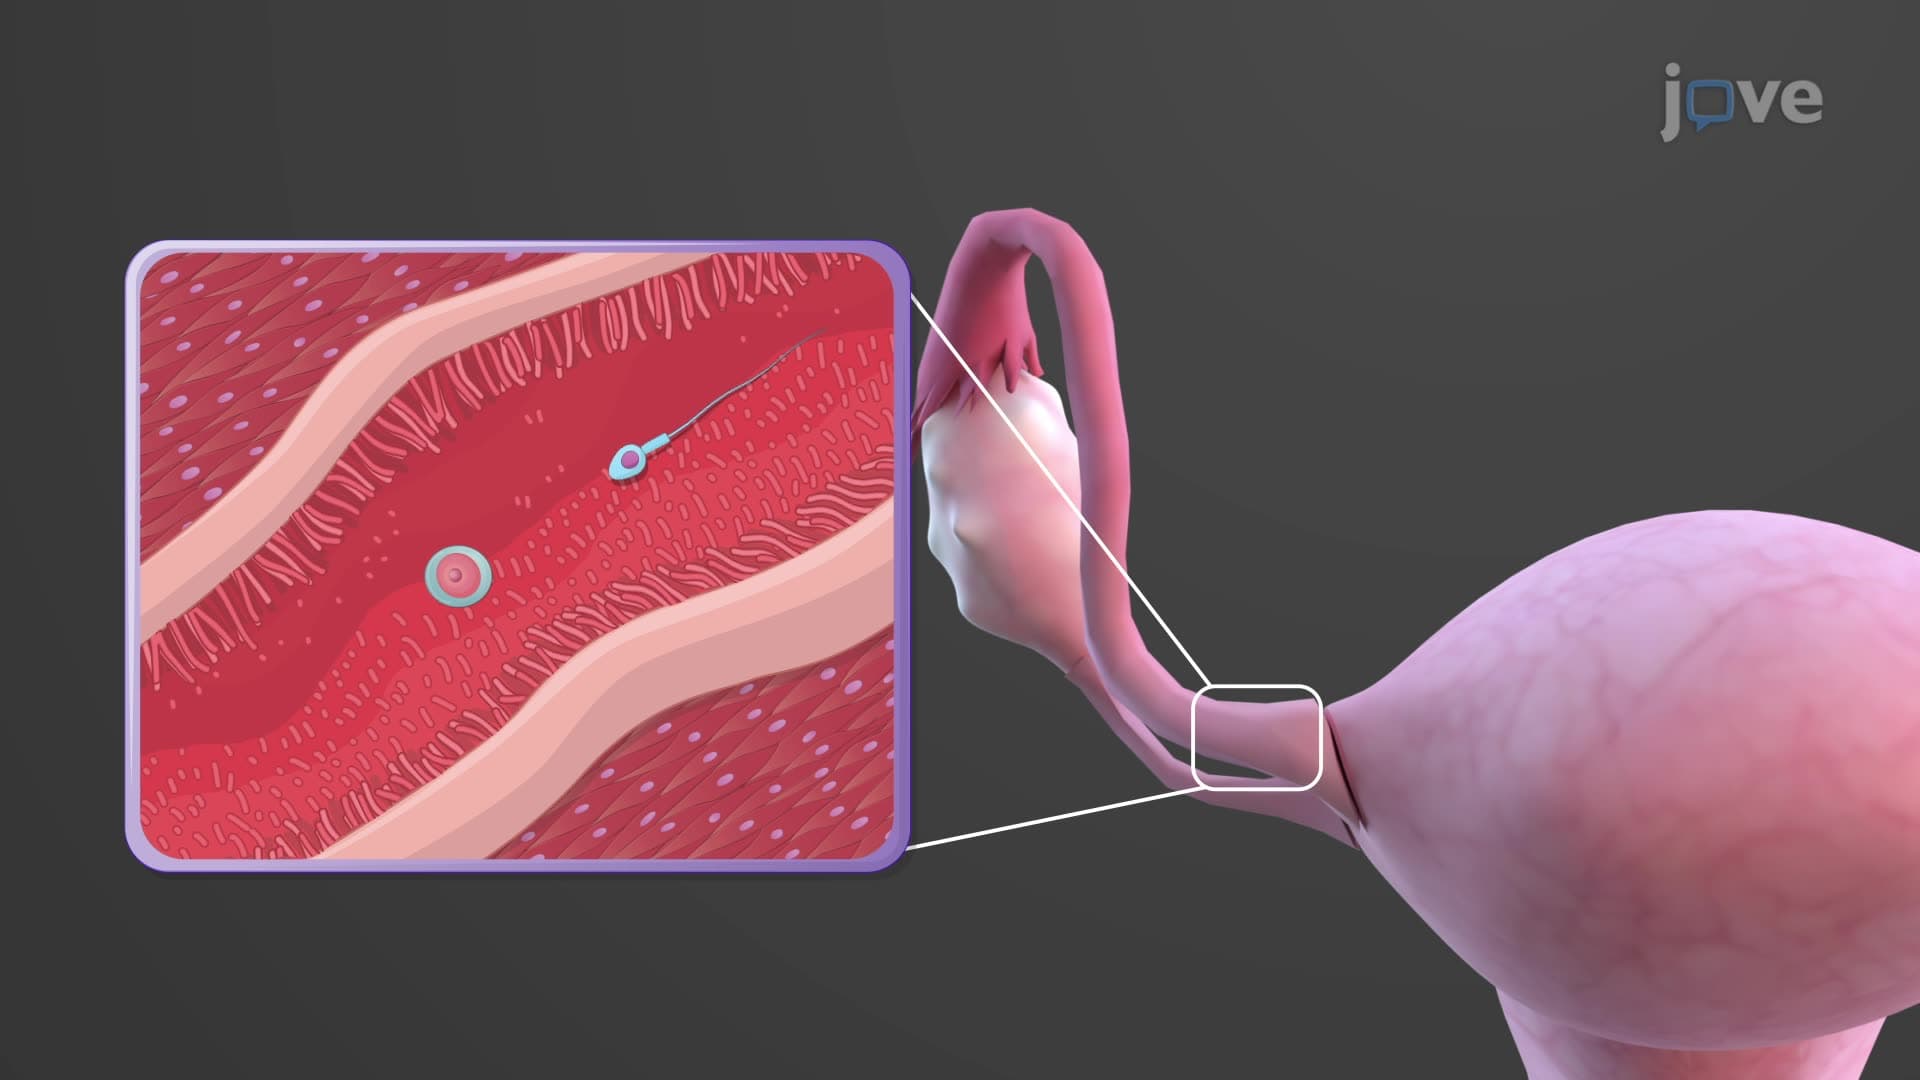
Uterine Tubes
 01:16
Necrosis
Morphological Manifestations of Necrosis
Necrotic cells show different types of morphological appearance depending on the type of tissue and infection. In coagulative necrosis, cells become...
 01:10
Review and Preview
Percentiles are a type of fractile that partition data into...
 01:13
Review and Preview
 01:28
Treatment for Pulmonary Arterial Hypertension: Phosphodiesterase Inhibitors
Among the PDE5 inhibitors, sildenafil (Revatio) stands out as a competitive and selective inhibitor. It operates by elevating cellular levels of cGMP and augmenting signaling through the cGMP-PKG pathway, promoting vasodilation. Upon oral...
 01:18
Treatment for Pulmonary Arterial Hypertension: Endothelin Receptor Antagonists
ETs are synthesized through a complex sequence of enzymatic steps, primarily involving an enzyme referred to as endothelin-converting enzyme...