Related Experiment Video
Updated: Feb 11, 2026
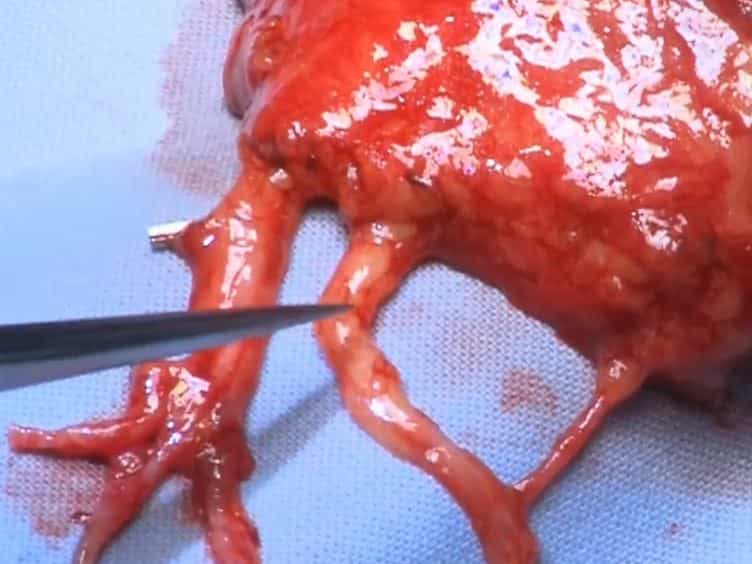

Single-stage Dynamic Reanimation of the Smile in Irreversible Facial Paralysis by Free Functional Muscle Transfer
Published on: March 1, 2015
Combination of Cross-Face Nerve Grafting and Masseteric Nerve Transfer in the Treatment of Incomplete Facial
Jose C Roman Padilla1, Luis Ortiz Peces, Guilermo Chacón Ferrer
1Department of Oral and Maxillofacial Surgery, La Paz University Hospital, Madrid, Spain.

Introduction:
Incomplete facial paralysis (IFP) poses a clinical challenge due to its heterogeneous etiologies and unpredictable outcomes. While treatment for complete paralysis is well established, effective interventions for IFP remain limited. Recently, combining cross-face nerve grafting (CFNG) with masseter nerve transposition (MNT) has emerged as a promising surgical strategy, aiming to provide both strong motor input and spontaneous facial movement in these patients.
Methods:
A systematic review of PubMed and Medscape (2021-2025) was conducted following PRISMA guidelines. Studies were included if they reported clinical outcomes of combined CFNG and MNT in patients with IFP.
Results:
Three studies met the inclusion criteria, comprising 48 patients. Bell's palsy was the most frequent etiology, followed by trauma and postsurgical injuries. Biglioli et al provided the only individual-level outcome data, showing postoperative improvement across etiologies and no significant correlation between age and dynamic recovery-findings consistent with larger cohorts, in which age-related trends do not reach significance. Outcome comparison across studies was limited by heterogeneous assessment tools. A clear trend toward end-to-side neurorrhaphy was observed in recent literature, reflecting a shift toward preserving residual motor fibers.
Conclusions:
Despite heterogeneity in surgical techniques and outcome assessments, CFNG combined with MNT consistently yielded favorable results. The approach described by Morley, involving end-to-side neurorrhaphy, may offer particular advantages by preserving healthy neural pathways and enhancing functional outcomes. While current evidence supports the effectiveness of dual innervation, standardized evaluation methods and larger patient cohorts are essential to validate these findings and guide individualized treatment strategies.

Related Concept Videos
 01:21
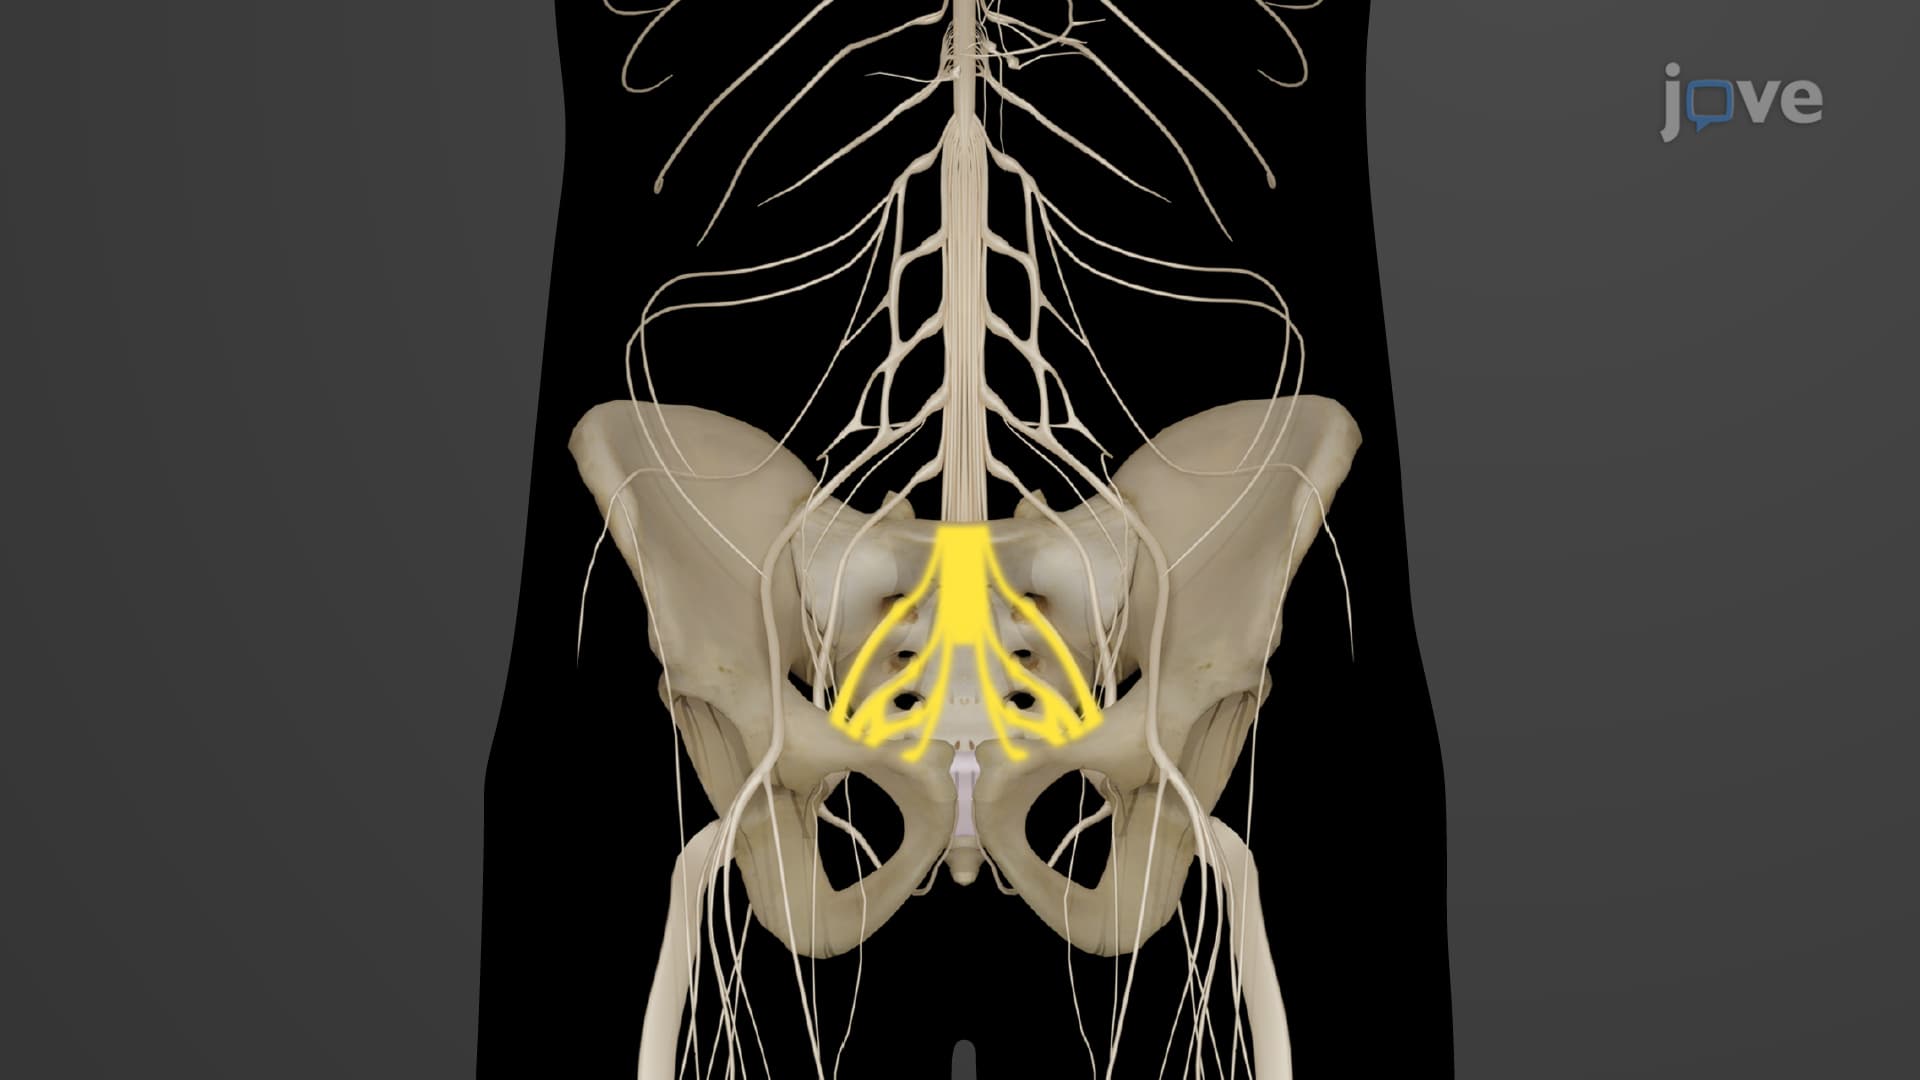
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:27
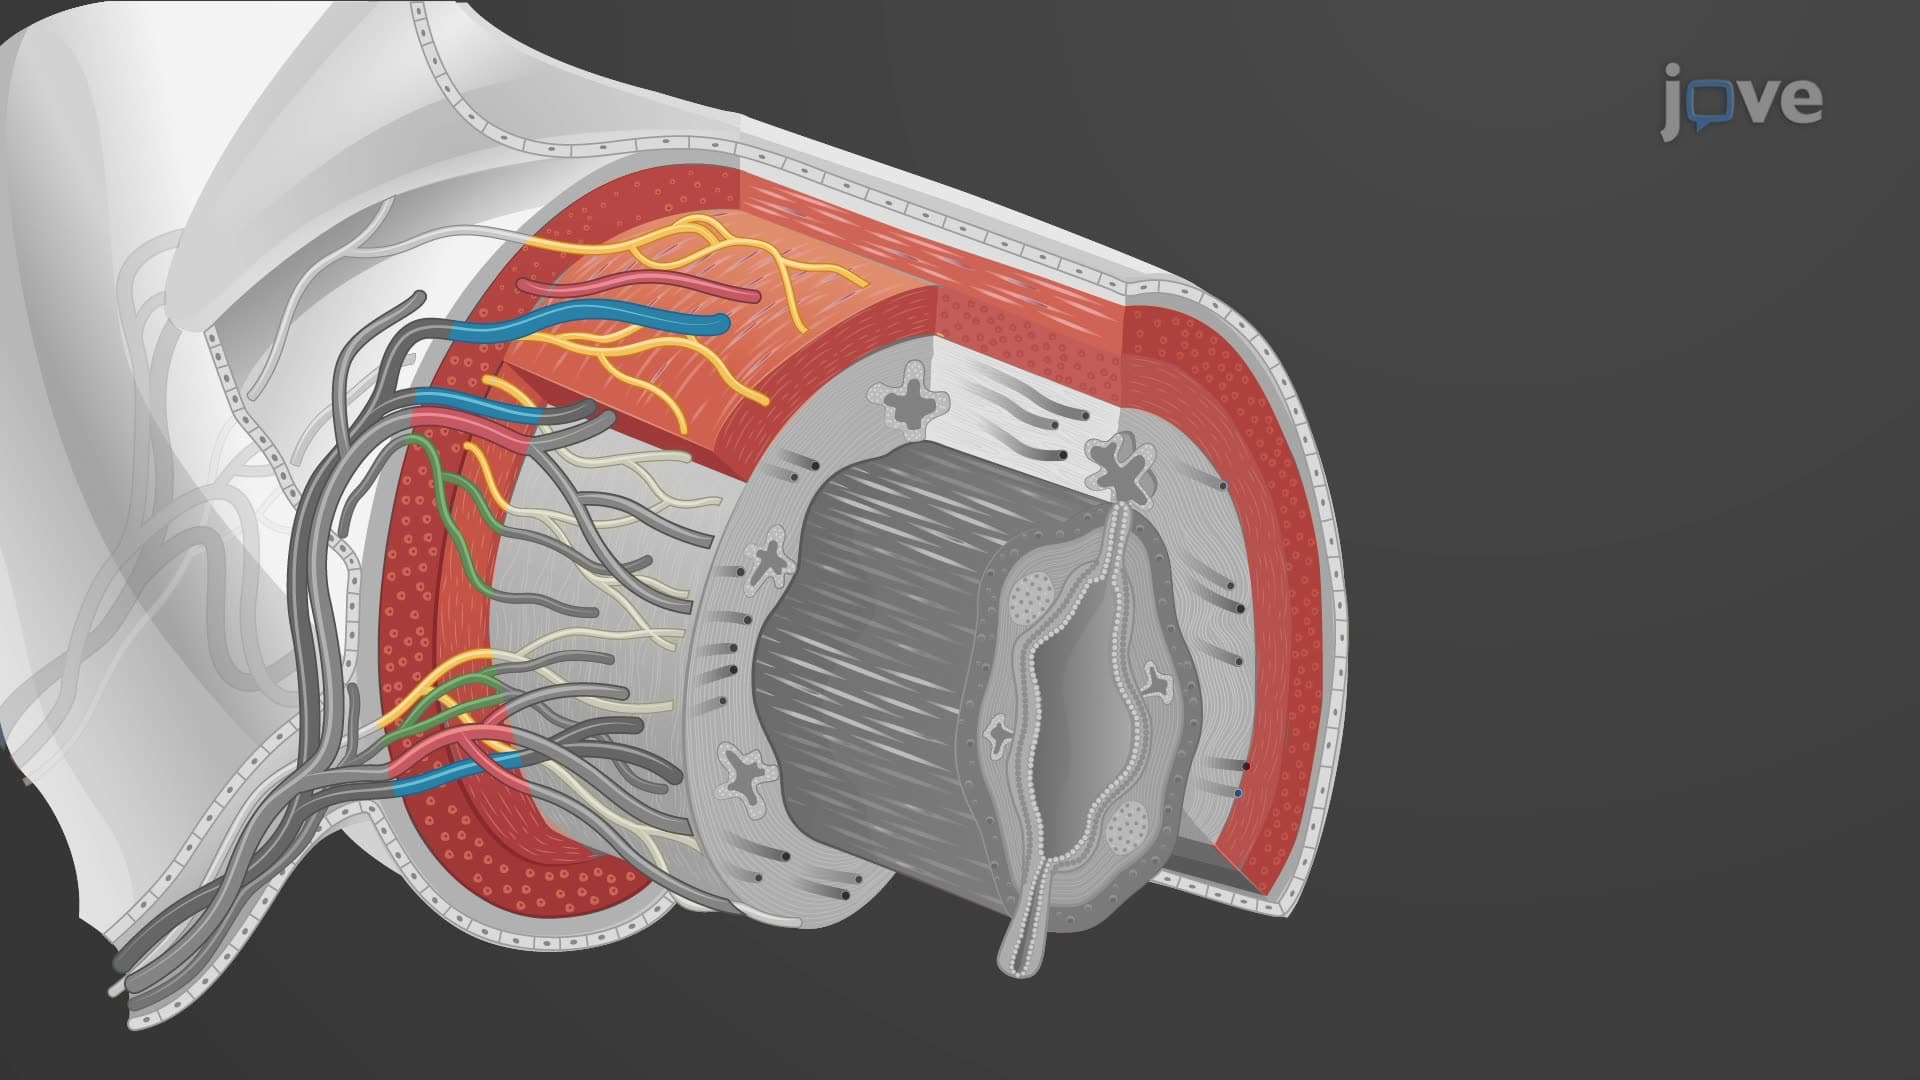
Nerve Supply of the GI Tract
The enteric nervous system consists of two major plexuses: the myenteric plexus (Auerbach's plexus) and the submucosal plexus (Meissner's plexus). These plexuses are located within the layers of...
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:22
Cranial Nerves: Types Part II
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:23
Spinal Nerves: Anatomy
There are 31 bilateral pairs of spinal nerves, each emerging from the spinal cord through the intervertebral foramina—openings between adjacent vertebrae. These nerves are...
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...