Related Experiment Video
Updated: Feb 13, 2026

Using Learning Outcome Measures to assess Doctoral Nursing Education
Published on: June 21, 2010
The magnitude and population burden of educational inequalities in adverse birth outcomes
Anton Schreuder1,2, David van Klaveren3, Richard M K van Dijk4
1Department of Public Health, Erasmus MC, University Medical Center Rotterdam, Rotterdam, 3000, CA, Netherlands. antoniusschreuder@gmail.com.

We aimed to describe the magnitude and population burden of inequality in adverse birth outcomes by maternal education (five categories). Data from 639,007 singleton births of gestational age ≥ 24 weeks or, if missing, birthweight ≥ 500 g were included from the National registry of the Netherlands, 2016-2019. One in six Dutch births had an adverse outcome. Each step down the educational ladder was associated with higher adverse outcome rates. Inequalities in stillbirth and neonatal mortality rates were large between the highest (Master's or higher) and lowest (primary) educated groups (rate ratio [RR] = 2.94 [95%CI: 2.33-3.55] and 2.25 [1.71-2.79], respectively). Inequalities were smaller for preterm birth, small-for-gestational-age, low Apgar score, neonatal intensive care unit admission, and severe congenital anomalies (RR range = 1.32-1.77; PAF range = 13.8-17.7%). Mortality would reduce by a third if the entire population had the mortality rates of the highest educated (population attributable fraction [PAF]stillbirth=35.0% [24.4-45.6%]; PAFneonatal mortality=27.1% [14.4-39.7%]). The middle education category (higher secondary) was the largest group, contributing most to the population burden of inequality despite only having a moderately elevated risk of adverse outcomes. Population health gains would be largest if addressed through preventive approaches targeting the entire health gradient rather than by only focussing on those at highest risk.
We aimed to describe the magnitude and population burden of inequality in adverse birth outcomes by maternal education (five categories). Data from 639,007 singleton births of gestational age ≥ 24 weeks or, if missing, birthweight ≥ 500 g were included from the National registry of the Netherlands, 2016-2019. One in six Dutch births had an adverse outcome. Each step down the educational ladder was associated with higher adverse outcome rates. Inequalities in stillbirth and neonatal mortality rates were large between the highest (Master's or higher) and lowest (primary) educated groups (rate ratio [RR] = 2.94 [95%CI: 2.33-3.55] and 2.25 [1.71-2.79], respectively). Inequalities were smaller for preterm birth, small-for-gestational-age, low Apgar score, neonatal intensive care unit admission, and severe congenital anomalies (RR range = 1.32-1.77; PAF range = 13.8-17.7%). Mortality would reduce by a third if the entire population had the mortality rates of the highest educated (population attributable fraction [PAF]stillbirth=35.0% [24.4-45.6%]; PAFneonatal mortality=27.1% [14.4-39.7%]). The middle education category (higher secondary) was the largest group, contributing most to the population burden of inequality despite only having a moderately elevated risk of adverse outcomes. Population health gains would be largest if addressed through preventive approaches targeting the entire health gradient rather than by only focussing on those at highest risk.


Related Concept Videos
 01:15
Orders of Magnitude
The order of magnitude is simply a way of rounding numbers consistently to the nearest power of 10. This makes doing rough mental math...
 01:23
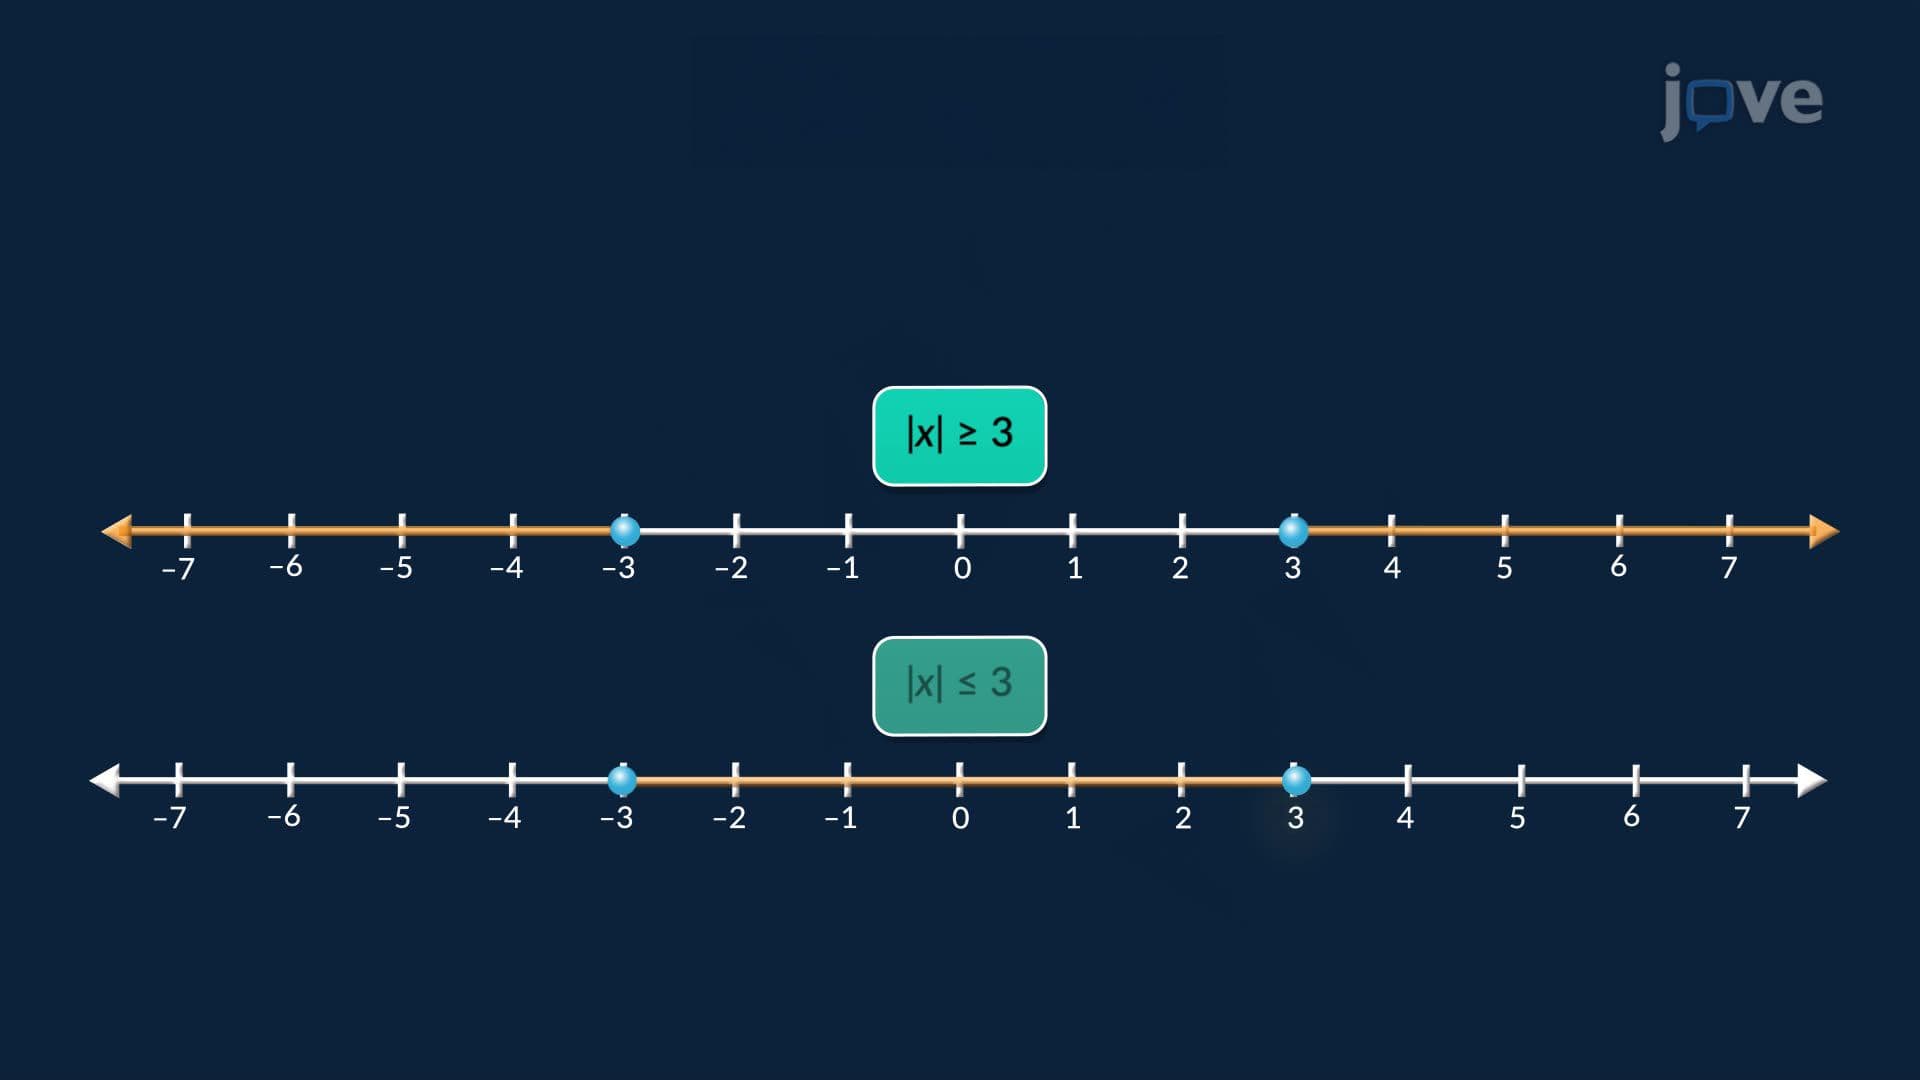
Absolute Value Inequalities
 01:28
Inequalities
 01:22
Birth Control Methods
 01:28
Graphical Representation of Inequalities
 01:24
Solving Inequalities Graphically