Related Experiment Video
Updated: Feb 13, 2026
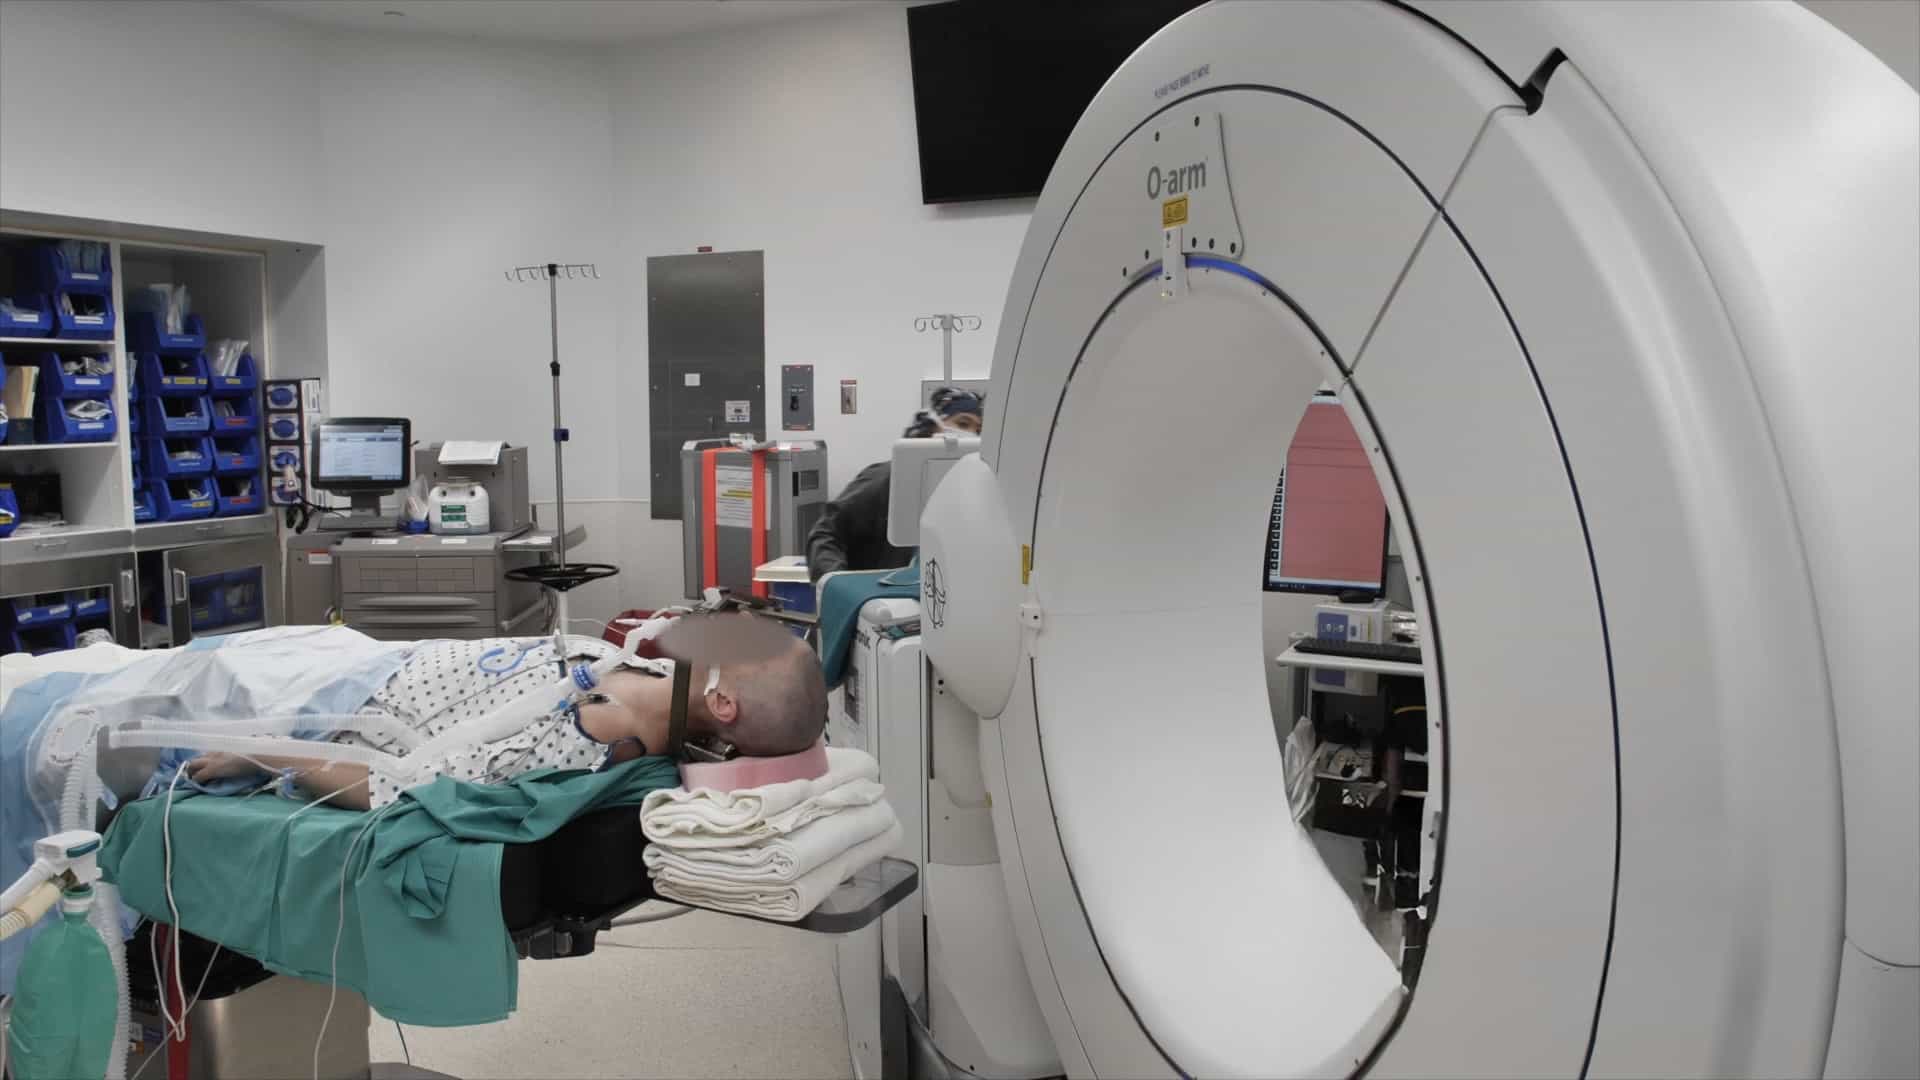
Robotic-Guided Stereoelectroencephalography for Invasive Epilepsy Monitoring
Published on: June 13, 2025
Case Report: Progressive myoclonus epilepsy as an early manifestation of neuronopathic Gaucher disease
Zhou Fang1, Xixi Sun1, Ying Hu1
1Department of Neurology, The First Affiliated Hospital of Anhui Medical University, Hefei, China.

Abstract:
Gaucher disease (GD) is a lysosomal storage disorder caused by biallelic GBA1 variants. Epilepsy is uncommon in GD and rarely manifests as progressive myoclonus epilepsy (PME), making early recognition difficult. We describe a 20-year-old man with childhood-onset myoclonus that progressed to drug-resistant generalized seizures and cognitive decline. Video-electroencephalography (VEEG) showed generalized polyspike-wave discharges associated with myoclonic jerks, whereas brain magnetic resonance imaging was initially normal. Cerebrospinal fluid studies, metabolic screening, and autoimmune encephalitis antibody panels were unremarkable. Glucocerebrosidase activity was markedly reduced, and a targeted myoclonic-epilepsy gene panel identified two GBA1 variants: c.907C > A (p. Leu303Ile) and c.1505G > A (p. Arg502His), indicating a presumed compound-heterozygous state consistent with neuronopathic GD type 3. No hepatosplenomegaly or skeletal abnormalities were detected. Seizure control remained poor despite multiple antiseizure medications and vagus nerve stimulation (VNS). To contextualize this case, we systematically reviewed 22 publications encompassing 71 GD3-PME patients. Most cases presented in childhood, frequently showed typical electrophysiological patterns of generalized or multifocal polyspike-wave discharges, and had early normal MRI followed by later cerebellar or brainstem atrophy. Recurrent compound-heterozygous GBA1 variants, markedly reduced enzyme activity, and poor therapeutic response were common findings. The accompanying systematic review highlights the heterogeneity and therapeutic limitations of GD3-associated PME and underscores the importance of incorporating metabolic and genetic testing into the evaluation of unexplained PME for timely diagnosis and tailored management.

Related Concept Videos
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...