Related Experiment Video
Updated: Feb 14, 2026
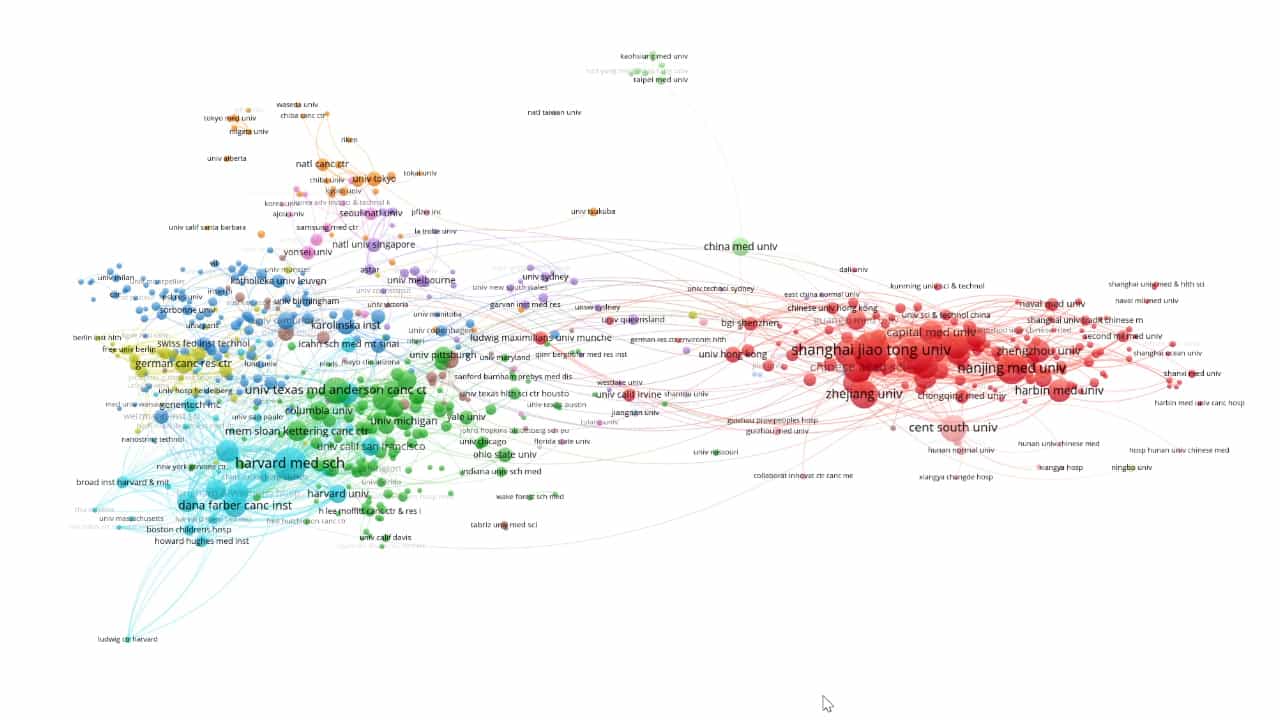

Global and Current Research Trends of Single-Cell Sequencing in Cancer: A Bibliometric and Visualization Study
Published on: April 18, 2025
Trends and inequities in peptic ulcer mortality across the United States, 1999-2023
Xiaoming Lin1, Shuai Wang1, Yunan Guan1
1Department of Gastric and Colorectal Surgery, General Surgery Center, The First Hospital of Jilin University, Changchun, Jilin, China.

Background:
Peptic ulcer disease (PUD) remains a cause of gastrointestinal mortality despite advances in Helicobacter pylori eradication and gastroprotection.
Methods:
We analyzed U.S. death certificates in CDC WONDER from 1999 to 2023, using Underlying Cause-of-Death files. Age-adjusted mortality rates (AAMRs; per 100,000) were standardized to the 2000 U.S.
Population:
Trends used average annual percent change (AAPC). Analyses were stratified by sex, age, race/ethnicity, region, urban-rural status, and ICD-10 subtype (K25-K28).
Results:
From 1999 to 2023, there were 87,574 PUD deaths. Annual deaths fell from 4,575 (1999) to 3,850 (2023; - 15.85%). AAMR declined from 3.30 (95% CI 3.20-3.39) to 1.78 (1.73-1.84) (AAPC - 2.66%, 95% CI - 3.80 to - 1.51). In 2023, AAMR was 2.09 (2.00-2.19) in males and 1.46 (1.39-1.52) in females; rates rose with age from 0.25 (35-44 years) to 14.71 (≥ 85 years). By race/ethnicity, AAMR was 1.81 (non-Hispanic [NH] White), 1.70 (NH Black), 1.57 (NH Other), and 1.47 (Hispanic). The West reached its highest point in 1999 and 2023. By 2013, NCHS (through 2020), the metropolitan AAMR was 1.74 (1.67-1.80) compared to 2.07 (1.91-2.23) in nonmetropolitan areas. Duodenal and gastric ulcers predominated; subtype AAPCs showed the steepest decline for unspecified-site ulcers.
Conclusions:
PUD mortality declined over a 25-year period but plateaued or increased in selected strata in the late 2010s and during the pandemic. Findings support sustained H. pylori control, evidence-based gastroprotection for high-risk medication users, and timely endoscopy-especially for older adults, men, rural residents, and regions with a high burden. Continuous surveillance should monitor post-pandemic rebound risks and equity in access.


Related Concept Videos
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
 01:24
Pathophysiology of Peptic Ulcer Disease: Mucosal Defense Factors
 01:31
Acid Suppressive Drugs for Peptic Ulcer Disease: Antacids
However, this neutralization reaction between...