Related Experiment Video
Updated: Feb 14, 2026

Author Spotlight: Advancing Labor Management Through Electromyometrial Imaging for Understanding Uterine Contractions
Published on: May 26, 2023
The Effect of Oral Supplementation with a Multi-Strain Probiotic Preparation on Group B Streptococcus (GBS) Carriage
Katarzyna Zych-Krekora1, Oskar Sylwestrzak2,3, Michał Krekora3
1Department of Perinatology, Obstetrics and Gynecology, Polish Mother's Memorial Hospital Research Institute, 93-338 Lodz, Poland.

Background/Objectives: Maternal rectovaginal carriage of Group B Streptococcus (GBS, Streptococcus agalactiae) is a major risk factor for vertical transmission and early-onset neonatal infection. Intrapartum antibiotic prophylaxis reduces early-onset disease but does not address antenatal carriage and may affect the maternal-neonatal microbiota. Microbiota-directed interventions, including probiotics, are being explored as complementary strategies. Methods: This prospective, single-centre, open-label pilot intervention study included 10 pregnant women (18-40 years) with singleton pregnancies and a positive vaginal and/or rectal GBS swab, without pre-gestational or gestational diabetes and without antibiotic use in the 4 weeks before enrolment. Participants received OMNi-BiOTiC® FLORA plus (multi-strain lactic acid bacteria, including Lactobacillus crispatus) orally at 2 × 2 g/day from the 15th to the 34th gestational week. Microbiological swabs were obtained at qualification (12-15 weeks), mid-pregnancy (22-25 weeks), and late pregnancy (34-35 weeks). Outcomes were described descriptively. Results: Among 56 screened pregnant women, 10 were GBS-positive (17.9%) and enrolled. All participants were GBS-positive at baseline. At 22-25 weeks, 5/10 (50%) had a negative GBS result. At 34-35 weeks, 9/10 (90%) were GBS-negative, while 1/10 (10%) remained colonised. Time to first negative result ranged from 7.6 to 20.2 weeks from supplementation start (median 8.6 weeks). No recurrences (negative-to-positive transitions) were observed between the second and third sampling points. No adverse events related to supplementation were reported. In contrast, among the 46 women who were GBS-negative at screening and did not receive probiotic supplementation, 14 (30.4%) were found to be GBS-positive at routine screening performed at 35-37 weeks of gestation. Conclusions: In this pilot single-arm study, oral supplementation with a multi-strain probiotic preparation during pregnancy was associated with a time-dependent reduction in rectovaginal GBS carriage and was well tolerated. These preliminary findings support the feasibility of larger randomised controlled trials incorporating microbiome profiling and neonatal outcomes.
Background/Objectives: Maternal rectovaginal carriage of Group B Streptococcus (GBS, Streptococcus agalactiae) is a major risk factor for vertical transmission and early-onset neonatal infection. Intrapartum antibiotic prophylaxis reduces early-onset disease but does not address antenatal carriage and may affect the maternal-neonatal microbiota. Microbiota-directed interventions, including probiotics, are being explored as complementary strategies. Methods: This prospective, single-centre, open-label pilot intervention study included 10 pregnant women (18-40 years) with singleton pregnancies and a positive vaginal and/or rectal GBS swab, without pre-gestational or gestational diabetes and without antibiotic use in the 4 weeks before enrolment. Participants received OMNi-BiOTiC® FLORA plus (multi-strain lactic acid bacteria, including Lactobacillus crispatus) orally at 2 × 2 g/day from the 15th to the 34th gestational week. Microbiological swabs were obtained at qualification (12-15 weeks), mid-pregnancy (22-25 weeks), and late pregnancy (34-35 weeks). Outcomes were described descriptively. Results: Among 56 screened pregnant women, 10 were GBS-positive (17.9%) and enrolled. All participants were GBS-positive at baseline. At 22-25 weeks, 5/10 (50%) had a negative GBS result. At 34-35 weeks, 9/10 (90%) were GBS-negative, while 1/10 (10%) remained colonised. Time to first negative result ranged from 7.6 to 20.2 weeks from supplementation start (median 8.6 weeks). No recurrences (negative-to-positive transitions) were observed between the second and third sampling points. No adverse events related to supplementation were reported. In contrast, among the 46 women who were GBS-negative at screening and did not receive probiotic supplementation, 14 (30.4%) were found to be GBS-positive at routine screening performed at 35-37 weeks of gestation. Conclusions: In this pilot single-arm study, oral supplementation with a multi-strain probiotic preparation during pregnancy was associated with a time-dependent reduction in rectovaginal GBS carriage and was well tolerated. These preliminary findings support the feasibility of larger randomised controlled trials incorporating microbiome profiling and neonatal outcomes.
Related Concept Videos
 01:21
Pilot and Numeric Relaying
 01:11
Oral Cavity
Teeth: The teeth are the hardest structures in our bodies. Humans have two sets of teeth throughout their lifetime: deciduous (baby) teeth and permanent teeth. Each tooth consists of several parts: the crown (visible part), the root (embedded in the jaw), enamel (hard outer...
 01:19
Thermal Strain
 01:20
Shearing Strain
 01:27
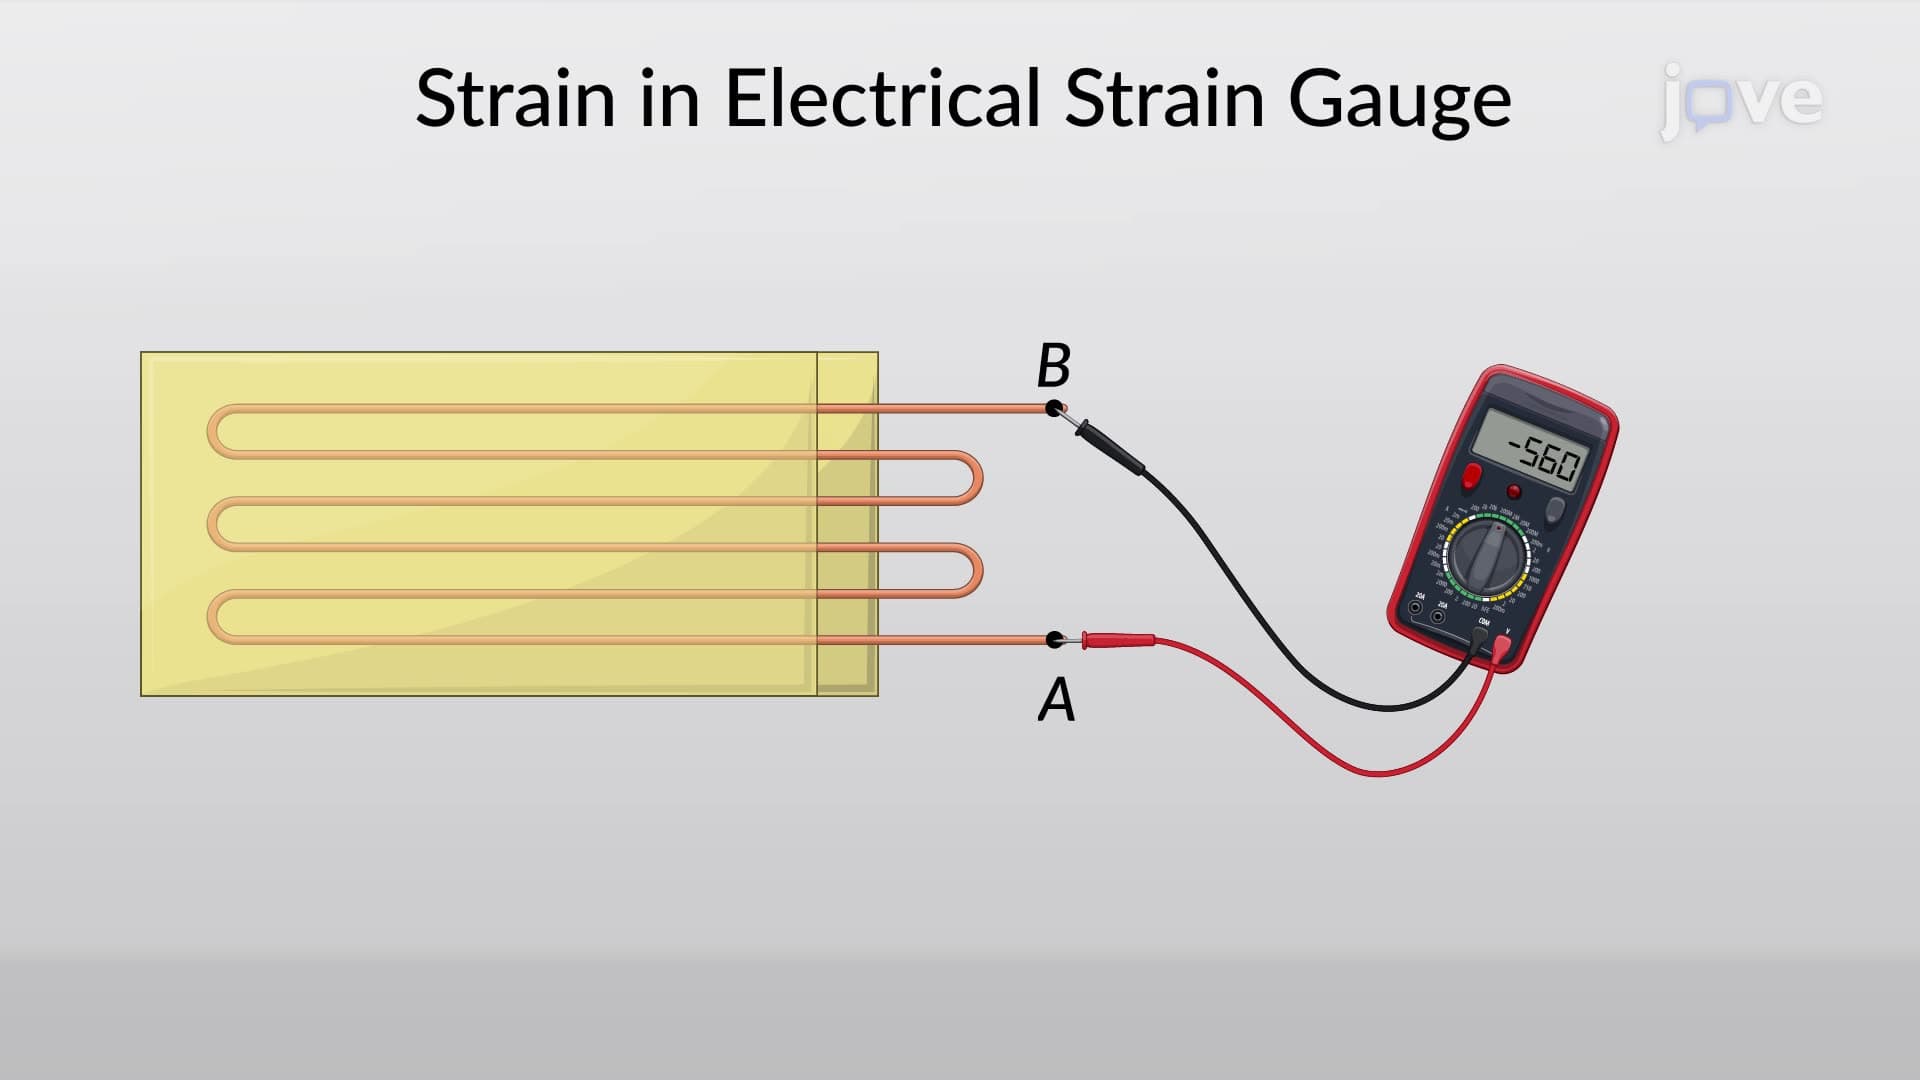
Measurements of Strain
 01:13
Strain Energy
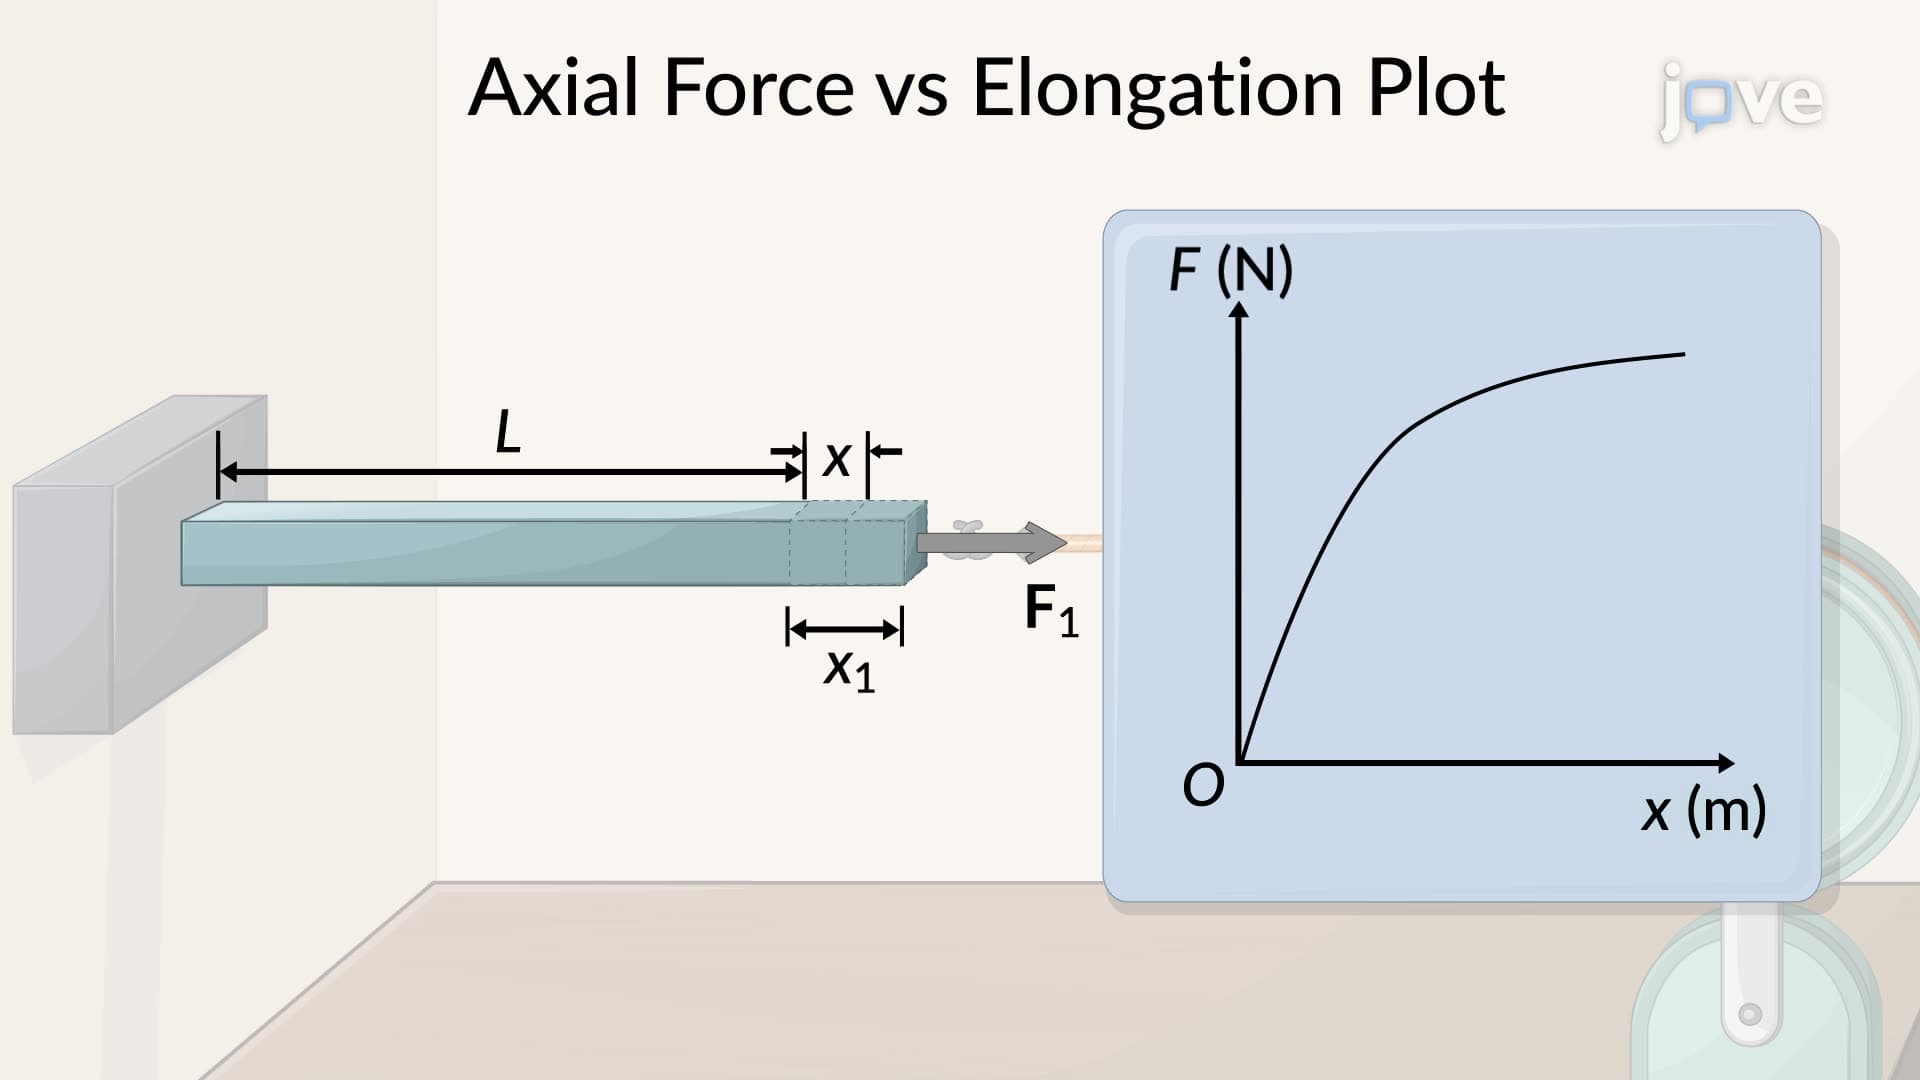
Consider a rod that is fixed at one end and subjected to an axial force at the free end. This axial force induces stress within the rod, leading to its elongation. As the axial force increases, so does the elongation of the rod, illustrating a direct relationship between the force applied and the resulting...