Related Experiment Video
Updated: Feb 14, 2026


A Simple Composite Phenotype Scoring System for Evaluating Mouse Models of Cerebellar Ataxia
Published on: May 21, 2010
Determinants and Phenotypes of Poorly Controlled COPD Using the RADAR Score: A Cohort in Real-World Primary Care
Myriam Calle Rubio1,2,3,4, Soha Esmaili2,3,4,5,6,7, Juan Luis Rodríguez Hermosa1,2,3,4,7
1Pulmonology Department, Hospital Clínico San Carlos, 28040 Madrid, Spain.

Abstract:
Background: Poor clinical control in Chronic Obstructive Pulmonary Disease (COPD) is prevalent, yet the interplay of disease severity, modifiable factors, and clinician perception remains poorly understood. This study aimed to determine the frequency of poor control, identify its independent determinants, and characterize the heterogeneity of the poorly controlled population receiving maintenance inhaled therapy with various devices in primary care. Methods: In a multicenter, cross-sectional analysis of 988 patients from the Study SIMPLIFY, clinical control of COPD was classified using the objective RADAR score. We used multivariable logistic regression and Machine Learning (Random Forest with SHAP analysis) to identify determinants of poor control (RADAR ≥ 4) and k-medoids cluster analysis to characterize the poorly controlled subgroup (n = 452). Results: Nearly half the cohort (45.7%, n = 452) had poor clinical control. Agreement between physician-assessed control (five categories) and RADAR classification was 49.3%, with overestimation in 34.0% and underestimation in 16.7% of cases (Cohen's κ = -0.081; weighted κ = -0.037). The strongest independent determinants were the exacerbator phenotypes (eosinophilic aOR 6.85; non-eosinophilic aOR 4.91). Key modifiable factors included active smoking (aOR 1.92), lower TAI-12 adherence score (per point; aOR 0.96), high dosing frequency (≥4 inhalations/day; aOR 1.54) and high inhaler burden (≥3 devices; aOR 1.84). Machine learning analysis identified clinical phenotype and adherence behavior as the top two scale-independent predictors of poor control. Cluster analysis of the poorly controlled group revealed five reproducible and clinically meaningful phenotypes (C0-C4), primarily separated by treatment complexity, comorbidities, and adherence. Conclusions: Poor clinical control is common and critically under-recognized in primary care patients with COPD on maintenance inhaled therapy. This is driven by a profound clinician perception gap and a failure to address key modifiable determinants, such as high dosing frequency, regimen complexity, and poor adherence, which likely drives therapeutic inertia. Our findings underscore the need to integrate objective tools to unmask poor control and highlight the importance of treatment simplification. The identification of distinct clinical phenotypes provides a roadmap toward a more personalized, evidence-based standard of care.
More Related Videos
 06:49
A Quick Phenotypic Neurological Scoring System for Evaluating Disease Progression in the SOD1-G93A Mouse Model of ALS
Published on: October 6, 2015
 06:16
Signal Acquisition, Score Interpretation, and Economics of a Non-Invasive Point-of-Care Test for Coronary Artery Disease
Published on: August 9, 2024
Related Concept Videos
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:06
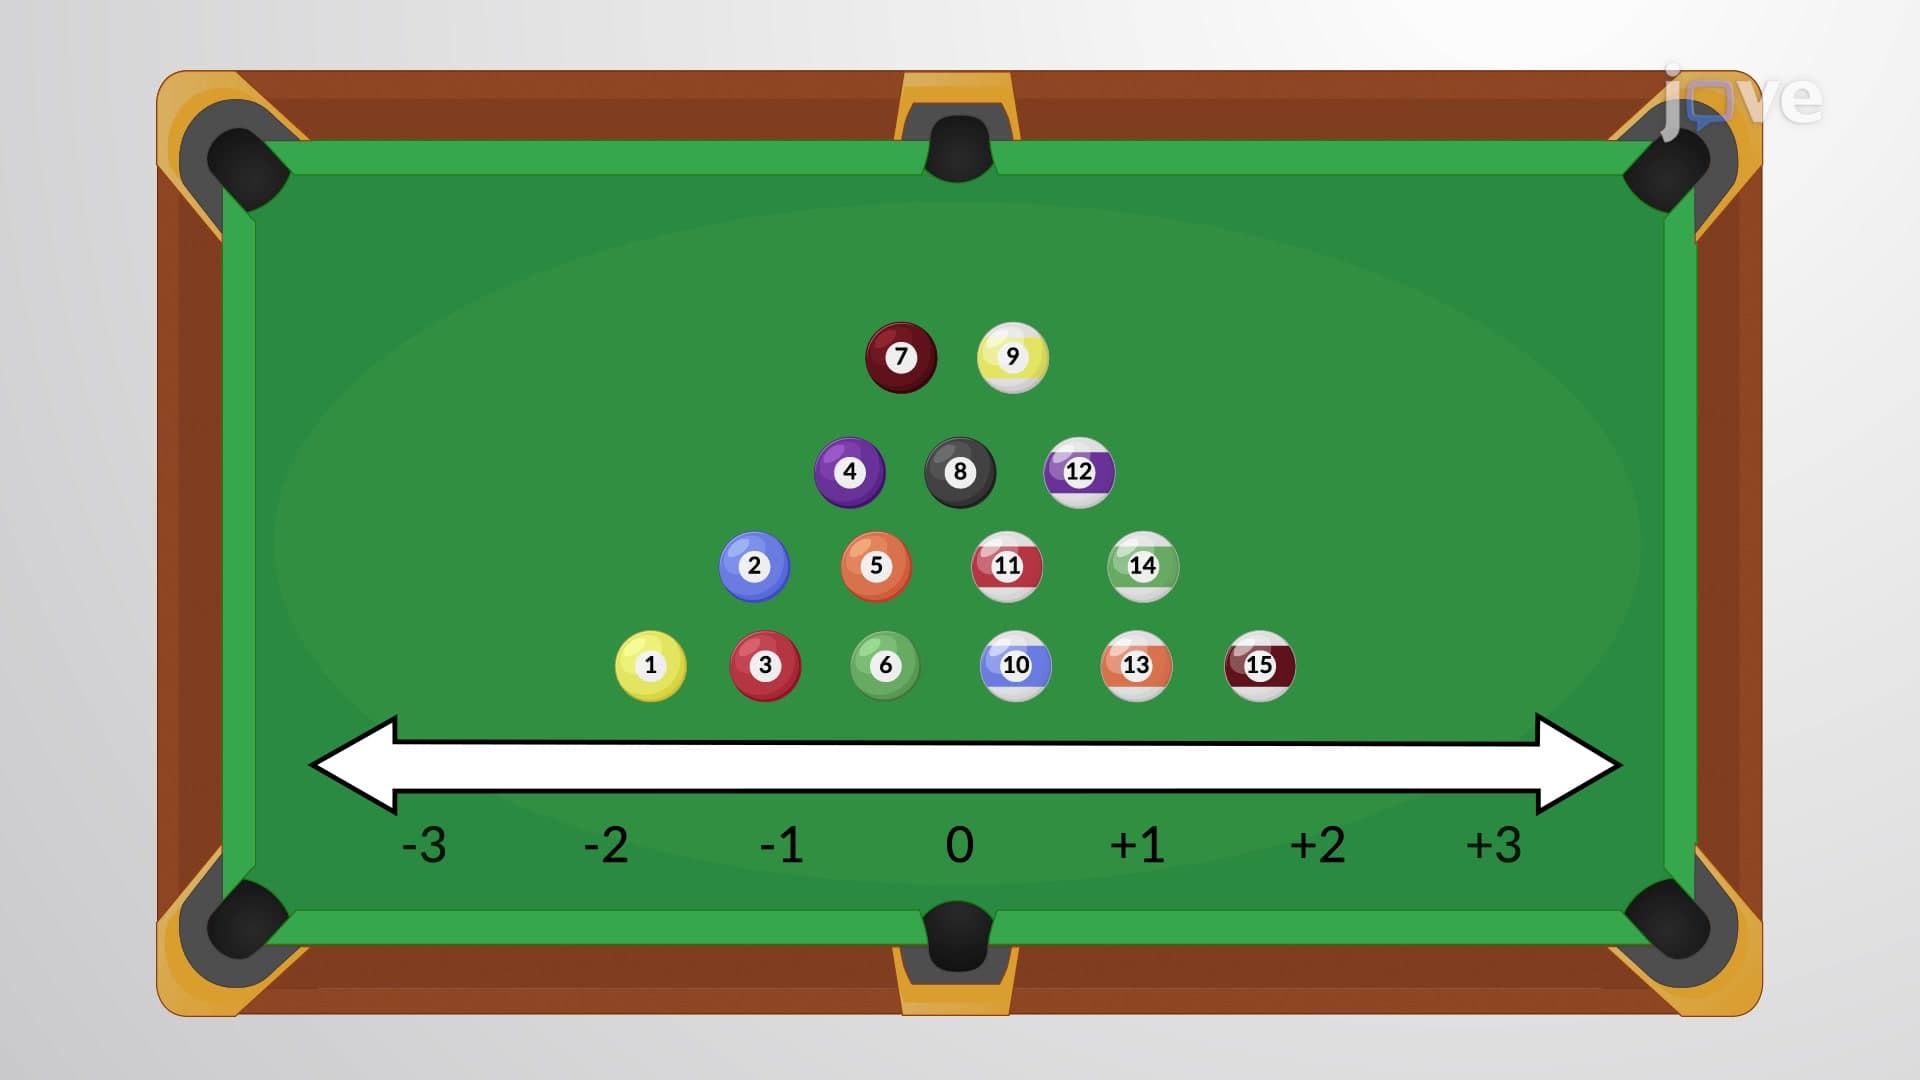
Introduction to z Scores
z scores...
 01:05
Introduction to z Scores
z scores...
 01:17
z Scores and Area Under the Curve
 01:07
z Scores and Unusual Values
This score indicates how far a value is from the mean in terms of standard deviation. For example, if a data value has a z score of +1, the researcher can infer that the particular data value is one standard deviation above the mean. If another data...