Related Experiment Video
Updated: Feb 14, 2026
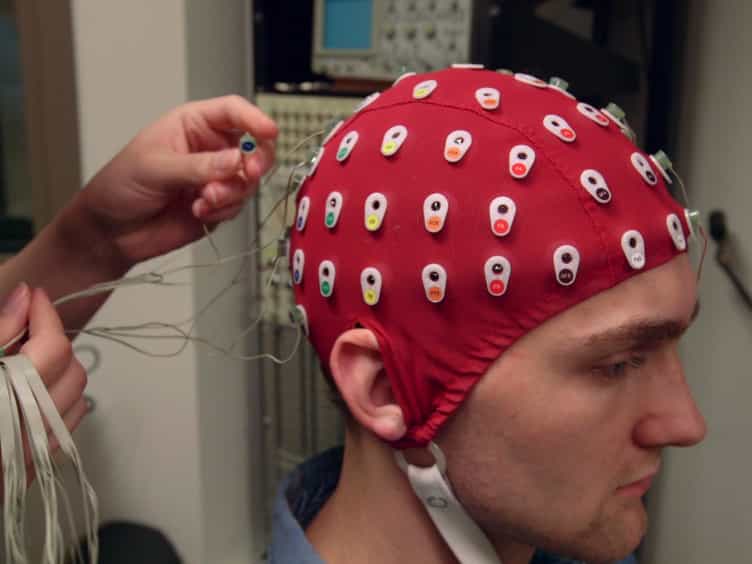

Somatosensory Event-related Potentials from Orofacial Skin Stretch Stimulation
Published on: December 18, 2015
Diagnostic value of somatosensory evoked potentials for paroxysmal sympathetic hyperactivity: a retrospective cohort
Lizhi Liu1, Yuqing Han1, Hui Feng1
1Department of Rehabilitation Medicine, The Affiliated Jiangning Hospital of Nanjing Medical University, Nanjing, China.

Purpose:
This study aimed to investigate the diagnostic value of somatosensory evoked potentials (SEPs) in patients with paroxysmal sympathetic hyperactivity (PSH) and to identify independent predictors of the condition.
Methods:
A retrospective cohort study was conducted on 123 patients with prolonged disorders of consciousness (PDOC) admitted to the Critical Care Rehabilitation Department of Nanjing Jiangning Hospital between August 2022 and August 2024. Patients were classified into PSH-positive (PSH+) and PSH-negative (PSH-) groups according to the Paroxysmal Sympathetic Hyperactivity Assessment Measure (PSH-AM). Demographic, clinical, and SEPs parameters were collected. Univariate and multivariate logistic regression analyses were employed to examine the association between these variables and PSH. The predictive performance was evaluated using receiver operating characteristic (ROC) curve analysis.
Results:
A total of 123 patients with prolonged disorders of consciousness were enrolled in the study. Among these, 34 patients (27.64%) were classified into the PSH + group and 89 patients (72.36%) into the PSH - group. Multivariate logistic regression analysis identified younger age (OR = 0.96, 95% CI: 0.92-0.99, p = 0.02), male patient (OR = 0.28, 95% CI: 0.09-0.75, p = 0.02), and reduced N20-P25 amplitude (OR = 0.34, 95% CI: 0.13-0.70, p = 0.01) as independent predictors of PSH. Using a cut-off value of 1.19 μV for the N20-P25 amplitude, the area under the curve (AUC) for discriminating PSH was 0.811 (95% CI: 0.71-0.912), yielding a sensitivity of 79.7% and a specificity of 75%. The combination of these three predictors improved the AUC to 0.846 (95% CI: 0.75-0.942). After adjusting for potential confounders, partial correlation analysis demonstrated a significant negative correlation between N20-P25 amplitude and PSH-AM score (adj. r = -0.30, p = 0.003).
Conclusion:
A reduced N20-P25 amplitude may serve as an independent and objective electrophysiological biomarker for the early prediction of PSH. In combination with younger age and male patient, it contributes to the identification of high-risk populations and offers valuable guidance for clinical management.

Related Concept Videos
 01:25
The Sympathetic Nervous System
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:31
Sympathetic Signaling
Sympathetic preganglionic fibers release the neurotransmitter acetylcholine (ACh) onto the ganglionic neurons in the...
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:20
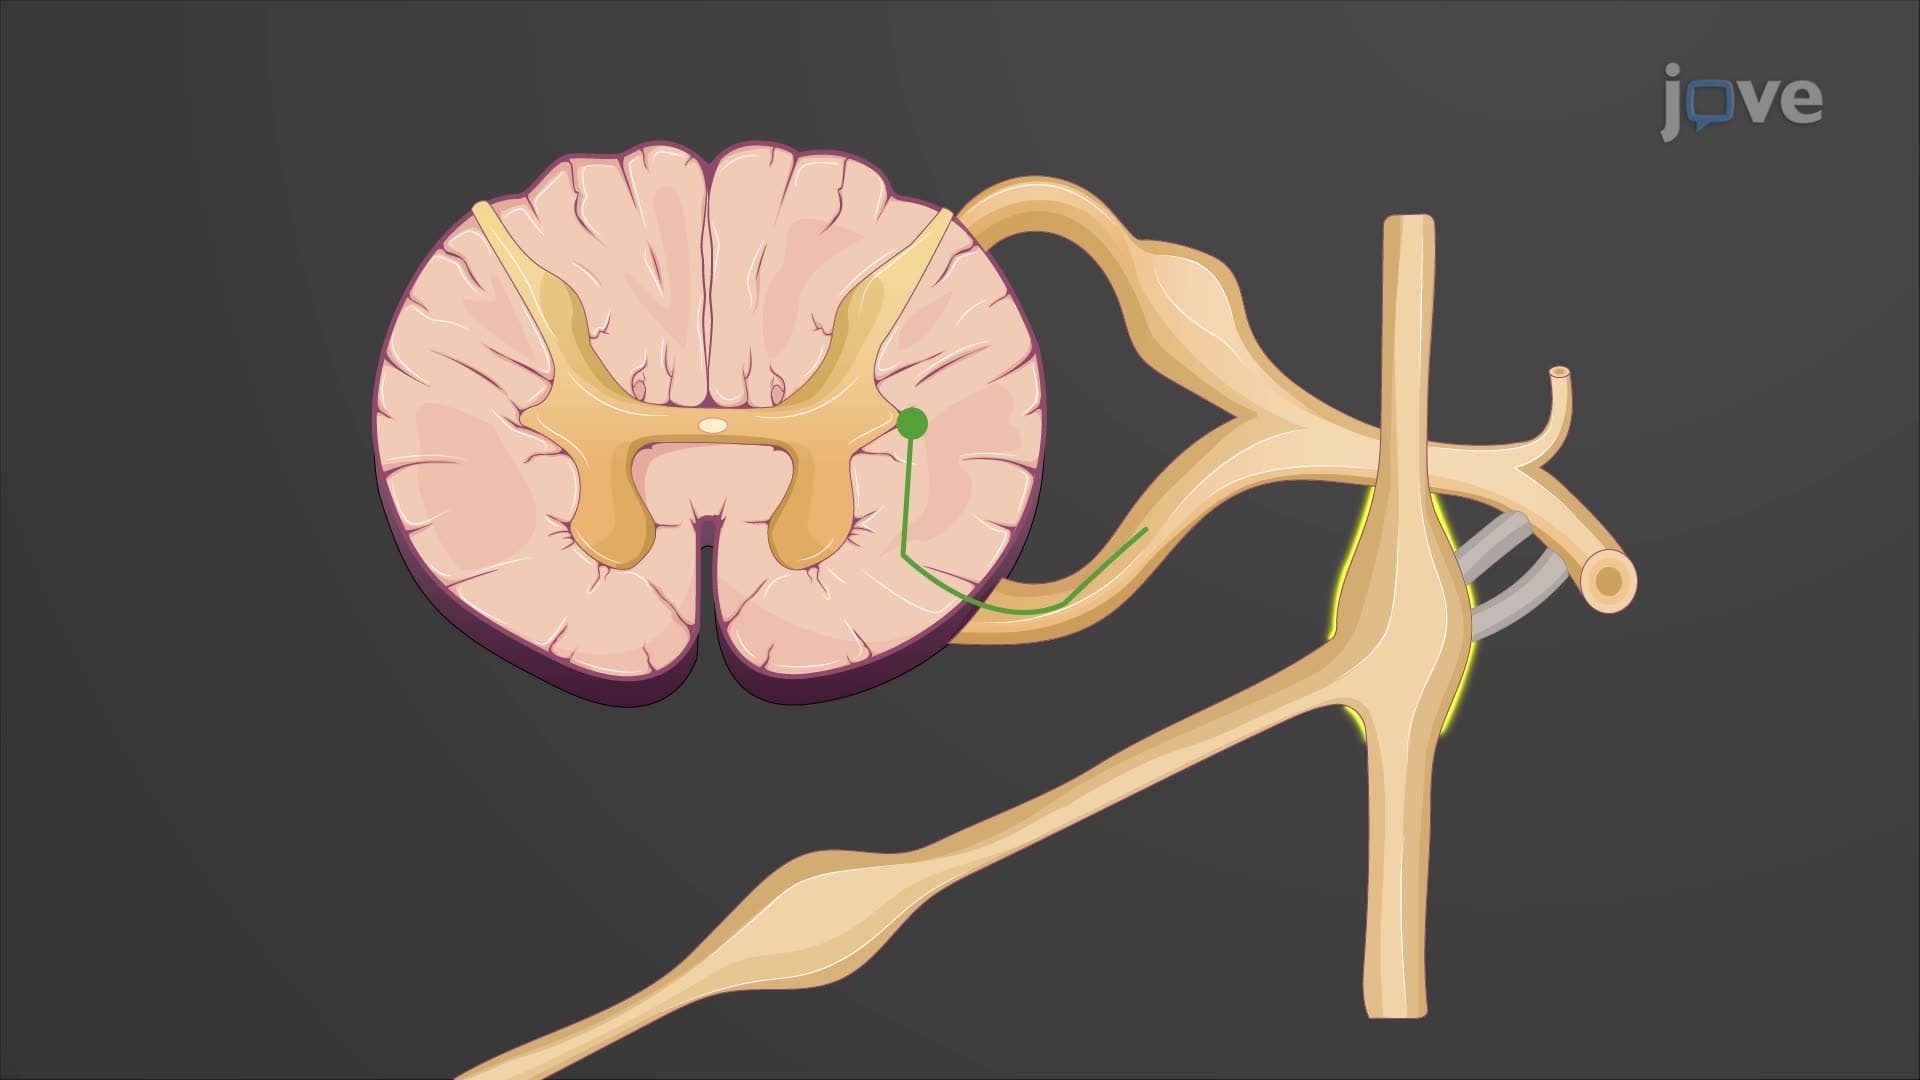
Sympathetic Pathways: Sympathetic Chain Ganglia