Related Experiment Video
Updated: Feb 14, 2026
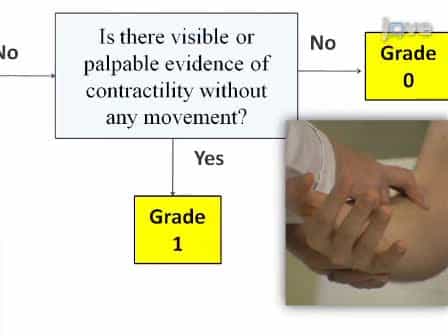

Manual Muscle Testing: A Method of Measuring Extremity Muscle Strength Applied to Critically Ill Patients
Published on: April 12, 2011
Quadriceps Strength and Movement Patterns in Patients After ACLR Who Pass a Clinic-Based Return-to-Sport Testing
David M Werner1,2,3, Ashley Conlin4, Paul Muray4
1College of Allied Health Professions, University of Nebraska Medical Center, Omaha, Nebraska, USA.

Background:
Passing a battery of return to sport (RTS) testing after anterior cruciate ligament reconstruction (ACLR) has been shown to reduce second injury rates. However, previously reported testing methods are inaccessible for most clinicians due to equipment, financial, and time constraints.
Purpose:
To assess whether patients after ACLR who pass a clinic-based RTS evaluation have residual strength and/or biomechanical deficits when tested compared with gold standard techniques.
Study Design:
Cross-sectional study; Level of evidence, 3.
Methods:
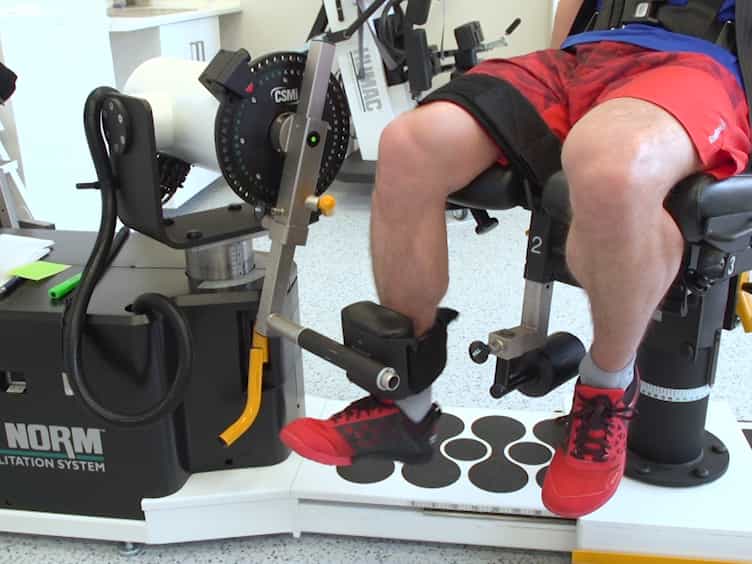
All participants passed a battery of clinic-based RTS tests-including ≥90% limb symmetry during isometric quadriceps strength, 1-repetition maximum isotonic knee extension, and 4 single-legged hop tests (single, crossover, triple, and 6-m timed)-as well as ≥90% on the Global Rating Scale and the International Knee Documentation Committee Subjective Knee Form 2000. Laboratory testing then included isometric quadriceps strength and rate of torque development (RTD) (90° of knee flexion) and isokinetic concentric quadriceps and hamstring strength (60 deg/sec) using an isokinetic dynamometer. An 8-camera, 2-force-plate, 3-dimensional motion analysis system was used to measure sagittal-plane joint angles and moments during bilateral and unilateral drop-vertical jumping. Paired t tests were conducted to assess interlimb differences.
Results:
In laboratory testing, the peak isometric quadriceps strength was 7.6% lower in the involved limb (P < .001). The isometric quadriceps RTD was up to 20.9% lower in the involved limb (P < .001). Isokinetically, the peak quadriceps strength was 4.9% lower in the involved limb (P = .003), while the peak hamstring strength was 4.7% higher in the involved limb (P = .017). All biomechanical measures demonstrated impaired loading of the injured limb with interlimb differences ranging from 6.6% to 67% (P < .005).
Conclusion:
Passing clinic-based RTS testing resulted in laboratory-based strength ≥90% limb symmetry and a previously established target of isometric quadriceps strength of 3 N·m/kg. However, deficits in quadriceps RTD and movement asymmetries persisted despite passing clinical criteria.

Related Concept Videos
 01:12
Non-destructive Tests for Concrete Strength
 02:29
Relative Strengths of Conjugate Acid-Base Pairs
 03:12
Batteries and Fuel Cells
 01:12
First Pass Effect
Depending on the route of administration, drugs can be metabolized in the liver, intestine, lungs, and vasculature. Orally administered drugs are first absorbed through the...
 02:35
Acid and Bases: Ka, pKa, and Relative Strengths
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests