Related Experiment Video
Updated: Feb 15, 2026


Y-90 Radioembolization and PD-1 Inhibitor as Neoadjuvant Treatment in Hepatocellular Carcinoma
Published on: May 24, 2024
Neoadjuvant immune checkpoint inhibitors for localized dMMR/MSI-H gastric cancer: a meta-analysis
W K Schwengber1, R A Pereira2, L F Leite da Silva3
1Internal Medicine Division, Mayo Clinic, Phoenix, USA.

Background:
Early studies indicate that neoadjuvant immune checkpoint inhibitors (ICIs) induce high rates of tumor regression in localized deficient mismatch repair (dMMR) and microsatellite instability-high (MSI-H) gastric and gastroesophageal junction (GEJ) cancers, raising interest in nonoperative management (NOM). Most available data, however, come from small, nonrandomized cohorts. A systematic synthesis was undertaken to better characterize efficacy and safety outcomes.
Materials And Methods:
A systematic search of PubMed, EMBASE, Scopus, Web of Science, and Cochrane Reviews was conducted from inception through June 2025 for prospective or retrospective studies of neoadjuvant ICIs in localized dMMR/MSI-H gastric or GEJ cancers reporting at least one prespecified outcome. Two reviewers independently extracted data and assessed study quality according to Preferred Reporting Items for Systematic Reviews and Meta-Analysis (PRISMA) guidelines. Pooled estimates were calculated using a DerSimonian and Laird random-effects model, and NOM outcomes were qualitatively summarized.
Results:
Twenty studies (396 patients) met inclusion criteria; three used dual ICI therapy, and the remainder used ICI alone or with chemotherapy. Overall, 320 patients (81.0%) underwent surgical resection. The pooled pathologic complete response (pCR) rate was 41.9% [95% confidence interval (CI) 33.2% to 51.1%], clinical complete response 63.8% (95% CI 45.6% to 78.8%), major pathologic response 64.2% (95% CI 49.1% to 76.9%), and grade 3-4 immune-related adverse events 6.7% (95% CI 1.7% to 13.8%). pCR was higher with treatment duration ≥3 months compared with <3 months [50.2% (95% CI 42.3% to 58.7%) versus 28.4% (95% CI 18.9% to 40.2%), χ2 = 8.84, P = 0.003]. Forty-four patients were managed nonoperatively, with two early local regrowths at median follow-up ranging from 11.5 to 28 months.
Conclusions:
Neoadjuvant ICIs are associated with favorable efficacy and safety in localized dMMR/MSI-H gastric and GEJ cancers. Longer neoadjuvant exposure (≥3 months) may improve pCR rates. Larger prospective studies are needed to define optimal treatment duration and the role of organ-preserving strategies such as NOM.
Insights
Neoadjuvant immune checkpoint inhibitors (ICIs) show promise for deficient mismatch repair (dMMR) and microsatellite instability-high (MSI-H) gastric cancers. Longer treatment durations may improve pathologic complete response (pCR) rates, supporting further research into nonoperative management.
Area of Science:
- Oncology
- Gastroenterology
- Immunotherapy
Background:
- Localized deficient mismatch repair (dMMR) and microsatellite instability-high (MSI-H) gastric and gastroesophageal junction (GEJ) cancers show promising tumor regression with neoadjuvant immune checkpoint inhibitors (ICIs).
- Existing data primarily derive from small, nonrandomized studies, necessitating a comprehensive synthesis of efficacy and safety outcomes.
Purpose of the Study:
- To systematically evaluate the efficacy and safety of neoadjuvant ICIs in localized dMMR/MSI-H gastric and GEJ cancers.
- To characterize outcomes associated with nonoperative management (NOM) in this patient cohort.
Main Methods:
- A systematic literature search was performed across major databases (PubMed, EMBASE, Scopus, Web of Science, Cochrane Reviews) up to June 2025.
- Data extraction and quality assessment were conducted by two independent reviewers following PRISMA guidelines.
- Pooled estimates for efficacy endpoints and qualitative summary of NOM outcomes were generated.
Main Results:
- Twenty studies encompassing 396 patients were included, with most receiving ICI monotherapy or combination therapy.
- The pooled pathologic complete response (pCR) rate was 41.9%, with a clinical complete response of 63.8%.
- Treatment duration of ≥3 months was associated with significantly higher pCR rates (50.2%) compared to <3 months (28.4%). Grade 3-4 immune-related adverse events occurred in 6.7% of patients.
Conclusions:
- Neoadjuvant ICIs demonstrate favorable efficacy and safety profiles in localized dMMR/MSI-H gastric and GEJ cancers.
- Extended neoadjuvant ICI treatment (≥3 months) may enhance pCR rates.
- Further prospective research is crucial to optimize treatment duration and establish the role of organ-preserving strategies like NOM.


Related Concept Videos
 02:19
The Spindle Assembly Checkpoint
Many proteins function together to control the spindle assembly checkpoint. Mutations affecting these proteins may allow cells to proceed into anaphase prematurely, resulting in the...
 01:52
Eukaryotic Transcription Inhibitors
Eukaryotic transcription inhibitors usually contain two distinct domains, a...
 01:16
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...
 01:21
Cancer Survival Analysis
 01:09
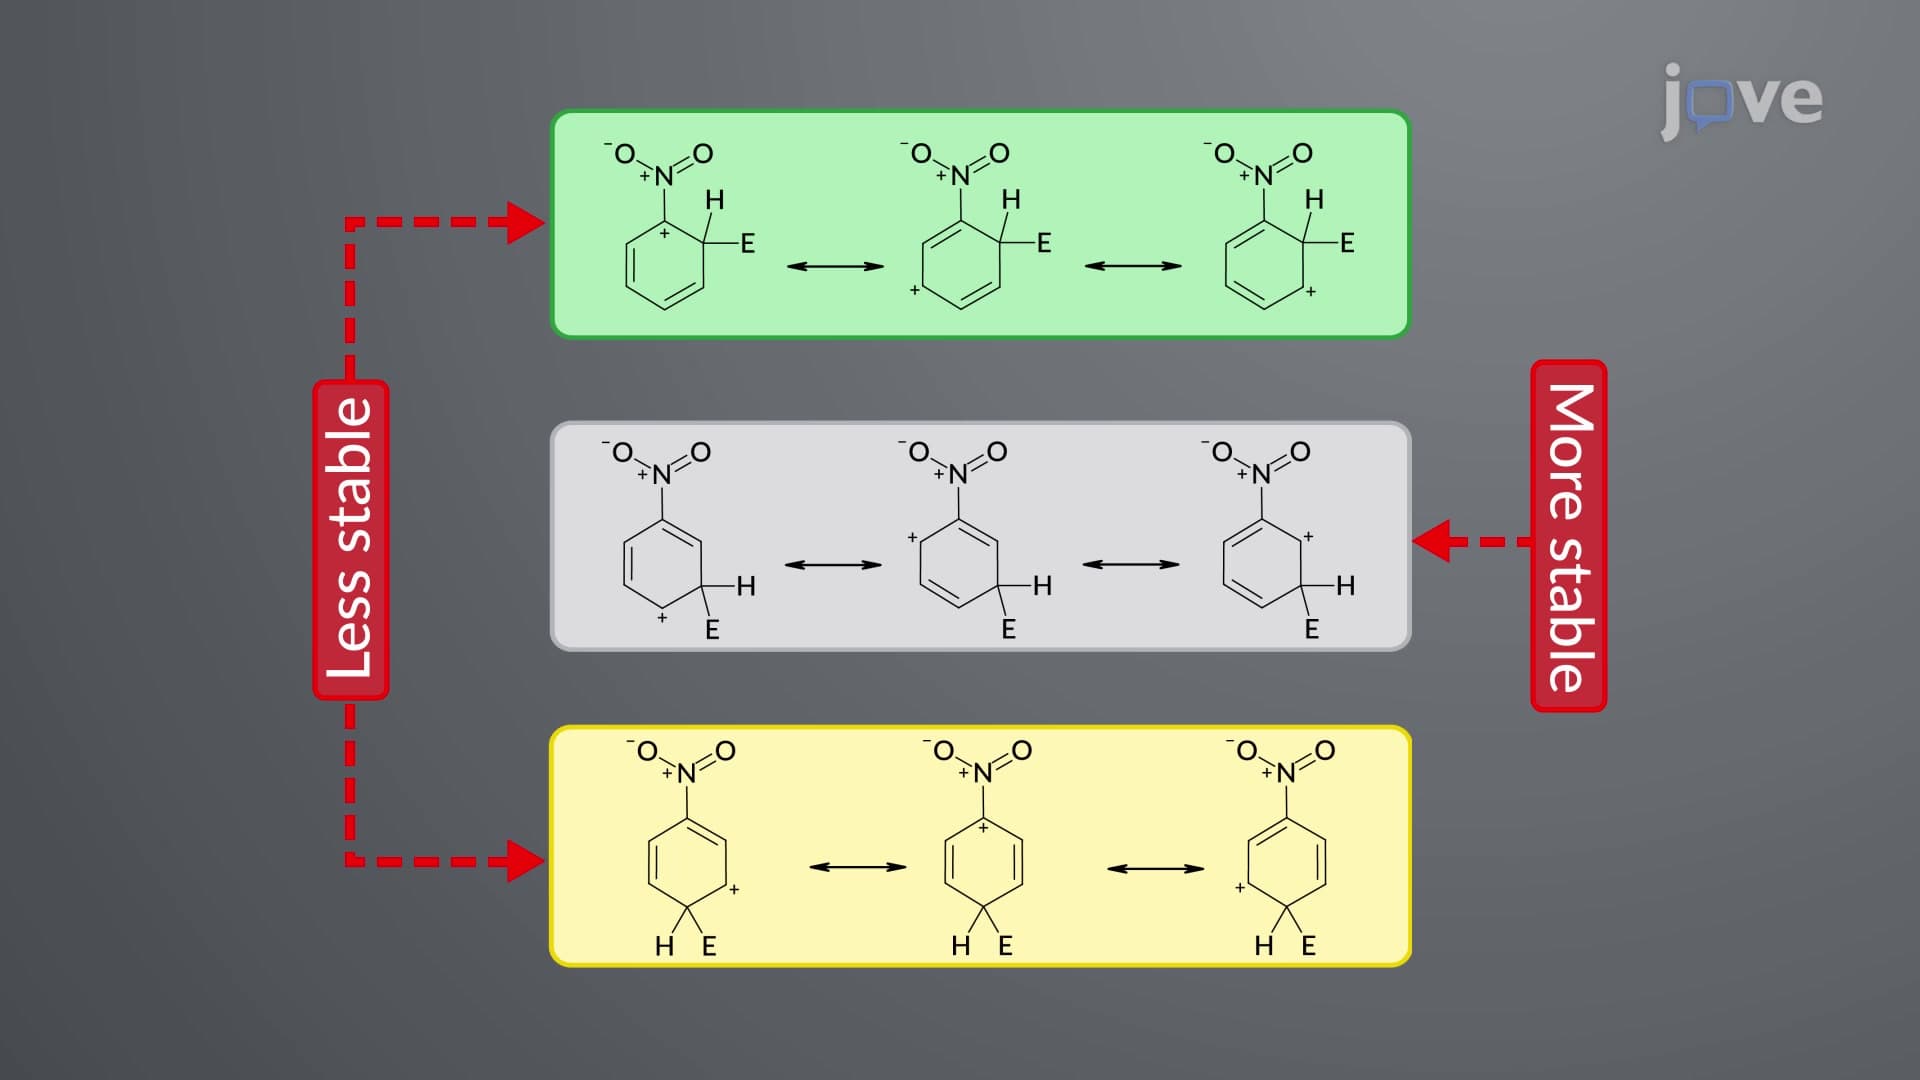
Directing Effect of Substituents: meta-Directing Groups
 01:16
Gastric Emptying