Related Experiment Video
Updated: Feb 15, 2026


Myocardial Infarction and Functional Outcome Assessment in Pigs
Published on: April 25, 2014
Chronic total occlusion and outcomes after out-of-hospital cardiac arrest with ST-segment elevation myocardial
Vincent Pham1, Andrea Cupiraggi2, Thibault Gasparato2
1Cardiology Department, Cochin Hospital, AP-HP, 75014 Paris, France; Université Paris Cité, Inserm 0970, Paris Cardiovascular Research Center, 75015 Paris, France; Association pour la Recherche et l'Innovation Cardiovasculaire Paris Centre, 75013 Paris, France.

Insights
Chronic total occlusions in ST-segment elevation myocardial infarction patients resuscitated from cardiac arrest are linked to higher crude death rates. However, these occlusions do not independently predict outcomes after adjustment for other factors.
Area of Science:
- Cardiology
- Interventional Cardiology
- Critical Care Medicine
Background:
- Out-of-hospital cardiac arrest (OHCA) with ST-segment elevation myocardial infarction (STEMI) has high mortality.
- Chronic total occlusions (CTOs) are common in coronary artery disease and linked to adverse outcomes in acute coronary syndromes.
- The prognostic significance of CTOs in OHCA patients with STEMI is not well-defined.
Purpose of the Study:
- To investigate the prognostic impact of coronary chronic total occlusions (CTOs) in patients who have been resuscitated from OHCA with STEMI.
- To determine if CTOs independently predict mortality in this high-risk patient population.
Main Methods:
- Analysis of data from the prospective PROCAT registry (2007-2024).
- Inclusion of consecutive patients with OHCA, return of spontaneous circulation, and STEMI undergoing emergent coronary angiography.
- Assessment of CTO presence at baseline, with 90-day all-cause death and in-hospital death as primary and secondary endpoints, respectively. Logistic regression and Cox models were used for analysis.
Main Results:
- Among 352 patients, 16% had CTOs. CTO patients were older, had more comorbidities, and more extensive coronary artery disease.
- Crude rates of in-hospital death (55.2% vs. 39.8%) and 90-day death (69.0% vs. 49.0%) were significantly higher in the CTO group.
- After multivariable adjustment, CTO was not an independent predictor of in-hospital or 90-day mortality.
Conclusions:
- CTO is associated with increased crude mortality rates in resuscitated OHCA patients with STEMI.
- CTO does not independently predict outcomes in this cohort after adjusting for clinical and resuscitation factors.
- CTO likely represents a marker of higher atherosclerotic burden rather than a direct cause of early death, but remains relevant for long-term management.
Background:
Out-of-hospital cardiac arrest in the setting of ST-segment elevation myocardial infarction is associated with high death rates. Chronic total occlusions are frequent in coronary artery disease, and have been linked to poor outcomes in acute coronary syndromes, but their prognostic impact in patients with out-of-hospital cardiac arrest in the setting of ST-segment elevation myocardial infarction is unclear.
Aim:
To evaluate the prognostic impact of coronary chronic total occlusions in patients resuscitated from out-of-hospital cardiac arrest with ST-segment elevation myocardial infarction.
Methods:
We analysed data from the prospective PROCAT registry including consecutive patients with out-of-hospital cardiac arrest with return of spontaneous circulation and ST-segment elevation myocardial infarction who underwent emergent coronary angiography between 2007 and 2024. The presence of chronic total occlusion was assessed at baseline. The primary endpoint was 90-day all-cause death; secondary endpoints included in-hospital death. Logistic regression and Cox models were used to assess associations between chronic total occlusion and outcomes.
Results:
Among 352 patients included, chronic total occlusion was present in 58 (16%). Patients with chronic total occlusion were older, had more co-morbidities and exhibited more extensive coronary artery disease. Rates of in-hospital death (55.2% vs. 39.8%; P=0.030) and 90-day death (69.0% vs. 49.0%; P=0.005) were higher in the chronic total occlusion group. In the univariate analysis, chronic total occlusion was associated with increased in-hospital deaths (odds ratio: 1.86, 95% confidence interval: 1.05-3.29) and 90-day deaths (hazard ratio: 1.76, 95% confidence interval: 1.18-2.62). However, after multivariable adjustment for clinical and resuscitation-related factors, chronic total occlusion was not independently associated with either endpoint.
Conclusions:
In patients resuscitated from out-of-hospital cardiac arrest with ST-segment elevation myocardial infarction, chronic total occlusion is associated with increased crude death rates, but does not independently predict outcomes after adjustment. Chronic total occlusion probably reflects a higher atherosclerotic burden rather than being a direct driver of early death. The detection of chronic total occlusion remains clinically relevant for long-term management.


Related Concept Videos
 00:59
Hospitals-II
Nurses that work in...
 01:28
Hospitals-I
 03:12
Freezing Point Depression and Boiling Point Elevation
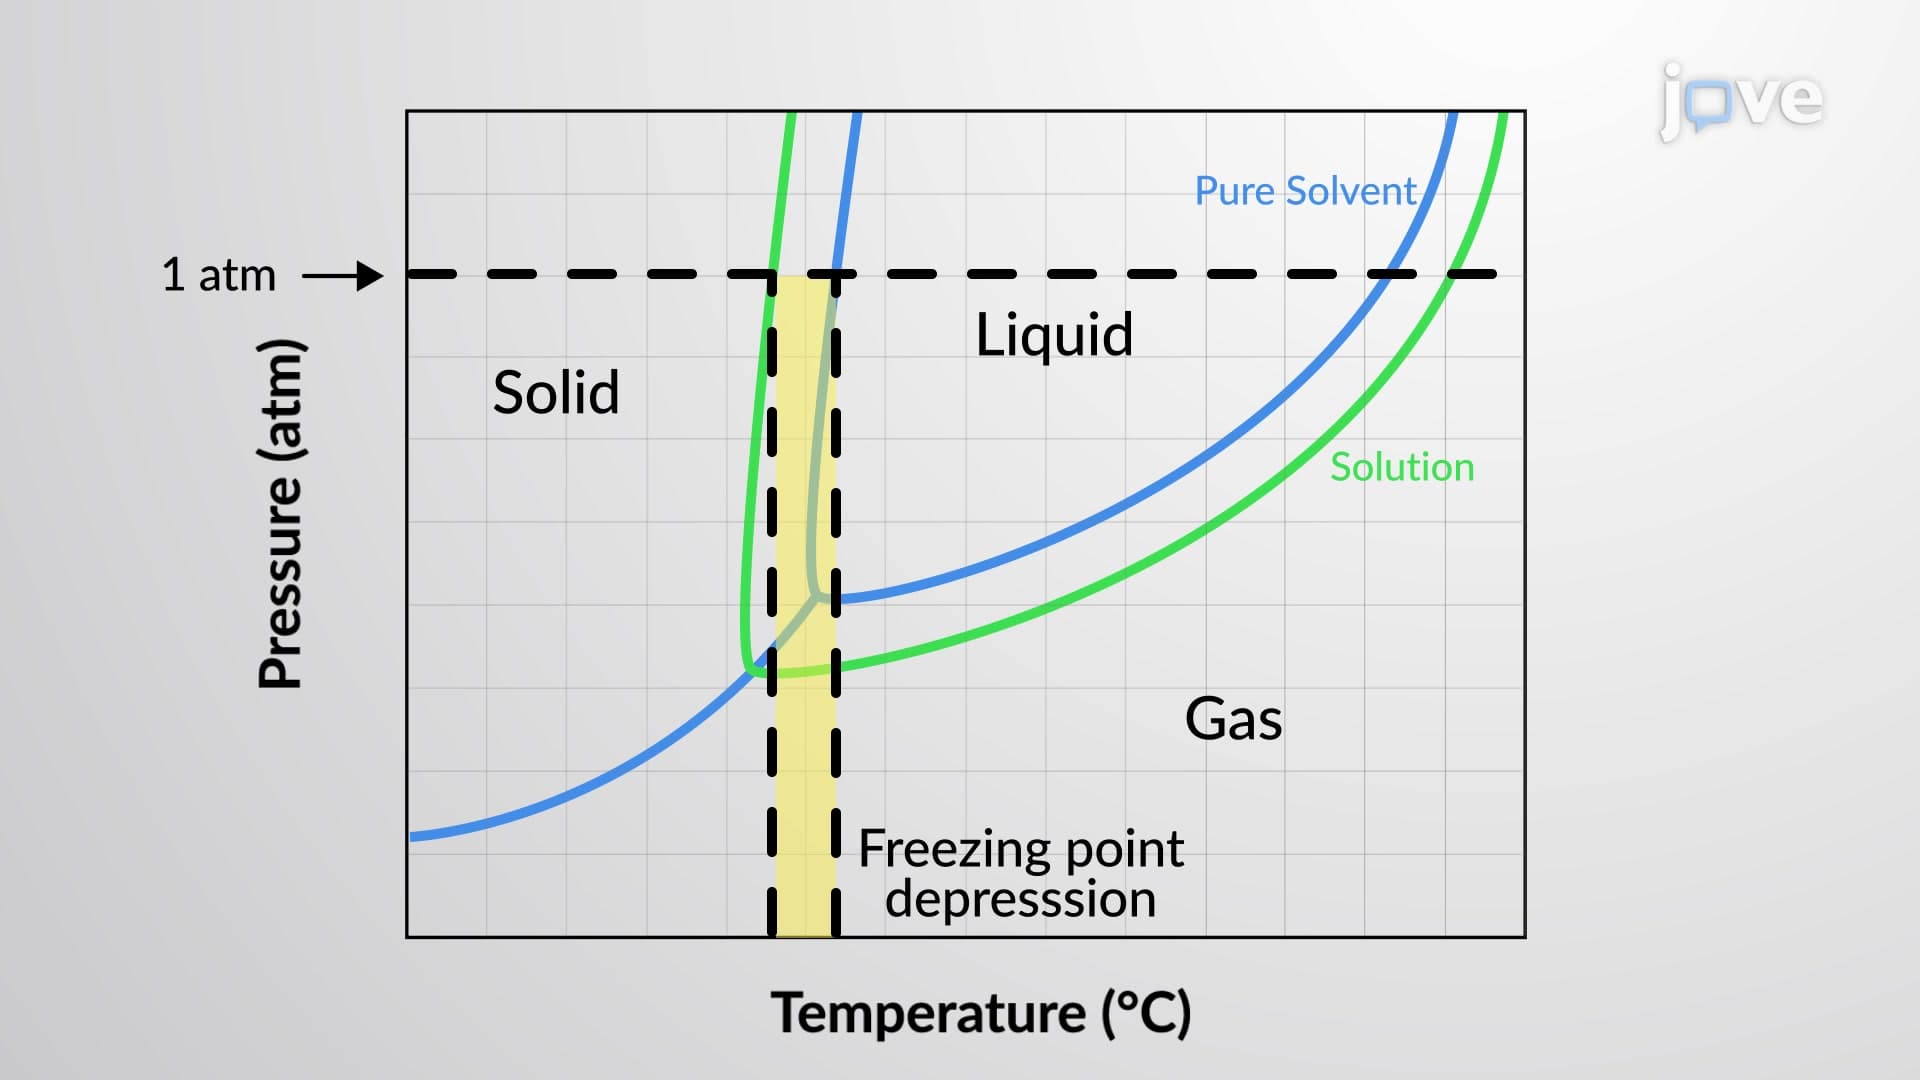
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 02:24
Predicting Reaction Outcomes
 01:20
Elevation of Intermediate Points on Vertical Curves
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...