Related Experiment Video
Updated: Feb 15, 2026
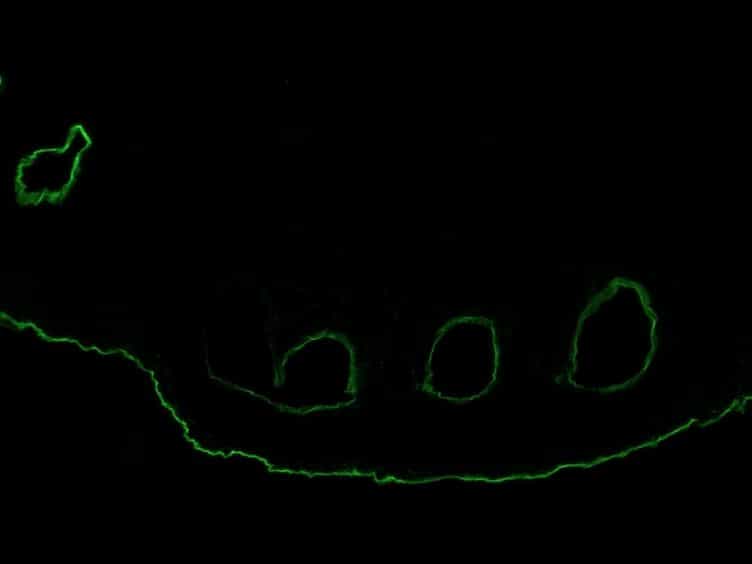

Granulocyte-dependent Autoantibody-induced Skin Blistering
Published on: October 12, 2012
Cutaneous autoimmune blistering disease during mirikizumab therapy in a patient with ulcerative colitis: a new
Lucia Centanni1,2, Fabrizio Fanizzi1,2, Ferdinando D'amico1
1Department of Gastroenterology and Endoscopy, IRCCS San Raffaele Hospital, Milan, Italy.

Abstract:
Autoimmune blistering diseases (AIBDs) may occur as adverse effects of various therapies, including biologics. Data on their association with IL-23 inhibitors in ulcerative colitis (UC) remain limited. We report the case of a 59-year-old man with UC who developed pruritic cutaneous bullae emerging within days following mirikizumab infusion. Histopathological examination and direct immunofluorescence demonstrated findings consistent with an AIBD. Following the withdrawal of mirikizumab, the residual cutaneous lesions progressively improved under corticosteroid therapy, suggesting a temporal association with the biologic exposure. This case highlights that mirikizumab may represent a potential trigger of an AIBD in susceptible individuals with UC. Clinicians should be aware of this rare but relevant complication to ensure timely recognition and management.

Related Concept Videos
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:29
Drugs for Treatment of Ulcerative Colitis in IBD
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...