Related Experiment Video
Updated: Feb 18, 2026
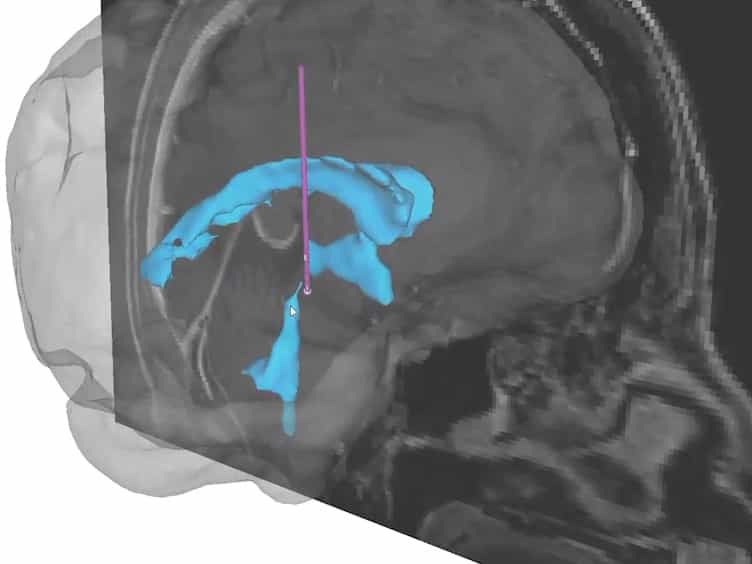

Targeting Neuronal Fiber Tracts for Deep Brain Stimulation Therapy Using Interactive, Patient-Specific Models
Published on: August 12, 2018
Deep Brain Stimulation for Post-Stroke Movement Disorders of Various Etiologies: An Individual Participant Data (IPD)
Thomas Kinfe1,2,3, Sanjay Pandey4, Martin Regensburger5,6
1Mannheim Center for Neuromodulation and Neuroprosthetics (MCNN), Department of Neurosurgery, Medical Faculty Mannheim, Heidelberg University, Mannheim, Germany.

Background:
Post-stroke movement disorders consisting of complex involuntary movement patterns with parkinsonism, dystonia, hemiballismus/hemichorea, and tremor represent a therapeutical challenge. Deep brain stimulation has been considered an effective treatment option, although it remains unclear which DBS targets should be approached.
Methods:
An individual participant data meta-analysis was conducted analyzing the efficacy (Burke Fahn Marsden Dystonia Rating Scale (BFM)-motor/-disability and the Fahn-Tolosa-Marín Scale for tremor (FTMTRS)) of pallidal (GPi) deep brain stimulation versus thalamic (VIM) versus GPi + VIM. PubMed, Embase, Cochrane Library, Ovid Medline, and Scopus were searched from 2000 to 2025. Additionally, correlation/regression analyses (age, duration of disease, stimulation parameters) were performed.
Results:
Sixteen studies including 32 patients (34.4% male; 65.6% female) were enrolled targeting the GPi (63.2%) versus VIM (23.6%) versus GPi/VIM-DBS (13.2%). Dystonia with tremor was found in 53%, dystonia with hemichorea/choreoathetosis in 50% (age at disease onset: 10 ± 18 years, age at DBS surgery: 37 ± 15 years, disease duration: 28 ± 19 years). GPi-DBS improved dystonia (BFM-motor: 6-12 months p < 0.005 and >12 months p = 0.038; BFM-disability 6-12 months p = 0.038) with no significant/relevant changes for VIM and GPi/VIM. No correlations were determined between DBS outcome and stimulation protocol and demographic characteristics. Adverse events occurred in 19%.
Conclusion:
DBS is effective for treating post-stroke movement disorders of various etiologies. Given the heterogeneity, selection, and reporting bias, the published data is limited in providing high-quality evidence. Hence, the authors advocate a multifocal DBS approach along with trial stimulation determined under a rigorous study protocol.
More Related Videos
 11:12
Controlling Parkinson's Disease With Adaptive Deep Brain Stimulation
Published on: July 16, 2014
 13:56
The Use of Magnetic Resonance Spectroscopy as a Tool for the Measurement of Bi-hemispheric Transcranial Electric Stimulation Effects on Primary Motor Cortex Metabolism
Published on: November 19, 2014