Related Experiment Video
Updated: Feb 20, 2026
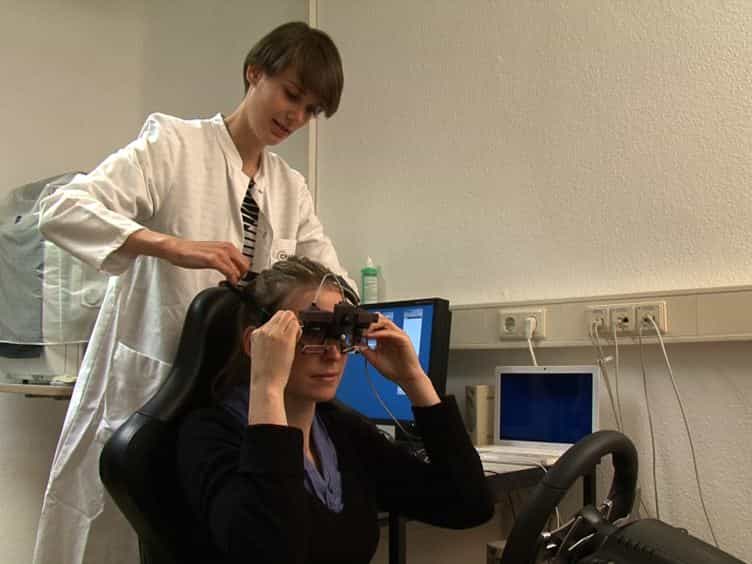

Driving Simulation in the Clinic: Testing Visual Exploratory Behavior in Daily Life Activities in Patients with Visual Field Defects
Published on: September 18, 2012
"Doctor, when can I drive?" - Can we compensate an immobilization of the right wrist while driving a car: A pilot
Falk Hilsmann1, Felix Lakomek1, Max Prost1
1Department of Orthopedic and Trauma Surgery, Medical Faculty and University Hospital Duesseldorf, Heinrich-Heine-University Duesseldorf, Duesseldorf, Germany.

Introduction:
The joints of the upper extremity are responsible for ensuring the safe movement of the body when steering and shifting gears. The impact of wrist immobilization and the subsequent movement limitations on driving ability remains inconclusively elucidated. The aim of the pilot study was to determine the range of motion required to safely operate a motor vehicle when the right wrist is immobilized. In addition, the compensators mechanisms that occur in this situation and enable safe driving to continue were to be Identified.
Materials And Methods:
A total of 20 healthy subjects were studied as part of a driving simulation in a stationary driving simulator. The right wrist was immobilized, and all subjects were required to complete a standardized driving program consisting of representative driving maneuvers (A) shifting gear, B) left turns, C) right turns). To evaluate driving performance, speed, lane keeping, and shifting time were assessed using the driving simulator. In addition, the range of motion of the upper extremity, spine, and hip were collected using the motion capture system.
Results:
The average age of the 20 healthy participants was 28.2 years, and 40% were female. The elimination of the right wrist does not result in a significant reduction in driving performance. During the act of shifting gears, a significant decrease in extension was observed in the right elbow (p = 0.002; 95% CI [-6.13, -1.57]), while a significant increase in abduction in the right shoulder joint (p = 0.008; 95% CI [-7.46, -1.28]) and flexion in the spine was observed (p = 0.011; 95% CI [-1.48, -0.22]). During a right-hand turn in the road, compensation occurs via the right elbow with a significant reduction in both maximum flexion (p = 0.008; 95% CI [2.98, 17.22]) and maximum supination (p = 0.005; 95% CI [-20.96, -4.34]). Conversely, when turning left, there is compensation via the left upper extremity: There is a significant increase in ulnar abduction of the left wrist (p = 0.03; 95% CI [-5.87, -0.33]) and minimal flexion of the left elbow (p = 0.012; 95% CI [1.22, 8.88]).
Conclusion:
Our data suggest that driving with an immobilized right wrist can be well compensated in healthy adults, although biomechanical changes in the upper extremity and spine were observed.

