Related Experiment Video
Updated: Feb 20, 2026


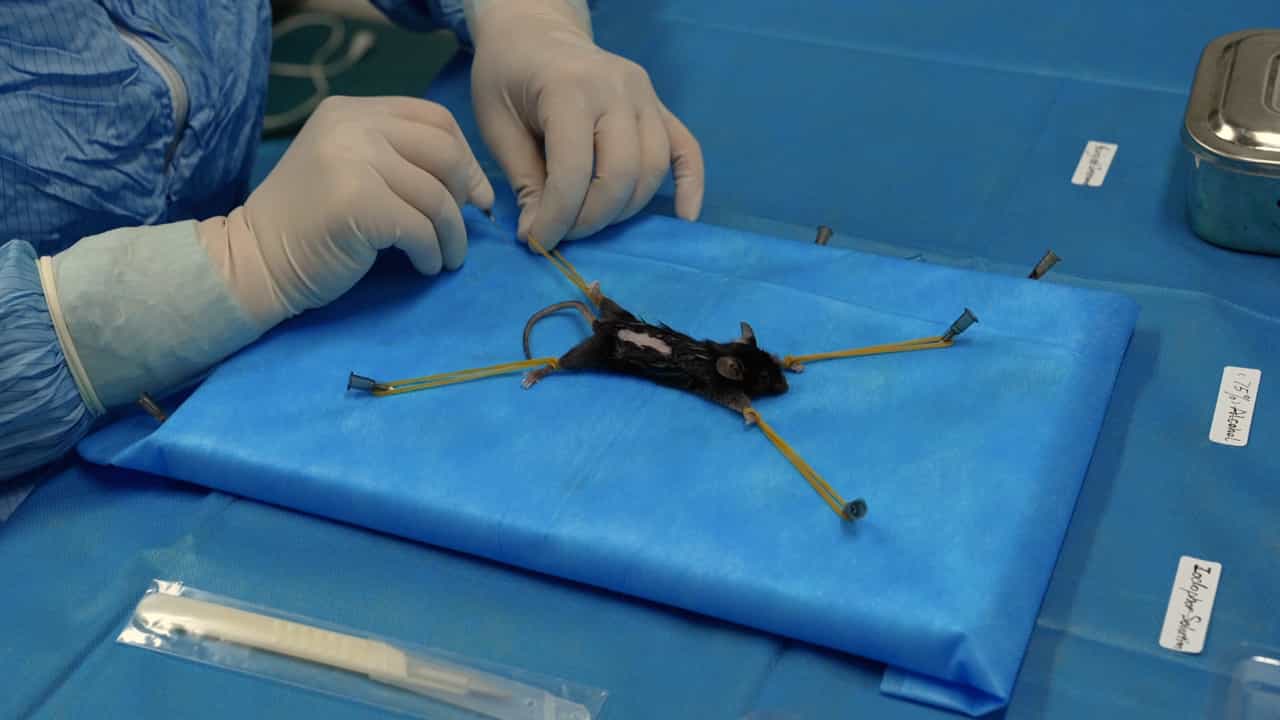
An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
Menopausal hormone therapy and long term mortality: nationwide, register based cohort study
Anders Pretzmann Mikkelsen1,2, Thomas Bergholt3,4, Øjvind Lidegaard4,5
1Department of Gynaecology and Obstetrics, Copenhagen University Hospital Herlev, 2730 Herlev, Denmark anders.mikkelsen@regionh.dk.

Objective:
To assess whether menopausal hormone therapy increases the risk of all cause mortality.
Design:
Nationwide, registry based cohort study.
Setting:
Denmark.
Participants:
Danish women born between 1950 and 1977 and alive at 45 years. Follow-up began on each woman's 45th birthday and ended on 31 July 2023. Of 969 424 eligible women, 92 619 were excluded because of thrombophilia, liver disease, arterial thrombosis or venous thrombosis, breast cancer, endometrial cancer, ovarian cancer, previous use of menopausal hormone therapy, or previous bilateral oophorectomy. Systemic menopausal hormone therapy was the intervention of interest.
Main Outcome Measures:
Death as registered in the Central Persons Register. Secondary outcomes were cause specific mortality registered in the cause of death register (cardiovascular, cancer, or other mortality). Hazard ratios were estimated using Cox regression, adjusted for age, calendar year, parity, educational degree, income group quarter (based on quartiles), country of birth, diabetes, hypercholesterolemia, hypertension, atrial fibrillation, valvular disease, heart failure, and three or more hospital contacts between 44 and 45 years of age.
Results:
Of 876 805 women, 104 086 (11.9%) redeemed a prescription for menopausal hormone therapy, and 47 594 (5.4%) died, with a median follow-up time of 14.3 years (interquartile range (IQR) 7.9-21.0 years). Women who used menopausal hormone therapy had an incidence rate of 54.9 deaths per 10 000 person years compared to 35.5 per 10 000 person years in the unexposed group, corresponding to an adjusted hazard ratio of 0.96 (95% confidence interval (CI) 0.93 to 0.98). Stratifying this by cumulative duration of menopausal hormone therapy use gave an adjusted hazard ratio after <1 years of menopausal hormone therapy of 1.01 (95% CI 0.98 to 1.05), after 1-2.9 years of use 0.94 (0.89 to 0.98), 3-4.9 years of use 0.90 (0.84 to 0.95), 5-9.9 years of use 0.89 (0.84 to 0.95), and over ≥10 years of use 0.98 (0.90 to 1.07). No unequivocal differences in cause-specific mortality were found between groups. Among the 703 women who underwent bilateral oophorectomy between 45-54 years, those who used menopausal hormone therapy experienced a 27-34% lower mortality hazard as compared to women who did not (median age at death for those who had taken menopausal hormone therapy 60.9 years (IQR 55.3-66.6 years) v 56.6 years (52.9-62.0 years) for those who had not).
Conclusions:
This nationwide cohort study did not find menopausal hormone therapy was associated with increased mortality.
More Related Videos

Related Concept Videos
 01:28
Menopause
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH...
 01:33
Hormonal Regulation
 01:40
Hormonal Regulation
 02:20
Longitudinal Research
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...