Related Experiment Video
Updated: Feb 20, 2026


Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
Distinct Phenotypes of Full-Thickness Rectal Prolapse in Women: A Comparison of Defecation-Only and Spontaneous
Zeyi Zhou1, Michelle Earley1, Sydni Au Hoy1
1Department of Surgery, Stanford University School of Medicine, Stanford, California, USA.

Background:
While some patients report full thickness rectal prolapse (RP) exclusively during defecation, others may experience it spontaneously during walking, exercise, and/or all the time. We hypothesized that patients with RP only during defecation have more preserved physiological and anatomical characteristics and aimed to identify the phenotypes of patients with various RP expression.
Methods:
A retrospective analysis of a prospectively maintained registry of women with RP (2017-2023) included clinical characteristics, MRI defecography (MRD), and high-resolution anorectal manometry (HR-ARM).
Key Results:
Of 297 patients, 147 (49%) experienced defecation-only RP, while 150 (51%) had spontaneous RP. The defecation-only RP group was younger (p < 0.001) and exhibited higher obstructive defecation syndrome (ODS) scores (p < 0.001), associated with higher rectal pressures at simulated defecation. The spontaneous RP patients had higher Wexner fecal incontinence scores (p < 0.001) and were more likely to seek medical care within 6 months of symptom onset (p = 0.006). On MRD, they had larger levator hiatus length, width, and bowl volume along with a wider anorectal angle. HR-ARM showed lower resting anal pressures (p = 0.03) and less sustained squeeze pressures (p = 0.04) in this group.
Conclusions And Inferences:
Defecation-only RP appears to represent a distinct phenotype, potentially an early stage of RP, characterized by younger age, more severe obstructive symptoms, more preserved anal sphincter function, and less pelvic floor laxity. Future research should focus on risk factors for progression to more sustained RP and the potential benefits of early intervention in patients with defecation-only RP.


Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:26
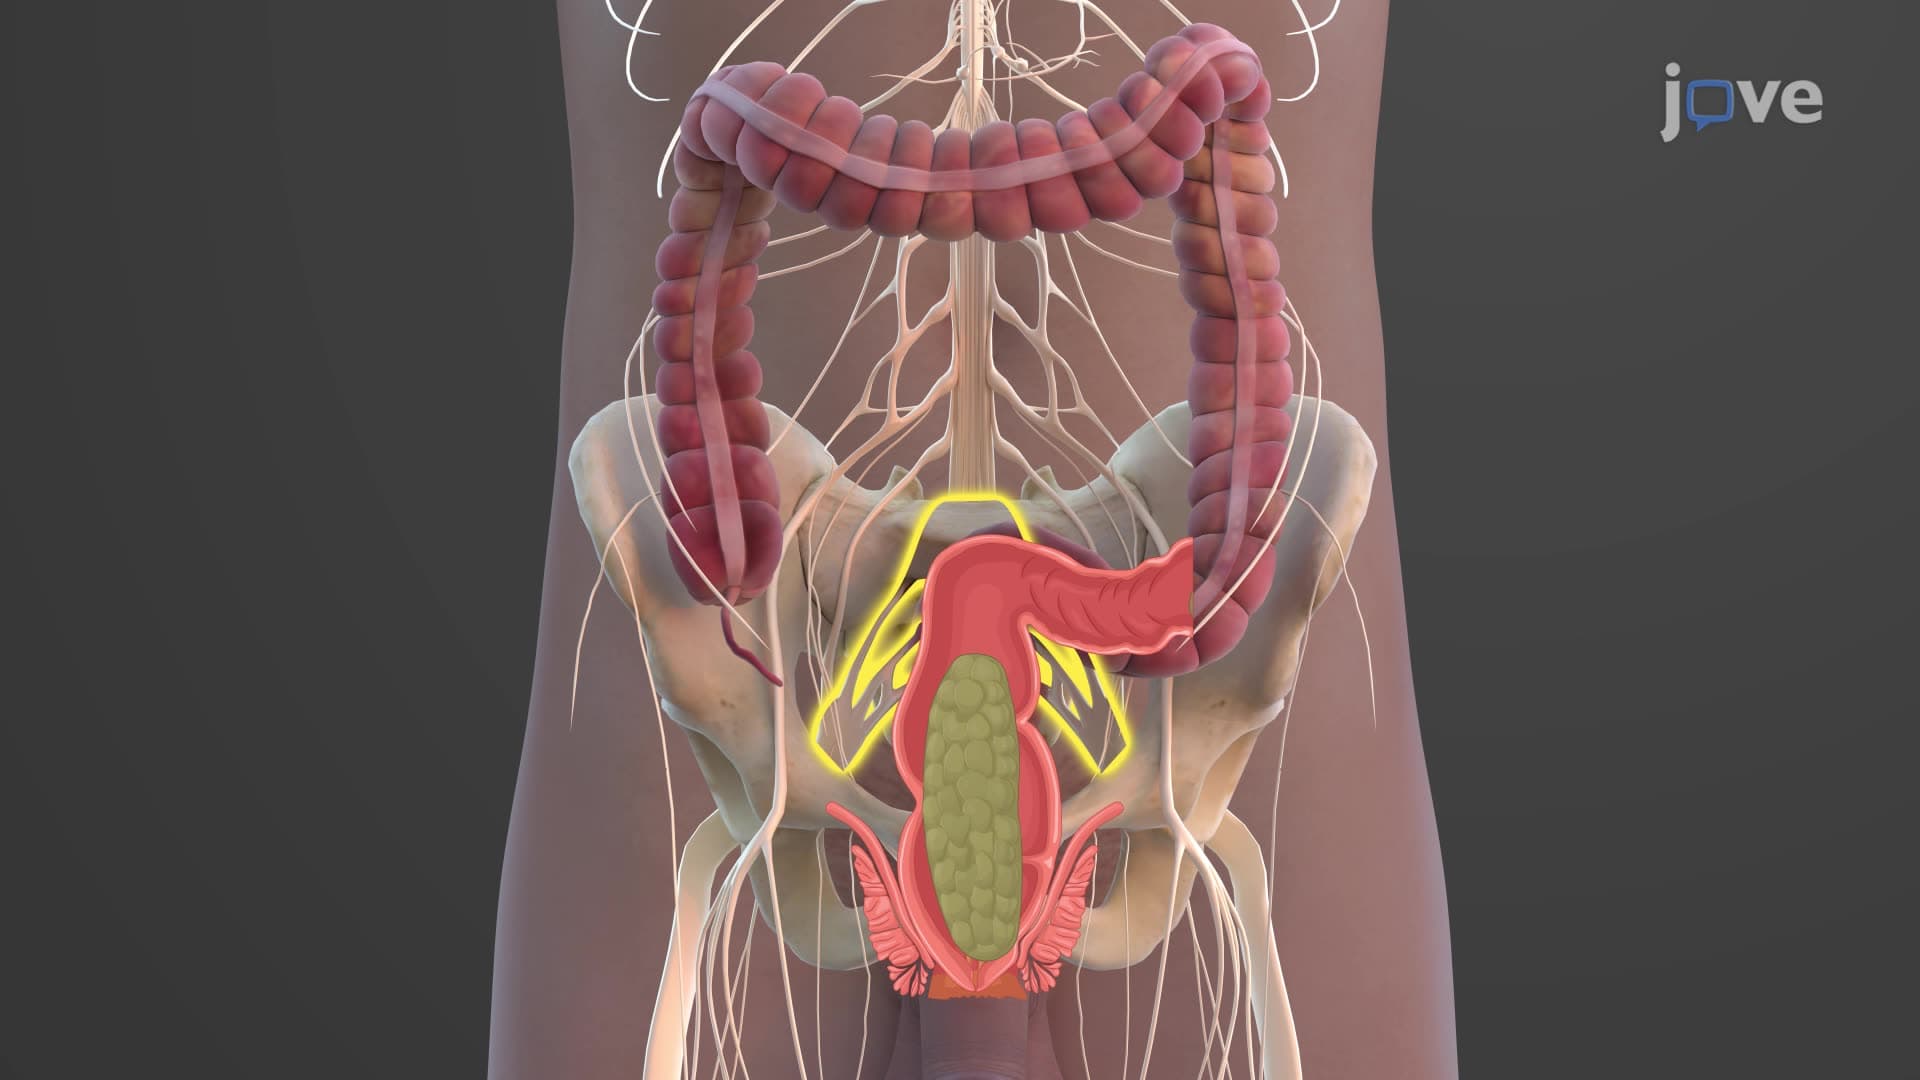
Feces Formation and Defecation
The mass peristalsis then pushes the feces into the rectum, which stretches the rectal walls to activate...
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:26
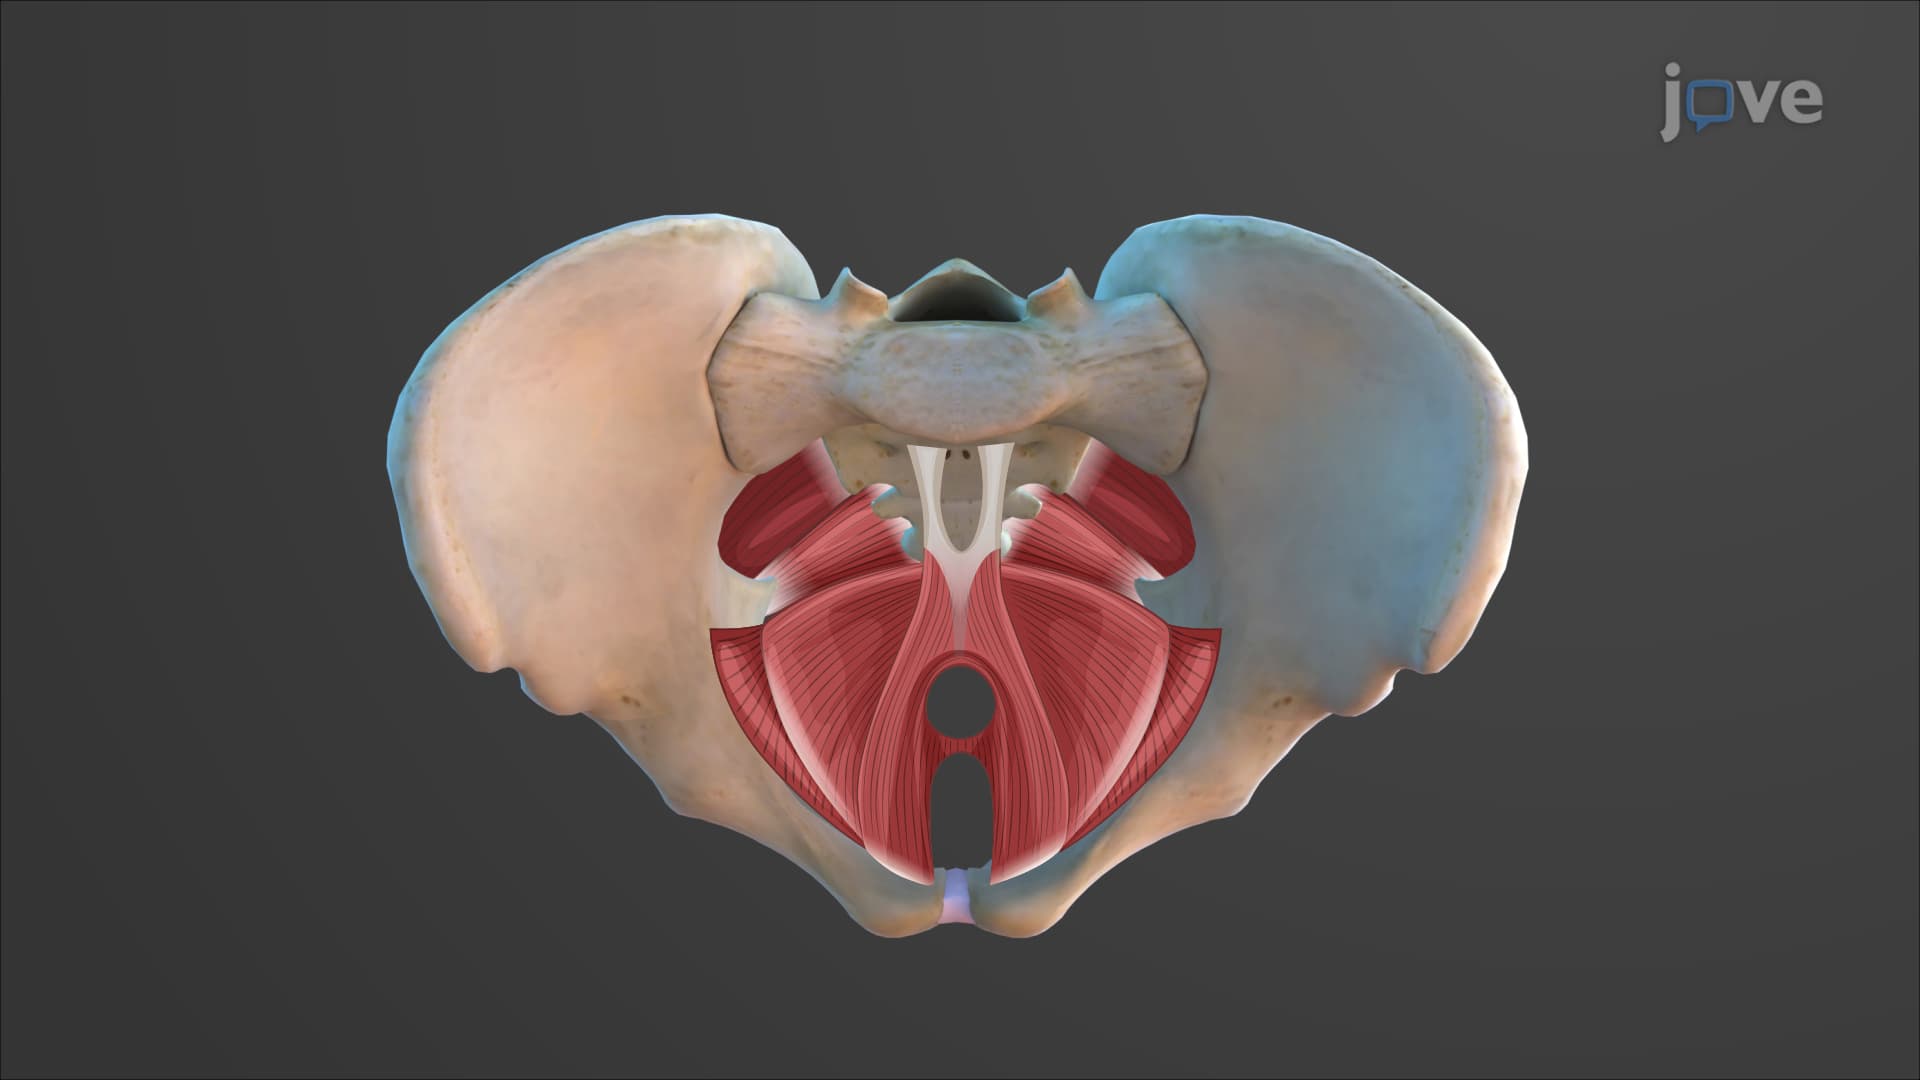
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...