Related Experiment Video
Updated: Feb 21, 2026
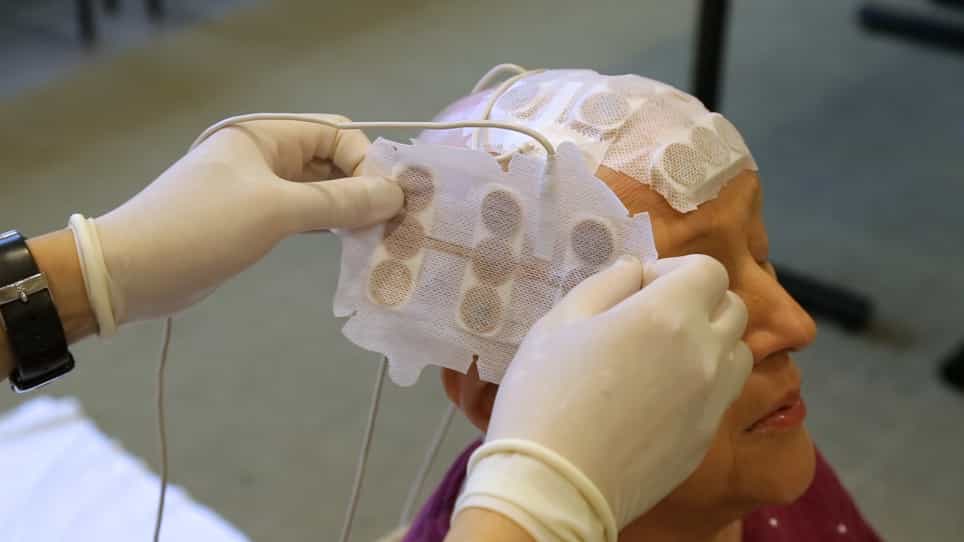
The Clinical Application of Tumor Treating Fields Therapy in Glioblastoma
Published on: April 16, 2019
Early withdrawal of systemic corticosteroid following malignant glioma craniotomy: a real-world population-based
Chia-En Wong1,2, Yu-Chen Kuo3, Pei-Wen Chen4
1Division of Neurosurgery, Department of Surgery, College of Medicine, National Cheng Kung University Hospital, National Cheng Kung University, Tainan, Taiwan.

Abstract:
BACKGROUND: Dexamethasone is commonly administered perioperatively in malignant glioma craniotomies to mitigate peritumoral edema and associated mass effects. However, prolonged steroid exposure impairs survival outcomes through immunosuppression. The optimal timing for postoperative steroid withdrawal remains unclear. This study investigates the association between early postoperative corticosteroid withdrawal and outcomes following malignant glioma craniotomy. METHODS: A retrospective cohort analysis was conducted using the TriNetX database. Propensity score matching (PSM) was performed to form two balanced groups comparing patients with early steroid withdrawal (discontinuation of within 7 days postoperatively and no reinitiation within 3 months) versus late steroid withdrawal (any steroid use between 7 days and 3 months postoperatively). Primary outcomes were survival at 6 months, 1 year, and 2 years. Secondary outcomes included perioperative complications including meningitis, cerebrospinal fluid (CSF) leak, intracranial hemorrhage, venous thromboembolism, and early reoperation. RESULTS: A total of 34,693 patients were included in the crude cohort. After PSM, 5922 patients were included in both groups. Early withdrawal of corticosteroid was associated with improved survival (6 months: HR 0.57, p < 0.001, 1 year: HR 0.65, p < 0.001, 2 years: HR 0.70, p < 0.001). Additionally, early steroid withdrawal was associated with lower incidence of meningitis (1-month: 0.4% vs. 1.3%, p < 0.001; 6-month: 0.7% vs. 2.3%, p < 0.001), CSF leak (1-month: 0.6% vs. 1.5%, p < 0.001; 6-month: 0.9% vs. 2.5%, p < 0.001), intracranial hemorrhage (1-month: 2.2% vs. 2.8%, p = 0.041; 6-month: 3.8% vs. 5.5%, p < 0.001), venous thromboembolism (1-month: 2.4% vs. 4.6%, p < 0.001; 6-month: 4.5% vs. 9.3%, p < 0.001), and early reoperation (4.9% vs. 11.3%, p < 0.001). CONCLUSIONS: In patients undergoing malignant glioma craniotomy, early postoperative steroids withdrawal was associated with improved survival and lower incidence of perioperative complications.


