How patients sleep after rotator cuff repair: a prospective analysis of pain, position, and recovery
Related Experiment Video
Updated: Feb 22, 2026
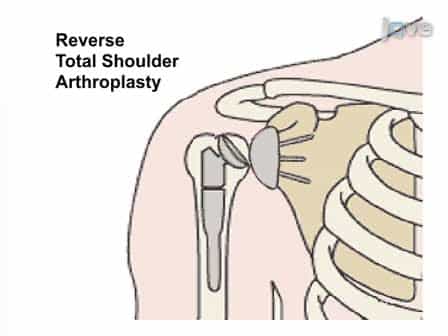
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Miguel Fiandeiro1, Adam A Rizk1, Jay M Levin1
1Rothman Orthopaedic Institute, Philadelphia, PA, USA.

Background:
Sleep disturbance is common among patients undergoing rotator cuff repair (RCR), yet the perioperative course of pain-related sleep disruption and the influence of behavioral factors are not well defined. Patients frequently ask perioperative sleep-related questions that lack evidence-based answers. This study aimed to characterize changes in sleep quality and sleeping patterns before and after RCR.
Methods:
Adults undergoing primary elective RCR at a single academic center (November 2021-October 2024) were prospectively enrolled. Surveys were completed preoperatively and at 2, 6, 12, and 24 weeks postoperatively. The primary outcome was the Pain and Sleep Questionnaire 3-item index (PSQ-3; 0-300). Secondary measures included the Sleep Hygiene Index, sleep position, sling use, and 24-hour visual analog scale (VAS) for pain. Analyses used chi-square/Fisher's tests, Kruskal-Wallis/analysis of variance, and Spearman correlations, all with Bonferroni correction to evaluate sleep position changes and candidate predictors. Primary mixed-effects models used 2 weeks as the reference time and preoperative PSQ-3 and VAS scores as a covariate to identify predictors of postoperative PSQ-3 and VAS pain. Secondary models used preoperative scores as the reference to determine when outcomes improved beyond baseline.
Results:
Sixty-three patients were enrolled; 50 (51 shoulders) completed final follow-up. Mean age was 59.9 ± 9.7 years, body mass index was 31.4 ± 6.0 kg/m2, baseline Sleep Hygiene Index was 10.2 ± 5.9, and PSQ-3 of 130.6 ± 99.1. At 2 weeks, back sleeping increased (85% from 39.2%, P < .001) and side sleeping declined (27.5% from 64.7%, P = .011). By 6 weeks, side sleeping partially recovered; by 24 weeks, sleep positions resembled baseline. Mixed-effects modeling demonstrated worse PSQ-3 at 2 weeks (β = +30.98, P = .039), followed by significant improvement below baseline by 6 weeks (β = -32.64, P = .030), 12 weeks (β = -56.20, P < .001), and 24 weeks (β = -92.55, P < .001). By 24 weeks, 55% of patients reported no nighttime sleep disturbance (PSQ-3 = 0). Nicotine use and preoperative side sleeping were independently associated with worse postoperative PSQ-3 and VAS scores. Additionally, Workers' Compensation status and higher preoperative pain predicted higher postoperative VAS.
Conclusions:
Sleep after RCR worsens transiently but improves by 6 weeks, with continued improvement by 12 weeks and 24 weeks. Most patients resume preoperative sleep positions by 6 months. Nicotine use and preoperative side sleeping are predictors of increased pain-related awakenings during RCR recovery.
More Related Videos
 05:25
Knotless Independent Double-Row Repair and Biceps Augmentation for Anterosuperior Rotator Cuff Tears
Published on: January 23, 2026
 07:44
Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
Related Concept Videos
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:15
REM Sleep Behavior Disorder
RBD is significantly associated with...