Related Experiment Video
Updated: Feb 24, 2026


Testing Acetylcholine Followed by Adenosine for Invasive Diagnosis of Coronary Vasomotor Disorders
Published on: February 3, 2021
Clinical determinants of agreement and discordance between stress SPECT and invasive coronary angiography
Matan Danon1, Nitzan Shabat Cohen1, Saar Ashri2
1Adelson School of Medicine, Ariel University, Ariel, Israel.

Insights
Stress single-photon emission computed tomography (SPECT) myocardial perfusion imaging shows variable agreement with invasive coronary angiography (ICA) for diagnosing coronary artery disease (CAD). Clinical factors significantly influence diagnostic agreement, improving risk stratification when combined with SPECT results.
Area of Science:
- Cardiology
- Nuclear Medicine
- Diagnostic Imaging
Background:
- Stress single-photon emission computed tomography (SPECT) myocardial perfusion imaging is a non-invasive tool for diagnosing coronary artery disease (CAD).
- SPECT imaging often produces inconclusive results, necessitating further investigation or clarification.
- Understanding the agreement and discordance between SPECT and invasive coronary angiography (ICA) is crucial for accurate diagnosis and risk stratification.
Purpose of the Study:
- To characterize the patterns of agreement and discordance between stress SPECT and ICA in patients with suspected CAD.
- To identify clinical and demographic factors associated with diagnostic agreement or disagreement.
- To evaluate the potential of incorporating clinical variables with SPECT findings for improved risk stratification.
Main Methods:
- Retrospective analysis of 915 patients with suspected CAD who underwent stress SPECT followed by ICA within three months.
- Extraction of clinical, demographic, and imaging data from medical records.
- Univariate and multivariable logistic regression analyses to identify variables associated with diagnostic agreement and to develop a predictive model.
Main Results:
- Diagnostic agreement between stress SPECT and ICA was observed in 68.2% of patients.
- Factors associated with agreement included nitrates, antiplatelet therapy, renal failure, and type II diabetes mellitus.
- Female sex, smoking, and higher BMI were associated with disagreement. The multivariable model combining SPECT with clinical factors improved discrimination (AUC 0.72 vs. 0.54).
Conclusions:
- Clinical factors are significantly associated with the agreement between stress SPECT and ICA.
- Integrating clinical context with SPECT findings can enhance diagnostic accuracy and inform risk stratification for CAD.
- This approach may help optimize patient management and reduce reliance on invasive procedures when results are equivocal.
Background:
Stress single-photon emission computed tomography (SPECT) myocardial perfusion imaging offers a non-invasive alternative for invasive coronary angiography (ICA) in diagnosing coronary artery disease (CAD), however often yields inconclusive results. This study aimed to characterize patterns of agreement and discordance between stress SPECT and ICA, and to evaluate potential risk stratification.
Methods:
We retrospectively analyzed 915 patients with suspected CAD who underwent stress SPECT followed by ICA within three months (enrollment: 2019-2020). Clinical, demographic, and imaging data were extracted from medical records. Variables associated with diagnostic agreement were identified using univariate logistic regression. A predictive model combining SPECT results with clinical variables was developed using backward stepwise logistic regression and evaluated by AUC-ROC.
Results:
Diagnostic agreement between stress SPECT and ICA was observed in 624 patients (68.2%), while 291 patients (31.8%) demonstrated discordant results. Agreement was associated with use of nitrates (OR 3.18, 95% CI 1.31-7.73), antiplatelet therapy (OR 2.57, 95% CI 1.86-3.56), renal failure (OR 2.34, 95% CI 1.43-3.84), and type II diabetes mellitus (OR 1.78, 95% CI 1.28-2.48), whereas female sex (OR 0.50, 95% CI 0.34-0.73), smoking (OR 0.72, 95% CI 0.50-1.03), and higher body mass index (BMI; OR 0.95 per kg/m², 95% CI 0.92-0.99) were associated with disagreement. The final multivariable model included stress SPECT results, sex, BMI, smoking status, serum creatinine, renal failure, type II diabetes mellitus, and use of antiplatelets and nitrates and demonstrated improved discrimination compared with SPECT alone (AUC 0.72 vs. 0.54, p < 0.001).
Conclusion:
In this exploratory study, clinical factors were associated with an agreement between stress SPECT and ICA. Incorporating clinical context alongside SPECT findings may help inform risk stratification.
More Related Videos


Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:29
Angina III: Clinical Manifestations and Assessment
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:26
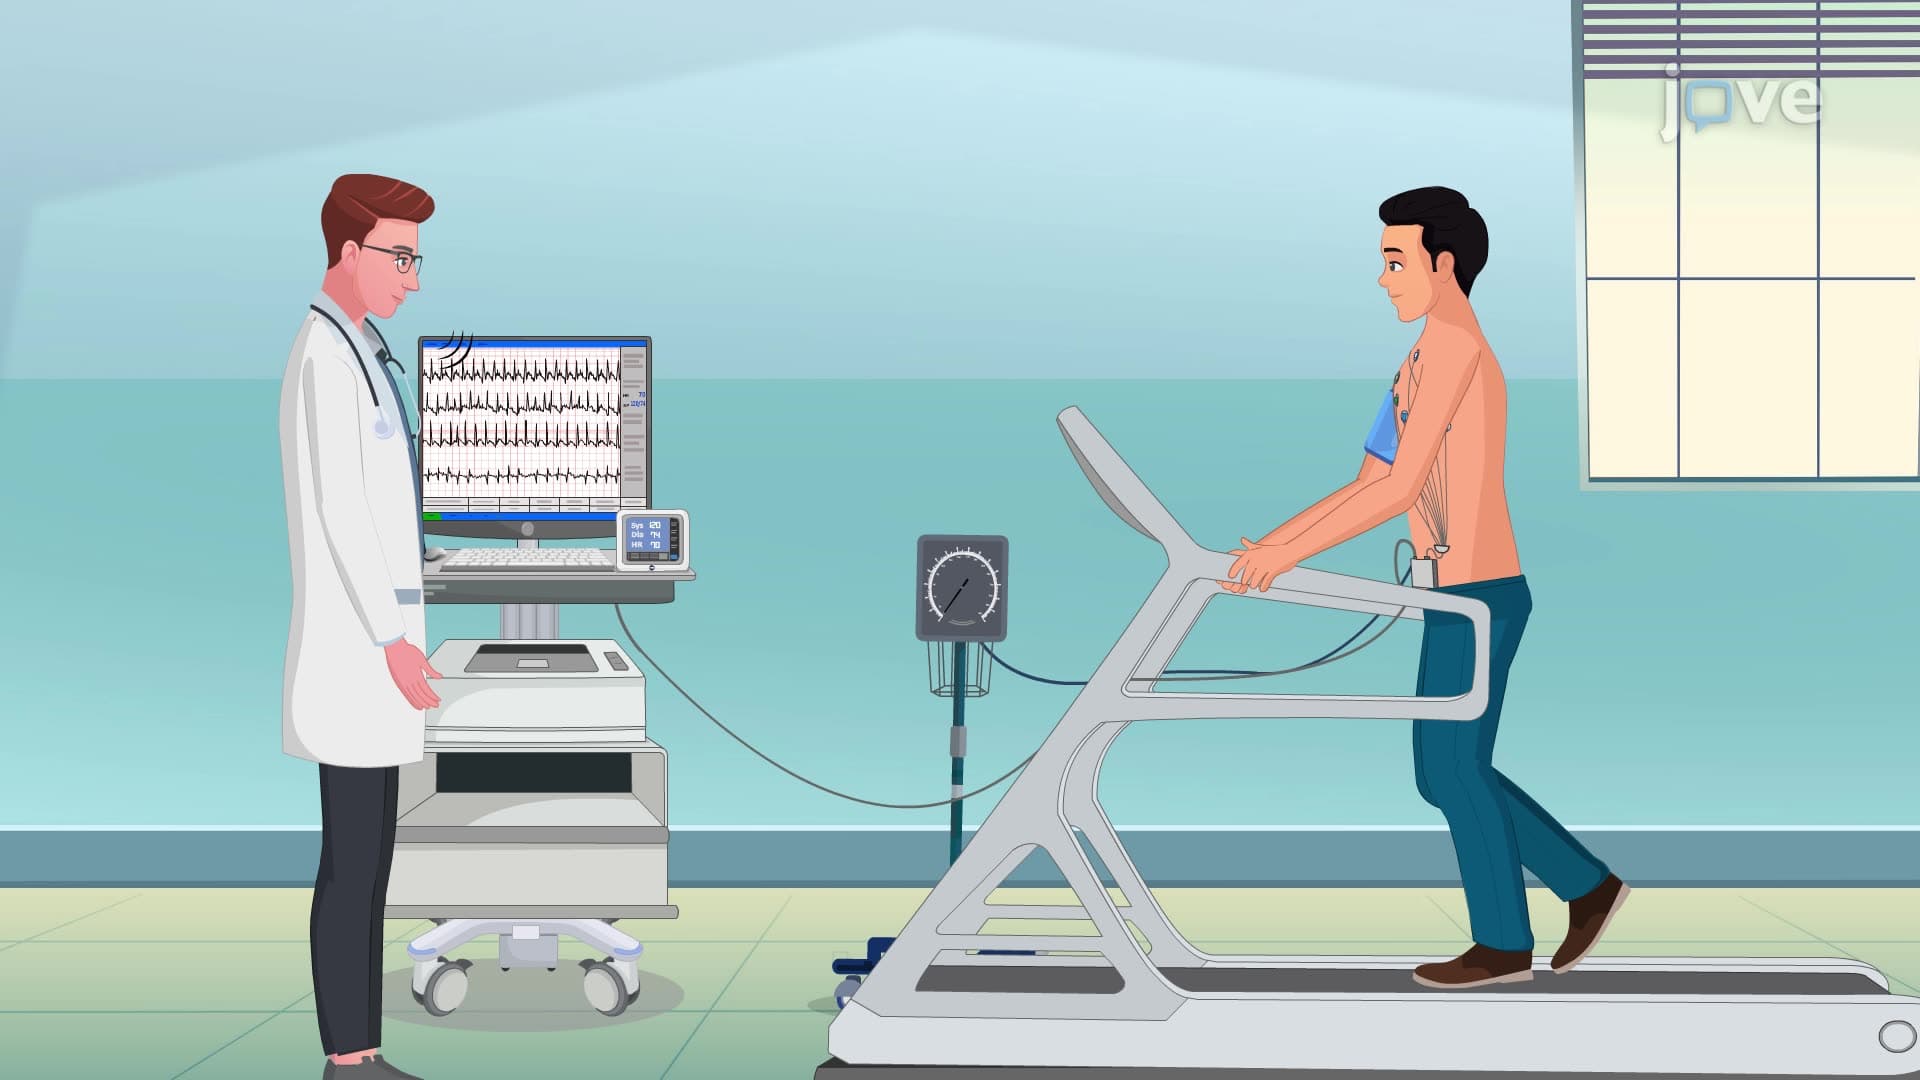
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:30
Acute Coronary Syndrome I: Introduction