Related Experiment Video
Updated: May 6, 2026
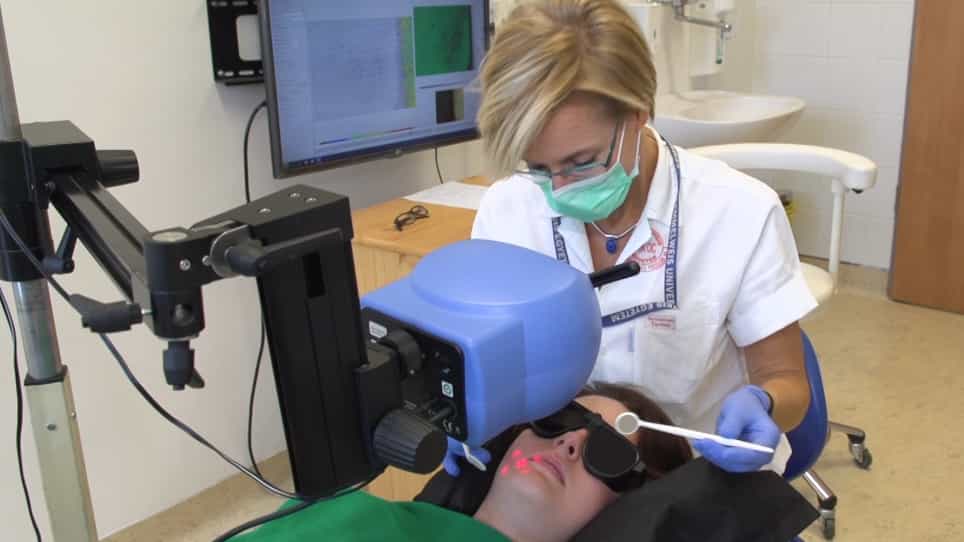

A Novel Approach to Monitoring Graft Neovascularization in the Human Gingiva
Published on: January 12, 2019
Success in Gingival Recession Coverage: Prognostic Indicators From Private Practice
Michael Saminsky1, Liat Chaushu1, Benjamin R Coyac2
1Department of Periodontology and Oral Implantology, Goldschleger School of Dental Medicine, Gray Faculty of Medical and Health Sciences, Tel Aviv University, Tel Aviv, Israel, tau.ac.il.

Purpose:
To identify parameters associated with successful root coverage, defined as 70% and 50% root coverage in Miller Class I-II/RT1 and III/RT2 defects, respectively, within periodontal office settings.
Methods:
Dental records of patients treated for gingival recessions were screened retrospectively. General health parameters, smoking status, pre and posttreatment recession depth (RD), that is, RD and residual RD (RRD), respectively, recession width (RW), keratinized tissue (KT) width, and clinical attachment loss (CAL) were extracted. Logistic regression linear mixed-effects models were used to identify correlations between patient- and treatment-specific variables and the success of gingival recession defect coverage up to 180 months.
Results:
Records from 105 surgically treated recessions (82 Miller Class-I-II/RT1, 23 Miller Class-III/RT2) in 56 patients (46 females, 10 males) were retrieved. Mean follow-up was 3.52 (1-15) years post-surgery. Smoking, Miller Class II/RT1 and III/RT2, and lateral teeth were negatively associated with treatment success (effect sizes: smoking -21.0, Miller II/RT1 -21.5, Miller III/RT2 -21.4, lateral -21.1; all p < 0.001), whereas canines and first premolars were positively associated with successful coverage (effect sizes: canine 1.71, first premolar 10.31; all p < 0.001). Univariate linear regression revealed that initial RD, RW, and Miller Class III/RT2 were significantly associated with higher CAL gain (estimates: RD 0.71, RW 0.65, Miller III/RT2 1.14), higher KT gain (estimates: RD 0.34, RW 0.33, Miller III/RT2 0.99), and lower RRD (estimates: Miller II/RT1 0.72, Miller III/RT2 0.92, RD 0.28, RW 0.30) (all p < 0.05).
Conclusions:
Long-term root coverage is negatively correlated with smoking, Miller Class II-III/RT1-2 recessions, and lateral teeth but positively related to canines and first premolars. CAL/KT gain and RRD are positively influenced by initial RD, RW, and Miller Class-III/RT2.
More Related Videos
 06:06
Adjunctive Diode Laser Therapy and Probiotic Lactobacillus Therapy in the Treatment of Periodontitis and Peri-Implant Disease
Published on: May 9, 2022
 06:36
Effects of Mechanical Methods Used in Peri-implantitis Treatment on Implant Surface Decontamination and Roughness
Published on: March 14, 2025
Related Concept Videos
 01:52
Regression Toward the Mean
 02:05
Self-Presentation: Self-Monitoring and Self-Handicapping
 01:12
Hindsight Biases
 01:15
Teeth
In the bud stage, the tooth germ (an aggregation of cells) starts to form in the developing jawbone. During the cap stage, the tooth germ differentiates into enamel organ, dental papilla, and dental sac, which will later develop into the tooth's enamel, dentin...
 01:25
First Derivative Test: Problem Solving
 01:27
Protecting Self-Esteem