Related Experiment Video
Updated: Feb 25, 2026
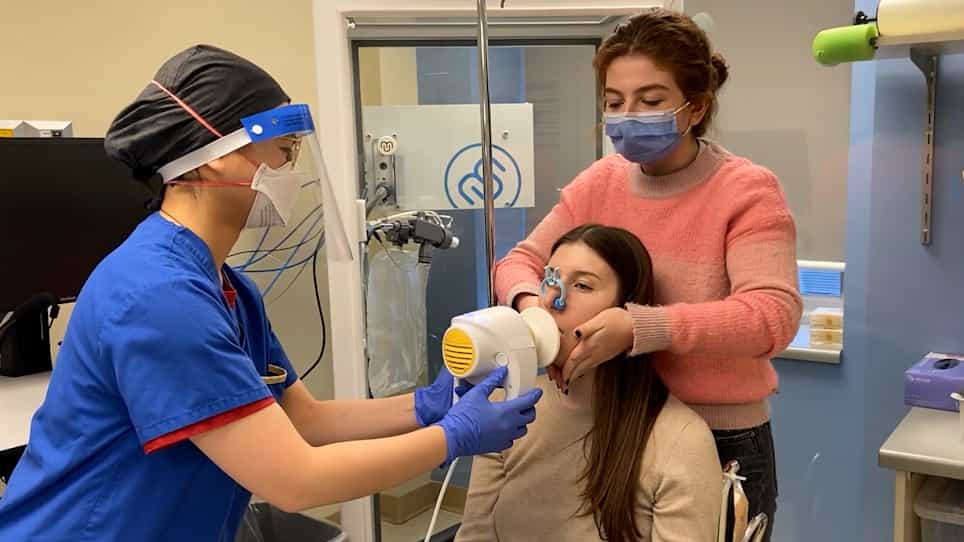
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Impact of breathing frequency on respiratory oscillometry measurements: a randomised cross-over and observational
Ben Knox-Brown1,2, Olga Carozzo3, Karl P Sylvester3,2
1Cambridge University Hospitals NHS Foundation Trust, Cambridge, UK benjamin.knox-brown@nhs.net.

Introduction:
The impact of breathing frequency on respiratory oscillometry measurements is unknown. We aimed to investigate the impact of different breathing frequencies in patients with asthma.
Method:
We recruited patients from the severe asthma clinic at Cambridge University Hospitals. Using a randomised-crossover design, participants performed the forced oscillation technique at three different breathing frequencies (15, 30, 40 bpm) in a randomised order for each participant. A metronome was used to ensure the correct breathing frequency. Analysis of variance (ANOVA) and Friedman tests were utilised to assess the significance of any differences across the breathing frequencies. We then leveraged cross-sectional data from asthma patients who performed respiratory oscillometry and investigated the determinants of self-selected breathing frequency using multivariable linear regression.
Results:
We recruited 59 patients. Mean age 54.1 years, 58% female, median forced expiratory volume in 1 s (FEV1)/FVC z-score -2.56 (-3.26 to -1.96). As breathing frequency increased from 15 bpm to 40 bpm, there was a significant reduction (-8.6%, p<0.001) in total airway resistance (Rrs at 5 Hz), which was not mediated by changes in tidal volume or flow rate. There was also a significant reduction (-14.9%, p<0.001) in Delta R5-R19, and an increase (+10.9%, p=0.081) in reactance (Xrs at 5 Hz). At higher breathing frequencies, 5% of study participants were reclassified as having respiratory oscillometry measurements within normal limits. Data from 796 asthma patients were extracted for the cross-sectional analysis. The median (range) self-selected breathing frequency was 16.55 bpm (8.0, 42.0). Demographic data and lung function explained 23.5% of the variation in breathing frequency.
Conclusion:
Higher breathing frequencies significantly reduce total Rrs . When performing respiratory oscillometry, breathing frequency should be controlled at approximately 15 bpm to reduce risk of misclassification.
Related Concept Videos
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is...
 01:26
Respiratory Volumes and Capacities I
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:24
Factors Affecting Respiration
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...