Related Experiment Video
Updated: Jul 17, 2026


Mobile Game-based Virtual Reality Program for Upper Extremity Stroke Rehabilitation
Published on: March 8, 2018
Comparative effectiveness of neuromuscular, virtual reality, proprioceptive, blood flow restriction and conventional
Binshan Zhao1, Wei Zhao1, Lianxu Chen2
1School of Physical Education, Northwest Normal University, Lanzhou, China.

Purpose:
Quadriceps atrophy and post-operative pain are common following anterior cruciate ligament reconstruction (ACLR) and can hinder functional recovery. This study aimed to systematically compare the effectiveness of neuromuscular training (NMT), virtual reality training (VRT), proprioceptive training (PT), blood flow restriction training (BFRT) and conventional rehabilitation training (CRT) in individuals undergoing rehabilitation after ACLR.
Methods:
A systematic review and network meta-analysis (NMA) were conducted in accordance with PRISMA-NMA guidelines. Six databases (PubMed, EMBASE, Cochrane Library, Web of Science, CNKI and Wanfang) were searched for randomized controlled trials (RCTs) published up to 1 May 2025. Risk of bias was assessed using the Cochrane RoB 2.0 tool. A frequentist NMA was performed in Stata 17.0MP to estimate standardized mean differences (SMDs) and 95% confidence intervals (CIs). Interventions were ranked using surface under the cumulative ranking curve (SUCRA) values. The certainty of evidence was appraised using the CINeMA framework.
Results:
Twenty-two RCTs involving 972 participants (mean age 23-39 years) were included. Compared with CRT, VRT showed favourable outcomes in visual analogue scale for pain (SMD = -0.72, 95% CI = [-1.22 to -0.22], SUCRA = 86.5%), functional hop tests (SMD = 1.26, 95% CI = [0.46-2.05], SUCRA = 97.5%) and isokinetic muscle strength (60°/s) (SMD = 2.24, 95% CI = [1.28-3.20], SUCRA = 99.6%). BFRT also outperformed CRT in several outcomes, including the International Knee Documentation Committee Subjective Knee Evaluation Form (SMD = 1.37, 95% CI = [0.77-1.96], SUCRA = 81.8%), Lysholm Score (SMD = 1.07, 95% CI = [0.16-1.97], SUCRA = 74.7%) and knee range of motion (SMD = 1.42, 95% CI = [0.80-2.04], SUCRA = 99.1%), with relatively high SUCRA values. Compared with CRT, NMT demonstrated modest improvements in the Functional Hop Tests (SMD = 0.29) and the Lysholm Score (SMD = 1.00). Certainty of evidence ranged from moderate to low, primarily due to imprecision and risk of bias.
Conclusions:
VRT and BFRT may offer benefits across several domains of post-operative rehabilitation following ACLR, with NMT also showing potential. However, given the limitations in evidence certainty, further high-quality RCTs are warranted to confirm these findings and inform clinical practice.
Level Of Evidence:
Level I.
More Related Videos
 05:07
Author Spotlight: Implementing the Enhanced Recovery After Surgery Concept in Rehabilitation Following Anterior Cruciate Ligament Reconstruction
Published on: March 1, 2024
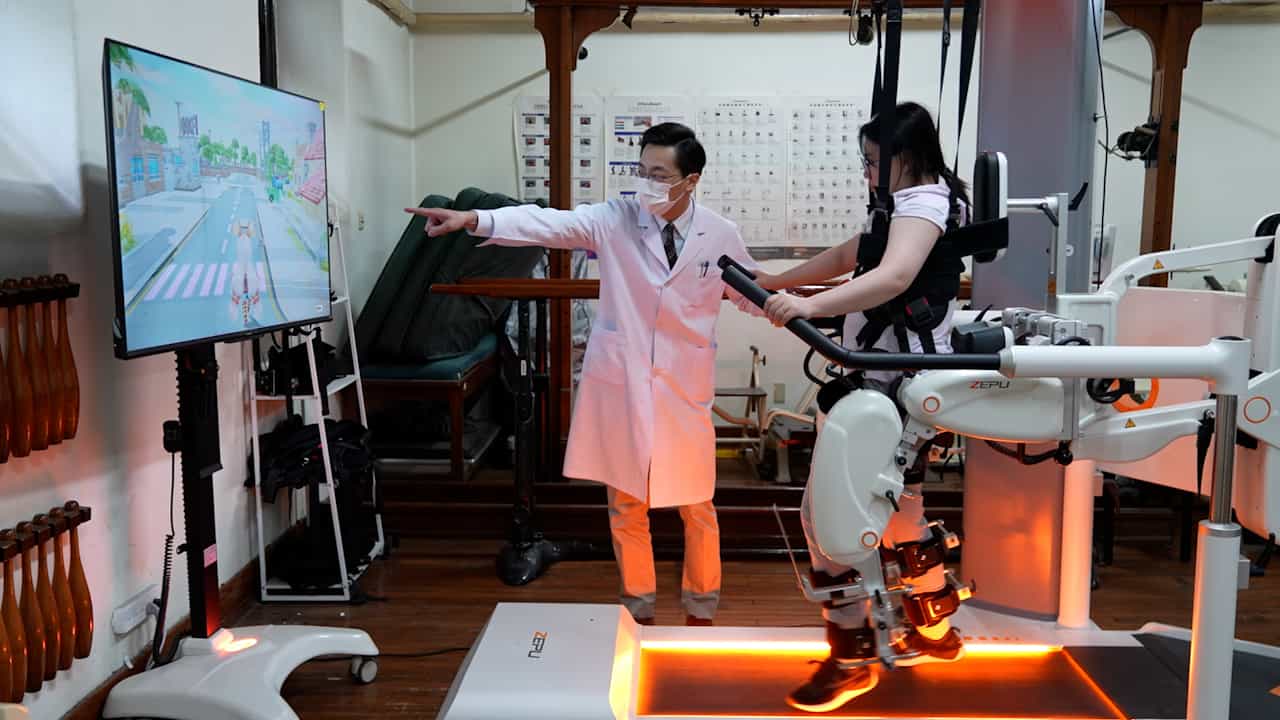 06:00
A Rehabilitation Program of Exoskeleton-assisted Body Weight-Supported Treadmill Training with Non-immersive Virtual Reality for Stroke Patients
Published on: May 16, 2025
