Related Experiment Video
Updated: Feb 28, 2026
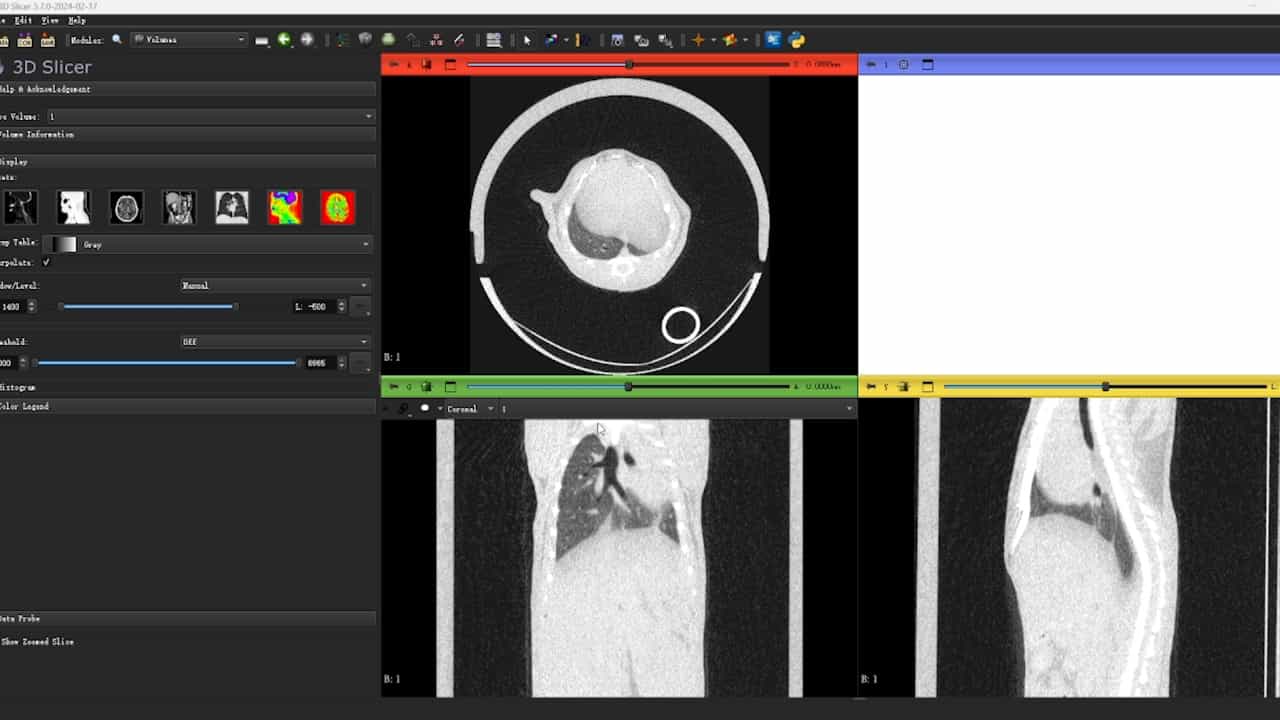

Unilateral Lung Volume Analysis Using Micro-CT for Enhanced Assessment of Pulmonary Fibrosis in Preclinical Models
Published on: June 20, 2025
Understanding Pulmonary Fibrosis in Pediatric Interstitial Lung Disease: A Comprehensive Analysis
Handan Kekec1, Ayse Tana Aslan1, Ismail Akdulum2
1Department of Pediatric Pulmonology, Gazi University Faculty of Medicine, Ankara, Turkey.

Insights
Pulmonary fibrosis (PF) is common in childhood interstitial lung diseases (chILD) and increases with age. Early detection is crucial, especially in DPLD-A disorders, as PF impacts lung function.
Area of Science:
- Pediatric Pulmonology
- Rare Diseases
- Radiology
Background:
- Childhood interstitial lung diseases (chILD) are rare, chronic respiratory conditions.
- Pulmonary fibrosis (PF) is a severe complication associated with mortality in chILD.
- Understanding PF prevalence and characteristics in chILD is critical for patient outcomes.
Purpose of the Study:
- To determine the prevalence and radiologic spectrum of PF in children with chILD.
- To investigate the association between PF and pulmonary function and clinical characteristics.
- To identify risk factors for PF development in chILD patients.
Main Methods:
- A multicenter, retrospective observational cohort study utilizing data from the chILD-TR (as of January 2024).
- Chest CT scans were reviewed by an experienced radiologist for PF findings.
- Patients were grouped based on the presence or absence of PF, with subsequent clinical and demographic data analysis.
Main Results:
- PF findings were present in 183 of 404 chILD patients, with reticular abnormalities being most common (34.9%).
- Patients with PF were older and had lower weight z-scores; DLCO% was significantly lower in the PF group.
- PF was more prevalent in Diffuse Pediatric Lung Disease-A (DPLD-A) disorders compared to DPLD-B.
Conclusions:
- PF is a frequent complication in chILD, with prevalence increasing with age.
- Children with DPLD-A disorders, characterized by surfactant dysfunction or alveolar developmental issues, are at higher risk for PF.
- Lower DLCO, DPLD-A classification, and older age are associated with a higher likelihood of PF in chILD.
Background:
Childhood interstitial lung diseases (chILDs) encompass a wide range of rare, chronic respiratory disorders, with pulmonary fibrosis (PF) being the clinical entity closely associated with mortality and morbidity.
Research Question:
What is the prevalence and radiologic spectrum of PF in children with chILD, and how is it associated with pulmonary function and clinical characteristics?
Study Design And Methods:
This multicenter, retrospective observational cohort study used data from the Turkish Childhood Interstitial Lung Disease Registry as of January 2024. An experienced radiologist reviewed the chest CT scans for PF findings. Patients were divided into 2 groups based on the presence or absence of PF findings, and their clinical and demographic data were analyzed.
Results:
A total of 404 patients (47.5% female) from 25 centers were included. The median age was 137 months (interquartile range [IQR], 24-376 months). The median z score for weight was -1.02 (IQR, -8.8 to 6.88), and the median z score for height was -0.59 (IQR, -7 to 6.45). The median FEV1 was 68% (IQR, 16%-127%), and the median diffusion capacity of the lungs for carbon monoxide (Dlco) was 66% (IQR, 21%-132%). The PF findings were as follows: reticular abnormalities, 34.9% of patients; cystic abnormalities, 21% of patients; traction bronchiectasis, 19.8% of patients; architectural distortion, 14.4% of patients; and honeycombing, 2.5% of patients. Two groups were compared based on the presence (n = 183) or absence (n = 221) of PF findings; the group with fibrotic findings showed a higher age and lower z score for weight (P < .05). Although no differences were found in PFT parameters between groups (P > .05), Dlco was lower in the fibrotic group (P = .015). The prevalence of PF was higher in patients with diffuse parenchymal lung disease (DPLD) group A disorders than in those with DPLD group B (P = .014).
Interpretation:
Our results show that PF is a common complication in chILD and becomes more pronounced with age, underscoring the importance of early detection. The higher rate of PF findings in patients with DPLD-A disorders suggests that children with surfactant dysfunction or alveolar developmental abnormalities may be at an increased risk of PF developing. PF may be more common in children with a lower Dlco score, with a DPLD-A disorder, or of an older age.


Related Concept Videos
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History