Related Experiment Video
Updated: Feb 28, 2026
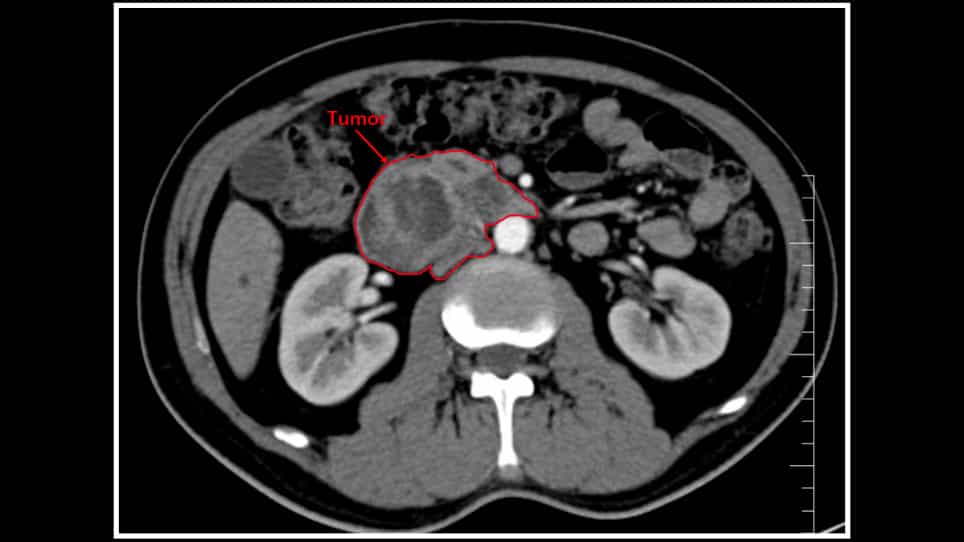

Management of the Uncinate Process in No-Touch Laparoscopic Pancreaticoduodenectomy
Published on: May 5, 2023
Epidemiology and Management of Postoperative Infections in Hepatectomy and Pancreaticoduodenectomy
Angelie Pathak1, Hina Patel1, Jason Zar1
1Department of Translational Research, College of Osteopathic Medicine of the Pacific, Western University of Health Sciences, Pomona, California 91766 USA.

Abstract:
Infections remain a major source of postoperative morbidity and mortality following complex bile duct surgeries, namely hepatectomy and pancreaticoduodenectomy. Infection rates remain high-ranging from 24% to 61%-and are influenced by multiple factors, including patient comorbidities, surgical complexity, and perioperative variables such as prolonged operative time, excessive blood loss, and preoperative biliary drainage. Disruption of the biliary barrier due to drainage or stent placement promotes bile stasis, microbial colonization, and biofilm formation, facilitating the emergence of multidrug-resistant (MDR) pathogens such as Escherichia coli, Klebsiella pneumoniae, and Enterococcus species. These resistance mechanisms-such as β-lactamase production, altered membrane permeability, efflux pump activity, and target site modification-make antimicrobial therapy increasingly complex, prolonging recovery, hospitalization, and healthcare costs. Diagnosis is often challenging and relies on a combination of clinical assessment, inflammatory markers (including leukocytosis, C-reactive protein, and procalcitonin), and microbiological cultures from bile, wound, or drainage fluid. Once infection is confirmed, management requires early recognition, empirical broad-spectrum antibiotic coverage, and subsequent de-escalation based on susceptibility testing. To prevent recurrence, effective source control through interventional drainage or reoperation is essential. In select cases, antifungal therapy may be indicated, particularly in the presence of Candida coinfection associated with biliary interventions or prolonged antibiotic exposure. Preventive strategies-including optimized perioperative care, tailored antibiotic prophylaxis, nutritional optimization, and minimally invasive surgical approaches-are vital to reduce infectious risk. Future efforts should focus on refining risk stratification, advancing rapid diagnostic methods, and developing evidence-based protocols to address the growing challenge of MDR infections and improve postoperative outcomes in hepatobiliary surgery.
More Related Videos
Related Concept Videos
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Kidney Transplant II: Surgical Procedure