Related Experiment Video
Updated: Feb 27, 2026
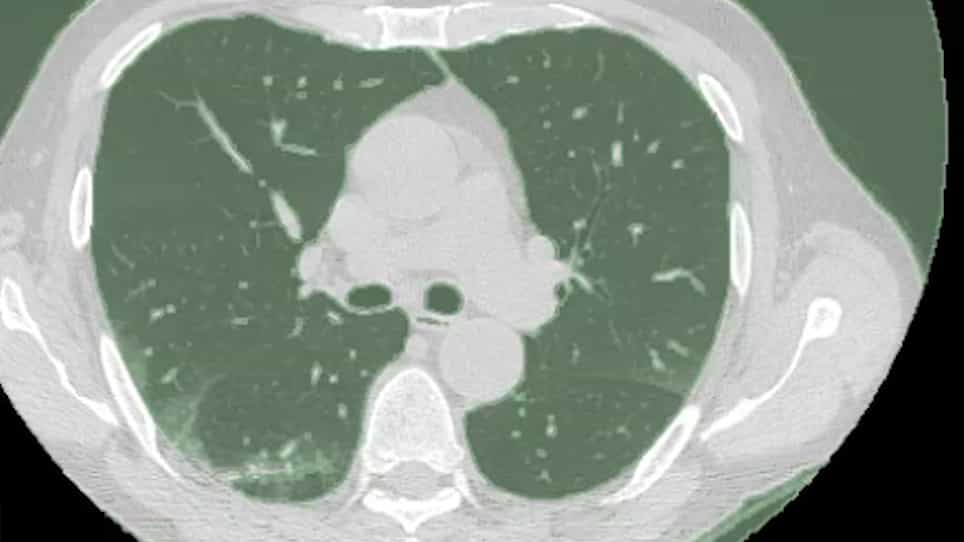

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Association Between ADA (Age-D-dimer-Albumin) Score and Chest CT Severity Score in COVID-19 Pneumonia
Enrico Maggio1, Giacomo Bonito2,3, Alessandra Oliva4
1Department of Medical and Cardiovascular Sciences, Sapienza University of Rome, Viale del Policlinico 155, 00161 Rome, Italy.

Abstract:
Background/Objectives: This study aims to assess the relation between the ADA score with the severity of pneumonia, as evaluated by chest tomography using a severity score. Methods: In this observational study we enrolled 350 consecutive adult patients (≥18 years) with COVID-19-related severe acute pneumonia requiring hospitalization, consecutively admitted to non-intensive care unit (ICU) medical wards from April 2020 to March 2022. A standard high-resolution chest computed tomography (HRCT) was performed in all cases with a multidetector CT scanner without intravenous contrast injection, except in case of suspicion of pulmonary embolism. The ADA score and semi-quantitative 25-point CT Severity Score (CTSS) were calculated for all patients. Results: A total of 350 COVID-19 patients (154 males (44%) and 196 females (56%)) were recruited. A logistic regression analysis showed that CTSS is statistically associated with the ADA score (Exp(B): 1.116; 95% CI: 1.027-1.212; p = 0.009) and the need for ICU (Exp(B): 8.719; 95% CI: 2.994-25.390; p < 0.001), while the linear regression analysis showed a relation between the CTSS and ADA score, GFR and CRP (p = 0.003) (predictors: ADA score [β coeff 0.276; 95% CI: 0.041--0.402; p = 0.017], GFR [β coeff -0.219; 95% CI: -0.095--0.001; p = 0.045], CRP [β coeff -0.226; IC 95% -0.077--0.001; p = 0.044]). Furthermore, a ROC curve analysis determined the optimal ADA score cut-off values for predicting severe CT findings at 44.5 (sensibility: 0.971; 1-specificity: 0.670; AUC: 0.750; SE 0.039; p < 0.001; 95% CI: 0.674-0.826; Youden's J index= 0.301). Conclusions: This study highlights the potential clinical utility of integrating laboratory- and imaging-based scores for a comprehensive assessment of patients hospitalized with SARS-CoV-2 infection. The combined use of these scores may enable a more accurate identification of patients with extensive pulmonary involvement and an increased prothrombotic burden at hospital admission, facilitating the early recognition of high-risk patients.


Related Concept Videos
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:30
Pneumonia III: Complications and Assessment
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: