Related Experiment Video
Updated: May 10, 2026

C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
Junctional Failures Following Long-Level Fusion to L5 in Elderly Patients: Impact of Spinopelvic Alignment and L5-S1
In-Seok Son1, Yong-Chan Kim1, Sung-Min Kim1
1Department of Orthopaedic Surgery, College of Medicine, Kyung Hee University, Kyung Hee University Hospital at Gangdong, Seoul 05278, Republic of Korea.

Abstract:
Background and Objectives: Long spinal fusion terminating at L5 remains controversial because of the risk of postoperative junctional failure. Although degeneration of the residual L5-S1 disc has been suggested as a contributing factor, the relative impact of disc degeneration versus sagittal spinopelvic alignment on different junctional failure patterns has not been fully clarified. Materials and Methods: This retrospective cohort study included 47 patients aged ≥60 years who underwent ≥5-level thoracolumbar fusion ending at L5 with a minimum follow-up of 2 years. Junctional failures were classified as proximal junctional failure (PJF) or distal junctional failure (DJF). Preoperative L5-S1 disc degeneration was assessed using modified Weiner and Pfirrmann classifications. Spinopelvic parameters were measured preoperatively, postoperatively, and at final follow-up. Junctional failure-free survival was analyzed using the Kaplan-Meier method, and risk factors were explored using Cox proportional hazards models. Results: Junctional failures occurred in 28 patients (59.6%), including 16 PJFs (34.0%) and 10 DJFs (21.3%). Lower grades of L5-S1 disc degeneration (Weiner grades 0-1) were more frequently associated with PJFs, whereas higher grades (≥2) were predominantly associated with DJFs (p = 0.024). Multivariate analysis showed that preoperative thoracolumbar kyphosis (hazard ratio [HR] = 1.164), preoperative T1 pelvic angle (HR = 1.269), and postoperative pelvic incidence-lumbar lordosis mismatch (HR = 0.877) as significant risk factors for PJF. Postoperative proximal junctional angle (HR = 0.899) and lumbar lordosis (HR = 0.920) were independently associated with DJF. Conclusions: Sagittal spinopelvic alignment parameters appear to have a greater influence on junctional failure patterns than residual L5-S1 disc degeneration in long fusions terminating at L5. Adequate sagittal correction should be prioritized to reduce the risk of both proximal and distal junctional failures.

Related Concept Videos
 01:29
Herniated Intervertebral Disc l: Introduction
 01:27
Degenerative Disc Disease I: Introduction
 01:23
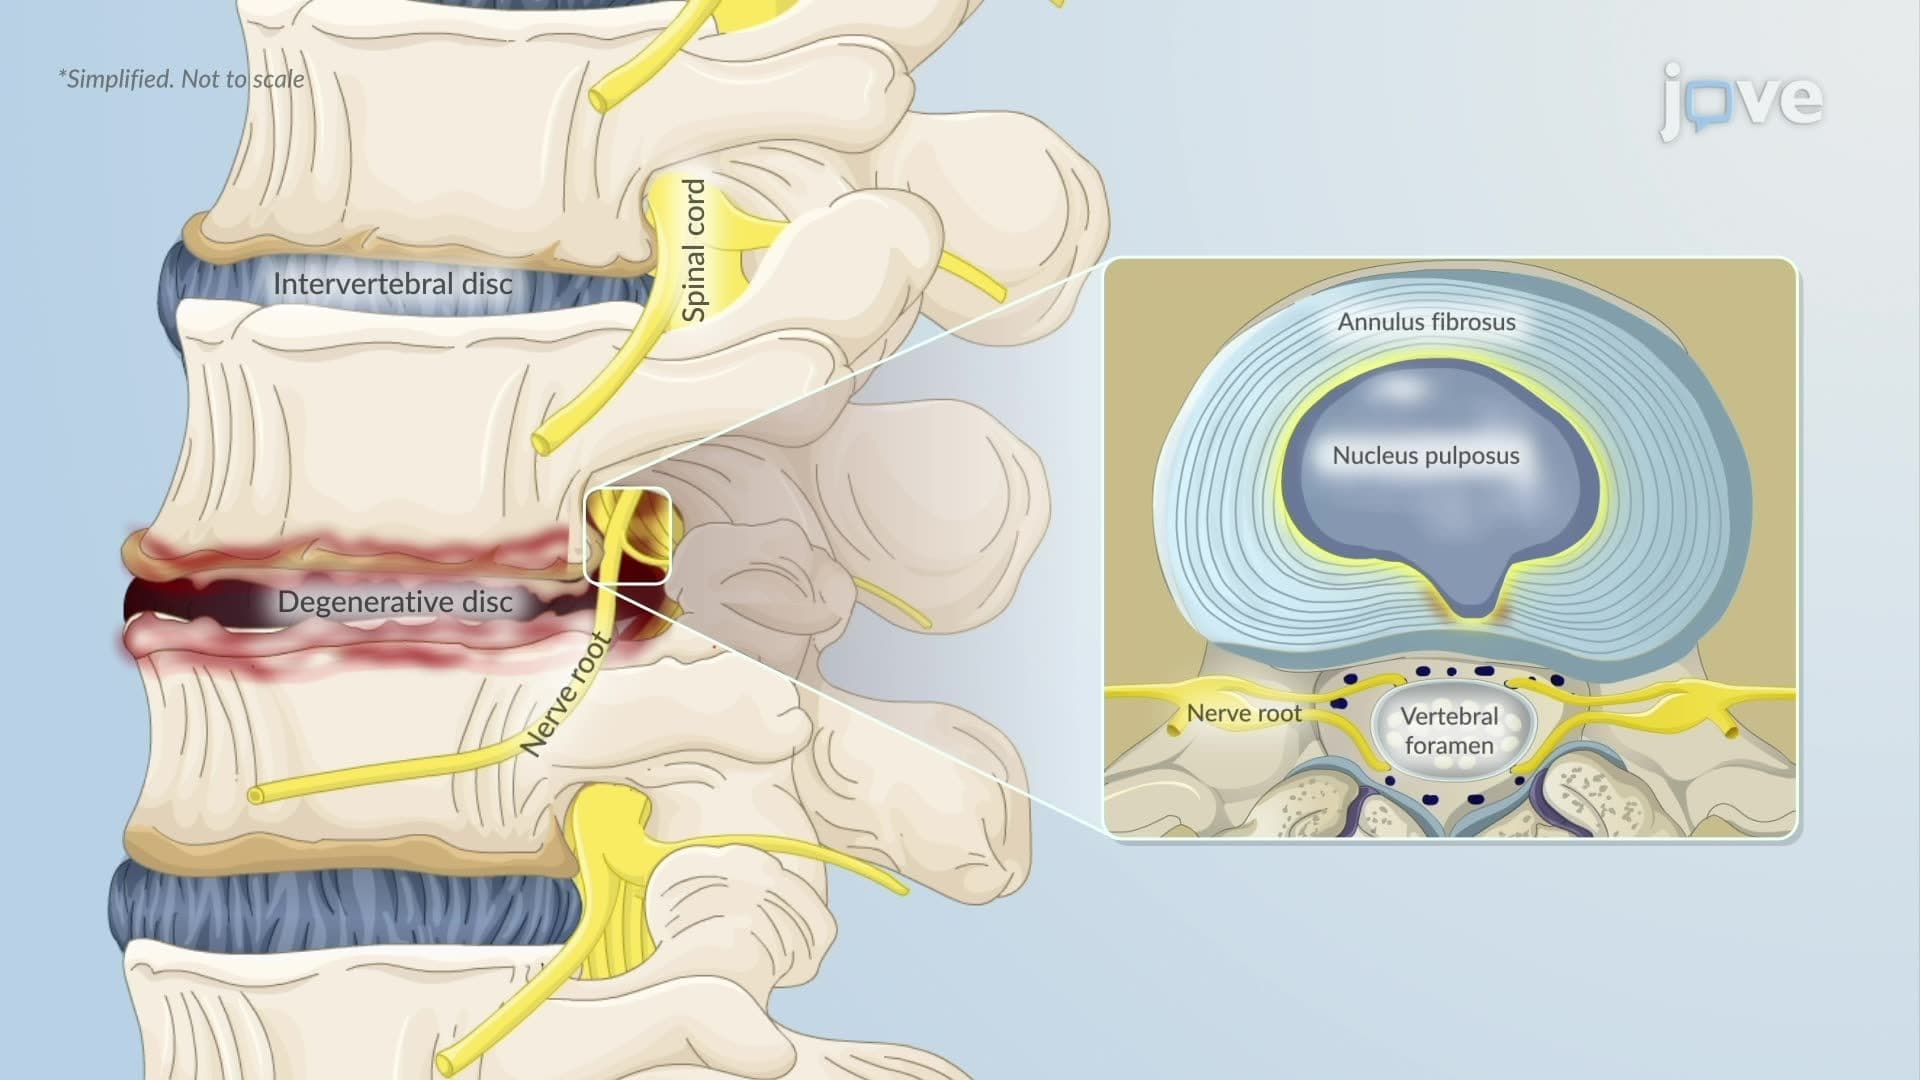
Degenerative Disc Disease ll: Pathophysiology
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology