Related Experiment Video
Updated: Feb 28, 2026
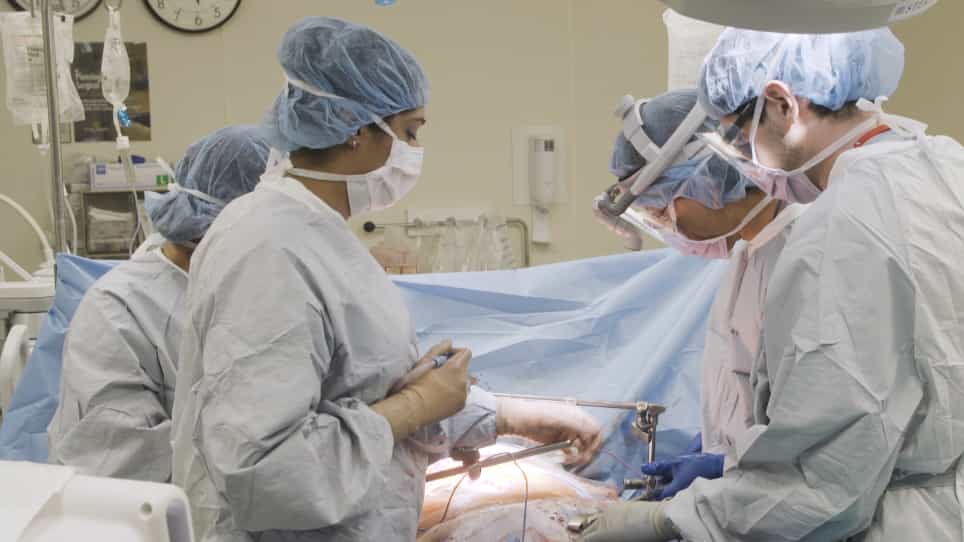

Colonial Wig Pancreaticojejunostomy
Published on: March 12, 2019
Association Between Postoperative Pancreatitis and Clinically Relevant Postoperative Pancreatic Fistula After
Uday Sankar Reddy Kathulapalli1, Harshal Bhoi1, Jyotirmay Jena1
1Surgical Gastroenterology, Siksha 'O' Anusandhan, Institute of Medical Sciences and Sum Hospital, Bhubaneswar, IND.

Insights
Postoperative day 1 serum amylase and drain fluid amylase reliably predict clinically relevant postoperative pancreatic fistula after pancreaticoduodenectomy. High drain fluid amylase or low serum amylase levels can guide early management decisions.
Area of Science:
- Gastroenterology and Hepatology
- Surgical Oncology
- Abdominal Surgery
Background:
- Postoperative pancreatic fistula (POPF) is a significant complication after pancreaticoduodenectomy (PD), impacting patient morbidity.
- Early identification of patients at risk for clinically relevant POPF (CR-POPF) is crucial for timely intervention and management.
Purpose of the Study:
- To evaluate the predictive value of postoperative day 1 (POD 1) serum amylase (SA) and drain fluid amylase (DFA) for CR-POPF following PD.
- To establish optimal cutoff values for POD 1 SA and DFA to facilitate risk-stratified postoperative care.
Main Methods:
- Prospective observational cohort study of adult patients undergoing PD with duct-to-mucosa pancreaticojejunal anastomosis.
- Measurement of SA and DFA on POD 1, POD 3, and POD 5.
- Receiver operating characteristic (ROC) analysis to determine optimal POD 1 cutoff values for CR-POPF prediction.
Main Results:
- Nine out of 57 patients (15.8%) developed CR-POPF.
- Significantly higher mean POD 1 SA (464 vs 262 IU/L) and DFA (12,664 vs 1,045 IU/L) in CR-POPF patients (p<0.002).
- POD 1 DFA showed high specificity (97.92%) with a cutoff of 3,011 IU/L (AUC 0.889); POD 1 SA cutoff of 363 IU/L had high sensitivity (77.78%) (AUC 0.803).
Conclusions:
- POD 1 SA and DFA levels are reliable early predictors of CR-POPF after PD.
- A POD 1 DFA >3,011 IU/L strongly suggests CR-POPF, while SA ≤363 IU/L helps exclude it.
- Integrating these biomarkers into postoperative protocols can improve drain management and targeted interventions for high-risk patients.
Backgrounds/Aims:
Postoperative pancreatic fistula remains a key determinant of morbidity following pancreaticoduodenectomy (PD). This study assessed whether postoperative day 1 (POD 1) serum amylase (SA) and drain fluid amylase (DFA) can predict clinically relevant postoperative pancreatic fistula (CR-POPF) to facilitate early risk-stratified postoperative management.
Methods:
This prospective observational cohort study (January 2021-April 2023) included adult patients undergoing PD with duct-to-mucosa pancreaticojejunal anastomosis. SA and DFA levels were measured on POD 1, POD3, and POD 5. The primary outcome was CR-POPF, defined according to the 2016 International Study Group of Pancreatic Surgery criteria. Receiver operating characteristic (ROC) analyses were performed to identify optimal POD 1 cutoff values.
Results:
Among 57 patients, nine (15.8%) developed CR-POPF. Mean POD 1 SA and DFA levels were significantly higher in patients who developed CR-POPF compared with those who did not (SA: 464 ± 164 vs 262 ± 176 IU/L, p = 0.002; DFA: 12,664 ± 8,800 vs 1,045 ± 1,128 IU/L, p < 0.001). POD 1 SA demonstrated an AUC of 0.803 (95% CI 0.677-0.897), with an optimal cutoff of 363 IU/L (sensitivity 77.78%, specificity 75.0%, negative predictive value (NPV) 94.7%). POD 1 DFA showed superior discrimination with an AUC of 0.889 (95% CI 0.778-0.957); a cutoff of 3,011 IU/L yielded a sensitivity of 66.67%, specificity of 97.92%, positive predictive value (PPV) of 85.7%, and NPV of 94.0%. A dilated pancreatic duct (>3 mm) was inversely associated with CR-POPF (p < 0.001).
Conclusions:
POD 1 SA and DFA levels provide a reliable early prediction of CR-POPF following PD. A DFA threshold above 3,011 IU/L demonstrates high specificity for CR-POPF, whereas a SA level ≤363 IU/L effectively excludes its occurrence. Incorporation of these parameters into postoperative protocols may aid early drain management decisions and targeted intervention in high-risk patients.
More Related Videos
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management