Related Experiment Video
Updated: Mar 3, 2026


Utilizing Percutaneous Ventricular Assist Devices in Acute Myocardial Infarction Complicated by Cardiogenic Shock
Published on: June 12, 2021
Acute Hemodynamic Effects of Ivabradine in Pediatric Cardiac Critical Care Patients
Rohit S Loomba1,2, Wesam Sourour1,2, Ashley Yao1
1Ann & Robert H. Lurie Children's Hospital, Chicago, IL.

Insights
Ivabradine safely reduced heart rate in pediatric cardiac patients within 24 hours. The drug demonstrated distinct hemodynamic phases, impacting heart rate, blood pressure, and oxygen saturation, with potential benefits observed.
Area of Science:
- Pediatric Cardiology
- Clinical Pharmacology
- Critical Care Medicine
Background:
- Ivabradine is used in pediatric patients for arrhythmias and heart failure to control heart rate.
- Tachycardia can negatively impact hemodynamics by increasing myocardial oxygen demand and decreasing cardiac output.
- Acute hemodynamic effects of ivabradine in children require real-time study.
Purpose of the Study:
- To characterize the effect of enteral ivabradine on heart rate in pediatric cardiac intensive care unit patients within 24 hours.
- To assess secondary hemodynamic effects including arterial saturation, respiratory rate, mean arterial blood pressure, central venous pressure, and renal near infrared spectroscopy.
Main Methods:
- Leveraged the Sickbay platform for real-time data acquisition.
- Monitored key hemodynamic parameters in pediatric patients receiving enteral ivabradine.
- Analyzed data within the first 24 hours of drug initiation.
Main Results:
- Heart rate decreased by approximately 17% within 15 hours of ivabradine administration.
- Observed varied changes in secondary parameters over time, including decreased central venous pressure.
- Noted increased renal tissue oxygen saturation (rSO2) by the 24-hour mark.
Conclusions:
- Ivabradine appears safe for use in pediatric patients.
- Hemodynamic responses to ivabradine occur in three distinct phases correlating with pharmacokinetics.
- These phases involve changes in heart rate and systemic oxygen delivery, with a potential for improved oxygen delivery in the final phase.
Background:
Utilization of ivabradine in the pediatric population has been centered on the goal of chronotropic control in patients with arrhythmias and heart failure. Tachycardia is known to be detrimental when it impairs hemodynamics by increasing myocardial oxygen demand, increasing ventricular end-diastolic pressures, and decreasing cardiac output in certain patients. The acute hemodynamic effects of ivabradine have not yet been studied in real time.
Study Question:
This study was performed leveraging the Sickbay platform (Medical Informatics Company, Houston, TX). The primary aim of this study was to characterize the effect of enteral ivabradine on heart rate in patients in a pediatric cardiac intensive care unit within 24 hours of initiation. Secondary aims were to characterize the effects of ivabradine on arterial saturation, respiratory rate, mean arterial blood pressure, central venous pressure, and renal near infrared spectroscopy for the same time frame.
Results:
Heart rate decreased approximately 17% in the first 15 hours after ivabradine administration. Changes were seen in the secondary aims that varied depending on time after first and second doses. Specifically, decreases in central venous pressure and increased renal tissue oxygen saturation (rSO2) were observed by the end of the 24 hours.
Conclusions:
Ivabradine seems safe in pediatric patients. It is associated with 3 distinct hemodynamic response phases: the first phase is associated with decreased heart rate and unchanged systemic oxygen delivery, the second phase is associated with increased heart rate and worsened systemic oxygen delivery, and the third phase being associated with decreased heart rate and improved systemic oxygen delivery. These phases coincide with the pharmacokinetic properties of ivabradine.
Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:19
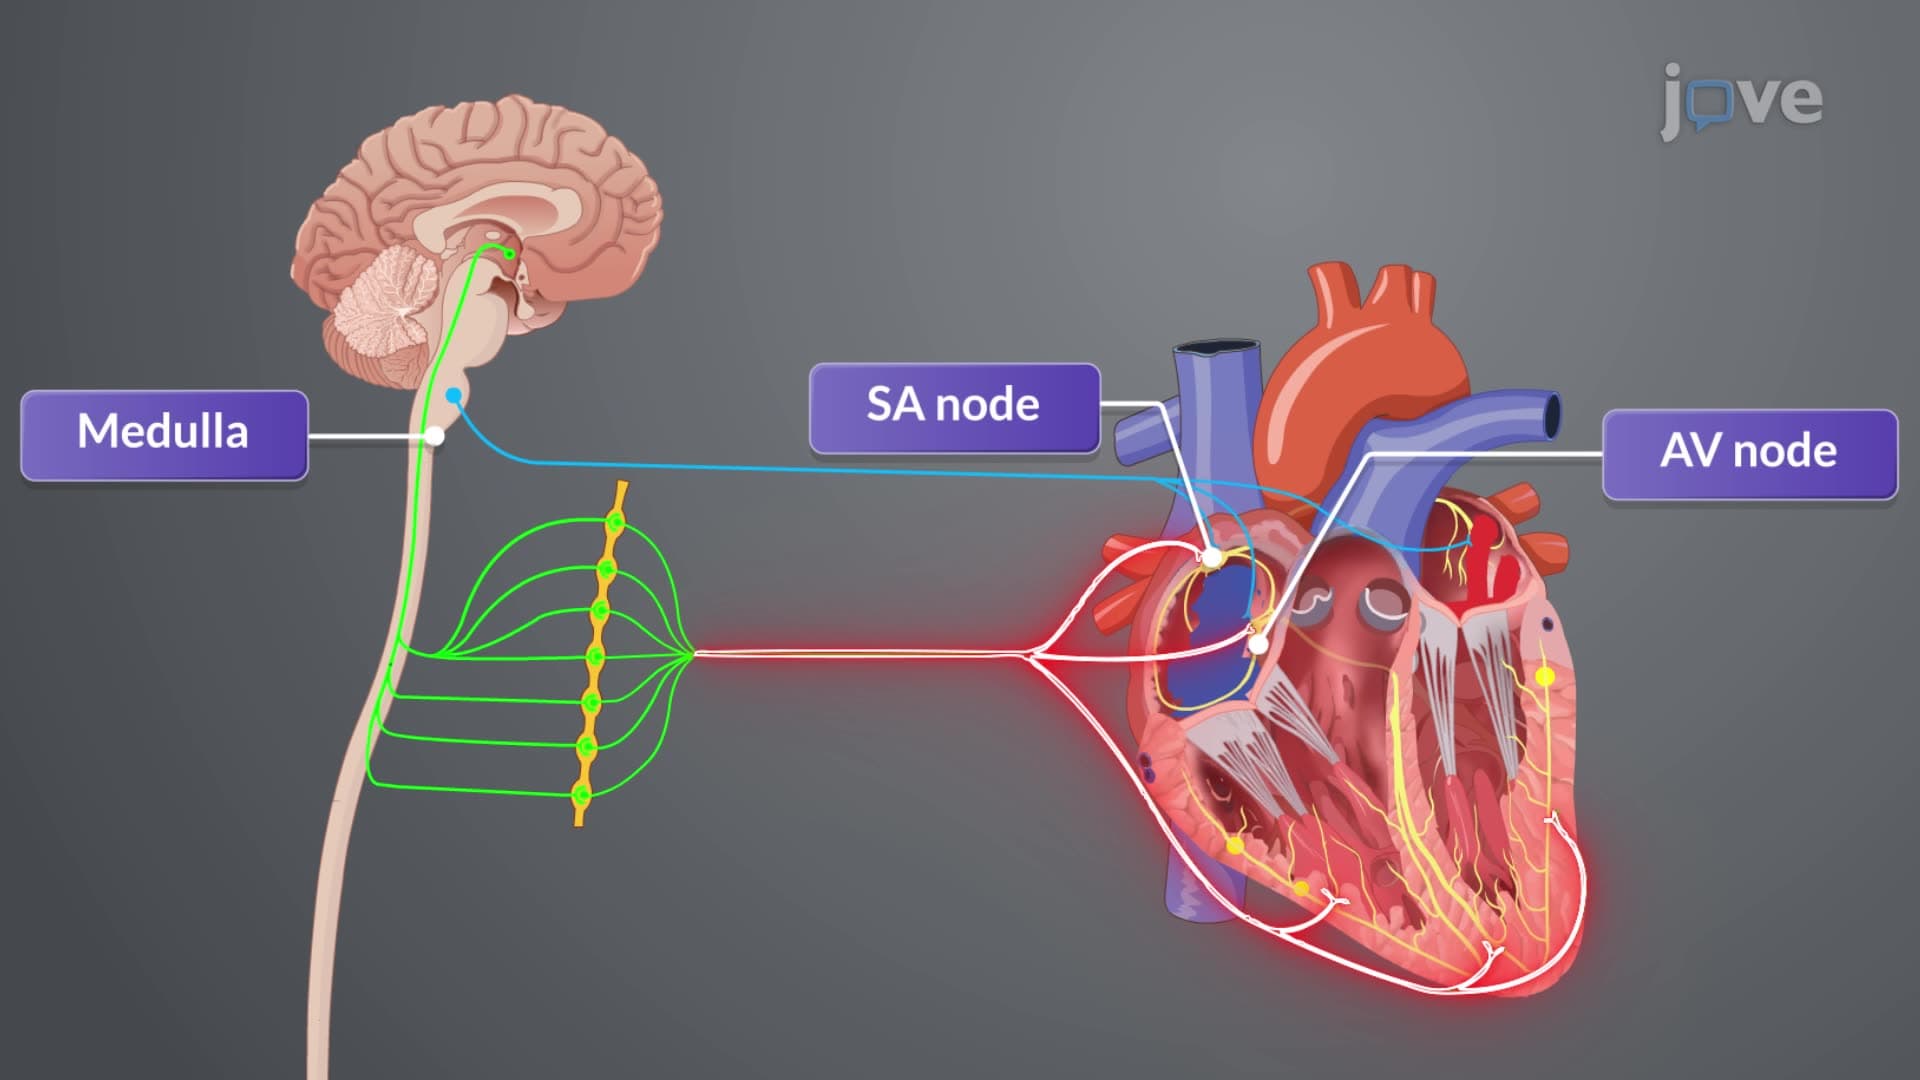
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:26
Heart Failure Drugs: Inotropic Agents