Related Experiment Video
Updated: Mar 3, 2026


The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Accuracy and safety of acetabular cup placement in total hip arthroplasty using mixed-reality navigation: A
Joseph P Costello1, Samantha G Mosle2, Hannah Mosher3
1Atrium Health-Carolinas Medical Center, Atrium Health Musculoskeletal Institute, 1000 Blythe Blvd, Charlotte, NC, 28203, USA.

Background:
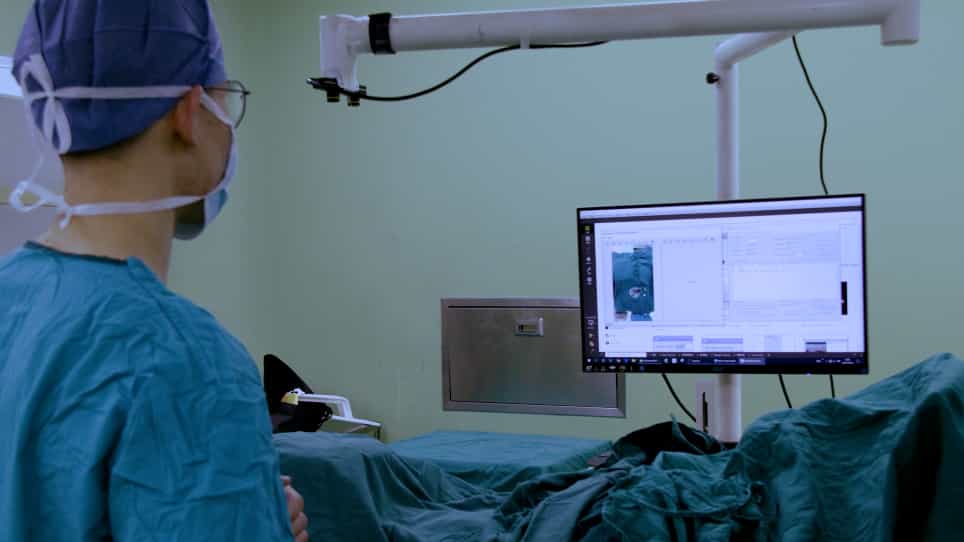
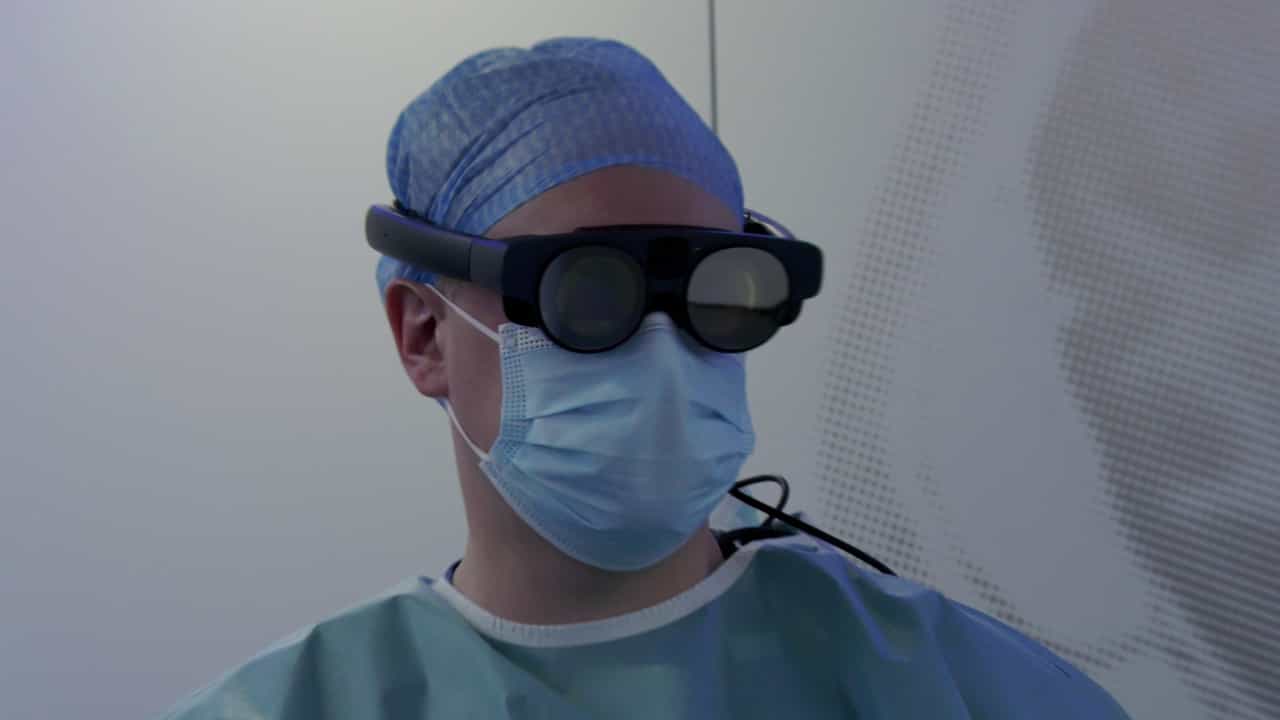
Safe and accurate placement of the acetabular component is critical in total hip arthroplasty (THA). Fluoroscopy helps with cup positioning in the direct anterior approach (DAA) but increases radiation exposure. Augmented and mixed-reality (MR) systems may improve precision while decreasing reliance on fluoroscopy. This study assessed the accuracy, safety, and impact on radiation exposure of MR navigation in anterior and posterior THA.
Methods:
From July 2023 to May 2024 at a single tertiary level institution, 33 patients underwent unilateral THA with MR by either the anterior (16) or posterior (17) approach. Operative time, patient demographics, pre-operative plan and post-operative positioning measures (center of rotation, leg length discrepancy, anteversion, and inclination) were compared between cohorts.
Results:
There were no demographic differences between cohorts, though operative time was significantly longer in the anterior group (106.30 vs 94.12 min, p < 0.001). Evidence of a learning curve was observed in the anterior cohort, with significantly higher radiation dose (187.40 vs 119.30 uGym2, p = 0.03) and reference air kerma (4.17 vs 2.60 mGy, p = 0.02) in the initial 20% of cases. While cup placement accuracy was comparable between groups for center of rotation, leg length discrepancy, and anteversion, inclination differed significantly (2.88 vs -6.71°, p = 0.0003). Within-group analyses showed significant deviations from the preoperative plan for all measured variables in both cohorts. Despite this, all patients met clinical thresholds for LLD (<18 mm) and anteversion (15° ± 10°), with 100% of anterior and 88.2% of posterior cases within the target inclination range (40° ± 10°), and 72.7% achieving a center of rotation within ≤5 mm of the plan.
Conclusion:
MR-navigated THA can safely produce accurate acetabular cup placement in both anterior and posterior total hip arthroplasty, validating safe use in THA. The observed learning curve suggests MR reduces reliance on fluoroscopy while enhancing surgical precision.