Related Experiment Video
Updated: May 6, 2026


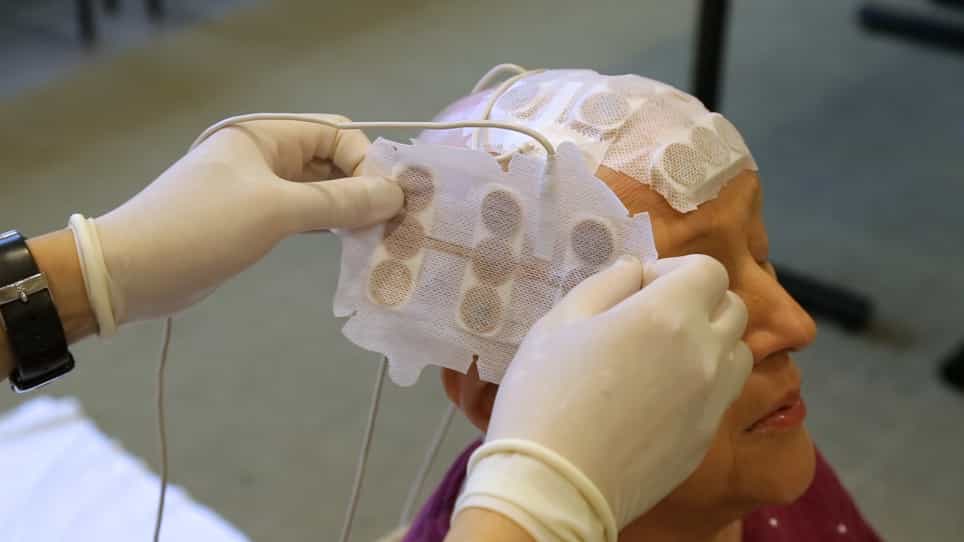
Tumor Treating Field Therapy in Combination with Bevacizumab for the Treatment of Recurrent Glioblastoma
Published on: October 27, 2014
Rethinking treatment de-escalation in elderly glioblastoma: Lessons from a multicenter real-world cohort
Orit Furman1,2, Eva Falah3, Inbar Dvir2,4
1Neuro-Radiotherapy Unit, Oncology Institute, Tel Aviv Sourasky Medical Center, Tel Aviv, Israel.

Background:
Glioblastoma (GBM) in elderly patients (≥65 years) carries a poor prognosis and higher treatment toxicity. Consequently, many receive de-escalated regimens, often guided by MGMT promoter methylation. However, real-world outcomes across treatment strategies remain underreported and often lack molecular and functional detail.
Methods:
We retrospectively analyzed 573 elderly GBM patients treated between 2009 and 2023 at 2 Israeli tertiary centers. Post-operative treatments included (1) chemoradiotherapy (CRT; 60Gy in 30 fractions or 40Gy in a15 fractions), (2) temozolomide (TMZ) monotherapy, (3) radiotherapy alone (RT), or (4) best supportive care. MGMT status and Karnofsky Performance Status (KPS) were analyzed where available. Survival was assessed using Kaplan-Meier and log-rank tests.
Results:
Median overall survival (mOS) was longest with CRT (14 months), compared to 8 months for TMZ and RT monotherapies and 2 months for best supportive care. Among MGMT-methylated patients, CRT yielded mOS of 23 months versus 8 months for TMZ alone. Younger age, surgical resection, and higher KPS predicted longer survival. In the TMZ subgroup, toxicity was low (6% hematologic, 12% non-hematologic grade 3-4 events) and survival improved with increasing TMZ cycles. Salvage therapy after progression was also associated with longer survival. Limitations include retrospective design, incomplete molecular data, frailty and QOL data not collected routinely, potential selection bias, and evolving treatment practices.
Conclusion:
Fit elderly patients with GBM may achieve benefit from full standard-of-care therapy. Treatment decisions should be guided by functional and clinical fitness rather than chronological age. These real-world data highlight the importance of integrating clinical and functional factors into management of elderly GBM.

Related Concept Videos
 02:56
Treatment Resistant Cancers
 01:22
Alzheimer's Disease: Treatment
 01:15
Drug Dosing: Geriatric Patients
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age