Related Experiment Video
Updated: Mar 7, 2026
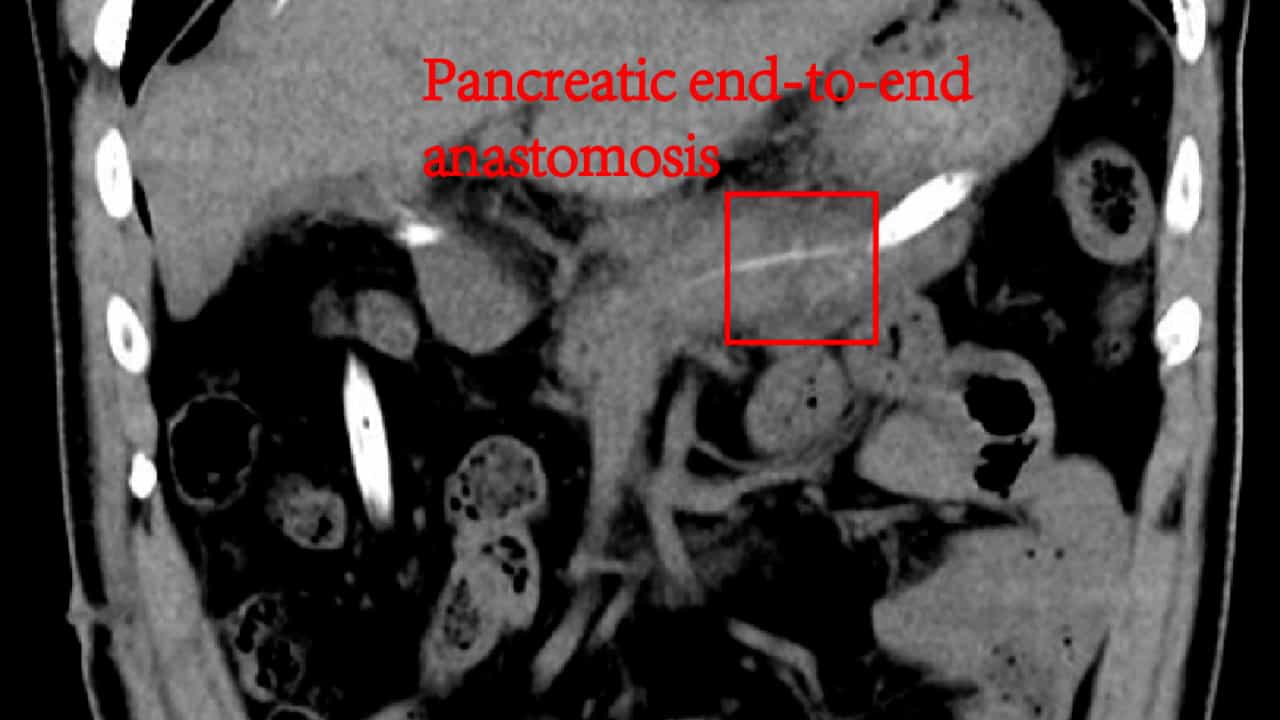

Application of Mid-Pancreatectomy with End-to-End Anastomosis in Pancreatic Benign Tumors
Published on: February 9, 2024
Characteristic and endovascular management of peripancreatic arterial aneurysms: Experience from a single-center
Siting Li1,2, Xiaoning Sun1,2, Wenxuan Xiang1,2
1Department of Vascular Surgery, Peking Union Medical College Hospital, Chinese Academy of Medical Sciences and Peking Union Medical College, Beijing, China.

Abstract:
ObjectivePeripancreatic arterial aneurysms (PAAs) are rare but associated with a high risk of rupture and significant mortality. This study aims to evaluate the safety and efficacy of endovascular management for PAAs, focusing on technical strategies and midterm outcomes.MethodsA single-center retrospective analysis was conducted on a study cohort of 26 patients with PAAs treated consecutively between June 2014 and March 2025. Endovascular therapy was prioritized, with open repair reserved for anatomically complex cases. Technical success, procedural details, and follow-up outcomes were analyzed.ResultsAmong 29 aneurysms in 26 patients, 15 were located at the gastroduodenal artery-superior pancreaticoduodenal artery (GDA-SPDA) and 14 were at the superior mesenteric artery-inferior pancreaticoduodenal artery (SMA-IPDA). Endovascular therapy achieved primary technical success in 88.5% of cases. Two patients failed endovascular access via both the CA and SMA. Another had a vascular variant creating a high risk of splenic ischemia upon embolization, and a fourth had an aneurysm involving critical duodenal branches. Three of these four patients underwent successful open surgical repair. Sac-only embolization was performed in 63.6% of cases to preserve collateral flow. Access routes were largely determined by aneurysm location, with SMA for SMA-IPDA aneurysms and celiac artery (CA) for GDA-SPDA aneurysms (p < 0.001). Concomitant celiac revascularization was avoided in most cases. At a median follow-up of 48 months, aneurysm recurrence and restenosis rates were 4.0% each, with no coil migrations or ischemic complications.ConclusionTailored endovascular strategies guided by aneurysm anatomy and collateral circulation yield high technical success and favorable midterm outcomes without routine celiac revascularization. Endovascular therapy is a safe and effective first-line approach for PAAs, with open repair reserved for complex anatomies.

Related Concept Videos
 01:26
Aneurysm III: Interprofessional Care
 01:22
Aneurysm IV: Nursing Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management