Related Experiment Video
Updated: Mar 10, 2026


State of the Art Cranial Ultrasound Imaging in Neonates
Published on: February 2, 2015
Ultrasound Assessment of the Third Ventricle Diameter: Agreement With CT Results in the Pediatric Population
Safae Dehbi1,2, Zhor Zeghari2,3, Chaimae Es-Sebbani4
1Pediatric Intensive Care Unit (PICU) of the Children's Hospital of Rabat, IBN SINA University Hospital, Rabat, Morocco.

Insights
Transcranial ultrasound (TUS) offers reliable bedside measurements of third ventricle diameter in children, showing good agreement with CT scans. This non-irradiating method is valuable for serial monitoring in pediatric intensive care units.
Area of Science:
- Pediatric Neurology
- Medical Imaging
- Critical Care Medicine
Background:
- Accurate measurement of the third ventricle diameter is crucial for managing critically ill children with neurological conditions.
- Computed tomography (CT) is a standard imaging modality but involves radiation exposure.
- Transcranial ultrasound (TUS) offers a non-irradiating alternative for bedside assessment.
Purpose of the Study:
- To evaluate the agreement between transcranial ultrasound (TUS) and CT measurements of third ventricle diameter in critically ill children.
- To determine the feasibility and reproducibility of TUS for ventricular assessment in a pediatric intensive care unit (PICU) setting.
Main Methods:
- A prospective observational cohort study was conducted in a PICU.
- 148 critically ill children (1 month to 15 years) underwent TUS within 1 hour of brain CT.
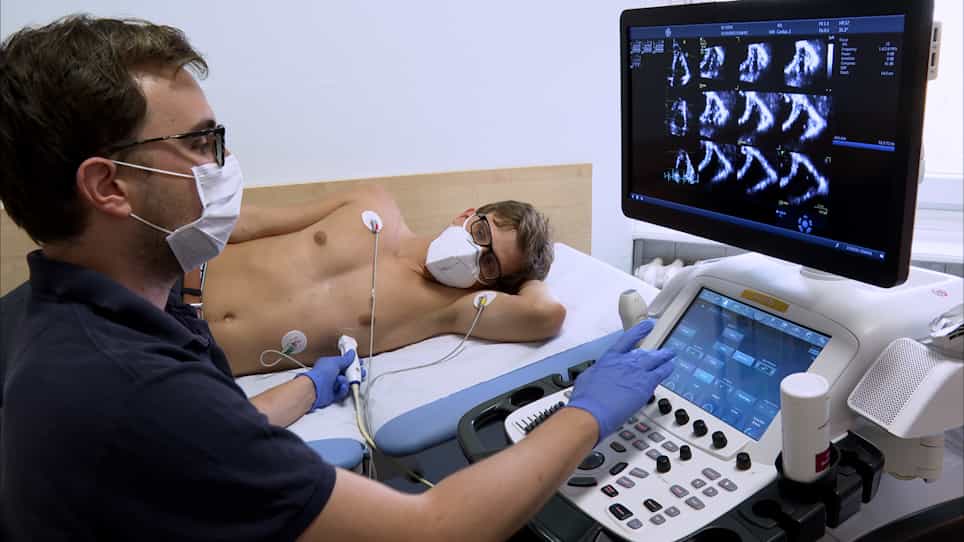
- TUS measurements were performed using a phased-array probe through bilateral transtemporal windows.
Main Results:
- TUS demonstrated high feasibility, with successful bilateral acoustic windows in 98.6% of cases.
- The median third ventricle diameter measured 3.6 mm by both CT and TUS.
- Bland-Altman analysis showed good agreement between TUS and CT, with minimal bias and acceptable limits of agreement.
Conclusions:
- TUS provides reproducible bedside measurements of third ventricle diameter in children, comparable to CT in patients without midline shift.
- TUS can serve as a valuable non-irradiating adjunct for serial ventricular monitoring, especially for hydrocephalus detection and external ventricular drain management.
- Further research is recommended to assess interoperator reproducibility and TUS applicability in complex cases.
Objectives:
To evaluate the agreement between transcranial ultrasound (TUS) and CT measurements of third ventricle diameter in critically ill children.
Design:
Prospective observational cohort study.
Setting:
PICU of the Children's Hospital of Rabat, Morocco.
Patients:
Children 1 month to 15 years old admitted with acute neurologic distress who underwent brain CT.
Interventions:
TUS was performed within 1 hour of CT using a phased-array probe through bilateral transtemporal windows.
Measurements And Main Results:
Of 150 screened patients, 148 were included (median age 5 yr; 68% male). Feasibility was high, with bilateral acoustic windows obtained in 98.6% of cases. The median third ventricle diameter was 3.6 mm by both CT and TUS. Bland-Altman analysis demonstrated good agreement between TUS and CT: mean bias 0.11 mm (limits of agreement, -0.78 to 1.01 mm) on the right side and 0.16 mm (-0.81 to 1.13 mm) on the left. Agreement was highest for smaller third ventricle diameters, which accounted for most measurements. No patients had a midline shift or had undergone decompressive craniectomy at the time of imaging.
Conclusions:
TUS provides reproducible bedside measurements of third ventricle diameter in children, with good agreement compared with CT in patients without midline shift or major surgical alterations. While not a substitute for comprehensive neuroimaging, TUS may serve as a nonirradiating adjunct for serial ventricular monitoring, particularly for monitoring for the development of hydrocephalus and during external ventricular drain management. Further research should evaluate interoperator reproducibility, applicability in patients with mass effect, and integration into clinical workflows.