Related Experiment Video
Updated: Mar 11, 2026


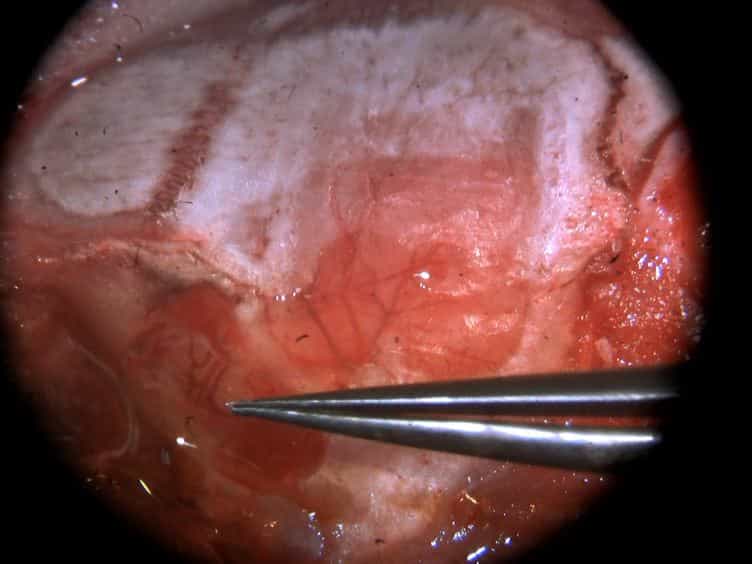
Microsurgical Clip Obliteration of Middle Cerebral Aneurysm Using Intraoperative Flow Assessment
Published on: September 25, 2009
Septic embolus resulting in M1 occlusion with separate, multiple distal mycotic aneurysms, complicated by surrounding
Nicholas K Dietz1, Jasmine Omair1, Andrea Becerril-Gaitan1
1Department of Neurosurgery, University of Louisville School of Medicine, Louisville, Kentucky.

Background:
Intracranial mycotic aneurysms are rare, representing only 0.7%-5.4% of all intracranial aneurysms, and typically arise from septic emboli secondary to infective endocarditis. Large-vessel occlusion due to a septic embolus is exceedingly uncommon and carries high morbidity.
Observations:
A 29-year-old man with methicillin-resistant Staphylococcus aureus endocarditis and intravenous drug use presented with intracerebral and subarachnoid hemorrhage. CT angiography revealed a left parieto-occipital hematoma with midline shift. An emergency craniotomy for hematoma evacuation exposed a ruptured distal middle cerebral artery (MCA) mycotic aneurysm, which was clipped, and pathological analysis confirmed abscess formation within the aneurysm wall. Despite antibiotic therapy, a new distal MCA aneurysm developed within an abscess cavity. Cerebral angiography later demonstrated M1 occlusion requiring mechanical thrombectomy, achieving partial reperfusion consistent with Thrombolysis in Cerebral Infarction grade 2a. The persistent abscess and aneurysm required Onyx embolization and abscess drainage in a hybrid operating room.
Lessons:
Sequential mycotic aneurysms with concurrent large-vessel occlusion and abscess formation represent a rare and aggressive manifestation of septic emboli. Successful management depends on coordinated microsurgical clipping, endovascular embolization, thrombectomy, and abscess evacuation. Early recognition of evolving vascular pathology and combined surgical-endovascular approaches improve outcomes in infective mycotic aneurysm-related cerebrovascular disease. https://thejns.org/doi/10.3171/CASE25902.
Insights
This case highlights sequential mycotic aneurysms and large-vessel occlusion, a rare complication of infective endocarditis. Combined surgical and endovascular treatments are crucial for managing this aggressive cerebrovascular disease.
Area of Science:
- Neurology
- Neurosurgery
- Infectious Diseases
Background:
- Intracranial mycotic aneurysms are rare, accounting for 0.7%-5.4% of all intracranial aneurysms.
- They typically result from septic emboli originating from infective endocarditis.
- Large-vessel occlusion from septic emboli is uncommon and associated with high morbidity.
Purpose of the Study:
- To present a rare case of sequential mycotic aneurysms with concurrent large-vessel occlusion and abscess formation.
- To emphasize the importance of a multidisciplinary approach in managing complex cerebrovascular disease.
- To highlight the role of advanced imaging and endovascular techniques.
Main Methods:
- A 29-year-old male with methicillin-resistant Staphylococcus aureus endocarditis presented with hemorrhage.
- Initial management included craniotomy for hematoma evacuation and clipping of a ruptured middle cerebral artery (MCA) mycotic aneurysm.
- Subsequent management involved mechanical thrombectomy for M1 occlusion and endovascular embolization with abscess drainage.
Main Results:
- Pathological analysis confirmed abscess formation within the aneurysm wall.
- A new distal MCA aneurysm developed despite initial treatment and antibiotic therapy.
- Successful reperfusion (TICI 2a) was achieved after mechanical thrombectomy, but persistent infection required further intervention.
Conclusions:
- Sequential mycotic aneurysms with large-vessel occlusion and abscess formation are aggressive manifestations of septic emboli.
- Successful management requires coordinated microsurgical clipping, endovascular embolization, thrombectomy, and abscess evacuation.
- Early recognition and combined surgical-endovascular strategies improve outcomes in infective mycotic aneurysm-related cerebrovascular disease.