Related Experiment Video
Updated: Mar 12, 2026


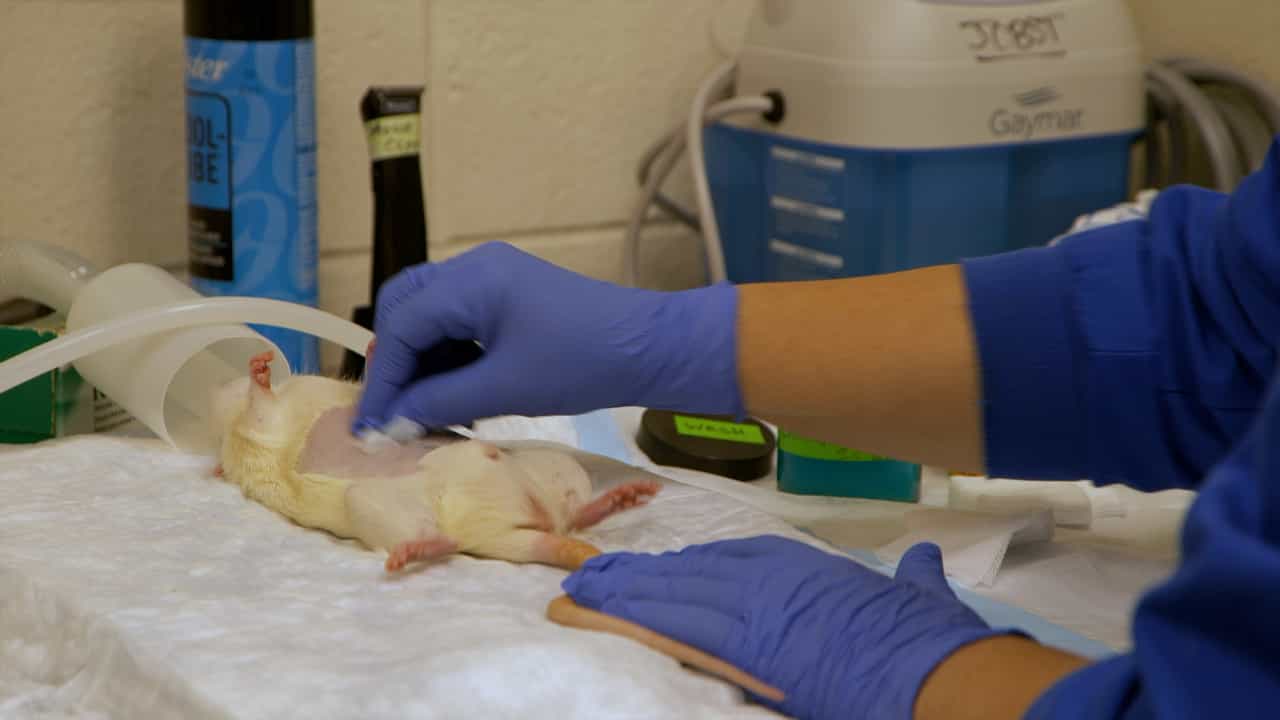
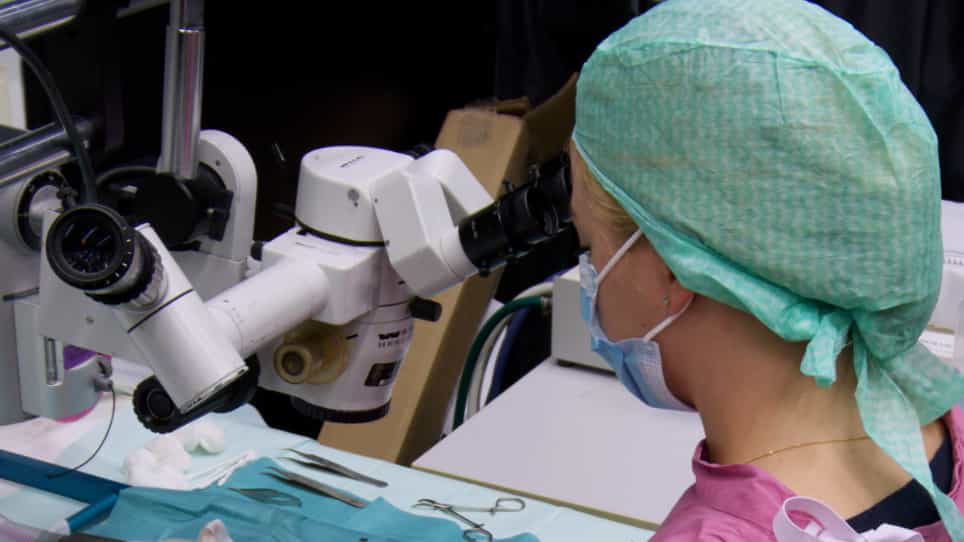
A Murine Model of Stent Implantation in the Carotid Artery for the Study of Restenosis
Published on: May 14, 2013
Sirolimus vs paclitaxel-coated balloons in in-stent coronary restenosis: A meta-analysis
Debvarsha Mandal1, Thomas Viji Pulickal2, Dhritika Ahlawat3
1Department of Internal Medicine, Avalon University School of Medicine, Willemstad 4797, Netherlands.

Background:
In-stent restenosis (ISR) is a persistent challenge after percutaneous coronary intervention, with drug-coated balloons such as sirolimus-coated balloons (SCBs) and paclitaxel-coated balloons (PCBs) being key treatment options. However, data comparing their efficacy and safety are limited.
Aim:
To evaluate the comparative efficacy and safety of SCBs vs PCBs in patients with coronary ISR.
Methods:
A systematic search of PubMed, EMBASE, and ScienceDirect was conducted from inception to May 2025, following Systematic Reviews and Meta-Analyses guidelines. Eligible studies were randomized controlled trials and observational studies comparing SCBs and PCBs in adults with coronary ISR, reporting outcomes like target lesion revascularization (TLR), major adverse cardiovascular events (MACE), stent thrombosis, all-cause mortality, cardiac mortality, and myocardial infarction. Risk ratios (RRs) with 95% confidence intervals (CIs) were calculated using a random-effects model. Heterogeneity was assessed with the I 2 statistic, and study quality was evaluated using the Cochrane Risk of Bias 2.0 tool and Newcastle-Ottawa Scale. A P value < 0.05 was considered significant.
Results:
Four studies (three randomized controlled trials and one observational study) were analyzed. No significant differences were found between SCBs and PCBs for TLR (RR 1.22, 95%CI: 0.72-2.06, P = 0.75, I 2 = 0%), MACE (RR 1.15, 95%CI: 0.70-1.90, P = 0.80, I 2 = 0%), stent thrombosis (RR 1.01, 95%CI: 0.57-1.78, P = 0.61, I 2 = 0%), all-cause mortality (RR 0.67, 95%CI: 0.11-4.06, P = 0.69, I 2 = 0%), cardiac mortality (RR 1.28, 95%CI: 0.16-10.28, P = 0.77, I 2 = 0%), or myocardial infarction (RR 0.99, 95%CI: 0.10-9.44, P = 0.35, I 2 = 0%). Studies had low to moderate risk of bias, with consistent treatment effects.
Conclusion:
SCBs and PCBs show similar efficacy and safety for coronary ISR, allowing flexible use based on availability and patient needs. Future studies should explore long-term outcomes and high-risk groups to optimize ISR management.
More Related Videos
Related Concept Videos
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:27
Coronary Artery Disease V: Interprofessional Care