Related Experiment Video
Updated: Mar 12, 2026


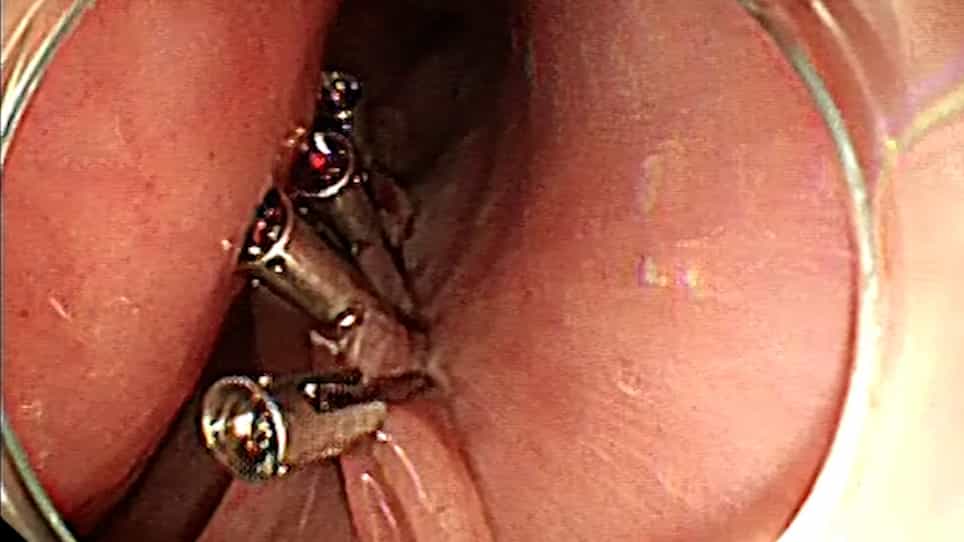
Robotic Myotomy and Partial Fundoplication for Achalasia
Published on: August 11, 2023
Simultaneous treatment of concomitant achalasia coexisting with epiphrenic diverticulum: The practice of submucosal
Xin-Wei Hao1, Ya-Wei Bi1, Zi-Meng Wang1
1Department of Gastroenterology, The First Medical Center of Chinese PLA General Hospital, Beijing 100853, China.

Background:
Esophageal epiphrenic diverticulum (ED) often occurs in patients with esophageal motility disorders, and its incidence rate is approximately 3%-7% in achalasia (AC). A distinct septum has been observed in some patients with AC coexisting with ED during gastroscopy. Digestive endoscopic tunnel technique has emerged as a promising therapeutic approach for these patients.
Aim:
To evaluate the therapeutic effectiveness of specific treatment methods for ED with septum (ED + S) or ED without septum (ED - S) in AC patients.
Methods:
This retrospective cohort study included 31 patients with AC and esophageal diverticula (21 patients with septum and 10 patients without septum) between January 2016 and January 2025. In ED + S group, submucosal tunneling myotomy combined with diverticular septotomy was performed, while patients in the ED - S group underwent submucosal myotomy alone. The Eckardt scores before and after surgery were compared to evaluate symptom relief and clinical success. The Gastroesophageal Reflux Disease Questionnaire (GERD-Q) score and gastroscopy findings were used to evaluate postoperative gastroesophageal reflux.
Results:
The corresponding operation steps were completed in both groups, with a technical success rate of 100%. We successfully followed up with 18 and 10 patients in the ED + S and ED - S group, with a median follow-up period of 2.5 years and 3.0 years, respectively. The postoperative Eckardt scores [median (interquartile range)] were significantly lower in both groups compared with preoperative scores [ED + S group: 6.0 (4.0-8.0) vs 0 (0-2.0), P < 0.05; ED - S group: 6.0 (3.75-8.25) vs 1.0 (0-3.0), P < 0.05]. The clinical success rates (Eckardt score ≤ 3) were 88.9% and 90.0%, respectively. The GERD-Q score was used to evaluate postoperative gastroesophageal reflux, and 3 patients (3/18, 16.7%) in ED + S group and 2 patients (2/10, 20%) in ED - S group experienced symptomatic reflux (GERD-Q score ≥ 8).
Conclusion:
In AC patients with ED + S, submucosal tunneling myotomy with diverticular septotomy can achieve good therapeutic effects. When there is no obvious septum, submucosal tunneling myotomy is an effective method.

Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...