Related Experiment Video
Updated: Mar 12, 2026


A Real-World High-Intensity Interval Training Protocol for Cardiorespiratory Fitness Improvement
Published on: February 22, 2022
High-intensity interval training for reducing cardiometabolic syndrome in healthy but sedentary populations
Juliette A Strauss1, Richard Kirwan1, Chathuranga Ranasinghe2
1Research Institute for Sport & Exercise Sciences, Faculty of Science, Liverpool John Moores University, Liverpool, UK.

Rationale:
The estimated global cost of inactivity is USD (US dollar) 53.8 billion. Exercise is a low-cost, effective, and accessible intervention that can reduce cardiovascular disease risk in sedentary populations. However, nearly one-third of adults do not meet the levels of physical activity recommended by the World Health Organization (WHO). WHO guidelines do not include advice for people who wish to undertake high-intensity interval training (HIIT), because it is unclear whether HIIT is an efficacious and acceptable method for sedentary populations to reduce their risk of cardiometabolic syndrome. As lack of time is the most frequently cited barrier to exercise, and HIIT requires a lower time commitment than moderate-intensity continuous training (MICT), this topic warrants a high-quality, non-biased exploration of the literature.
Objectives:
To assess the benefits and harms of high-intensity interval training (HIIT) on cardiometabolic health in healthy, sedentary adults.
Search Methods:
We searched CENTRAL, MEDLINE, Embase, Web of Science Core Collection (SCI-Expanded, SSCi, CPCI-S), and two trial registries up to 13 October 2025.
Eligibility Criteria:
We included randomised control trials (RCTs) that compared HIIT with a non-exercise control (comparison 1) or with MICT (comparison 2) over four weeks or longer in healthy adults (aged 18-64 years) who were sedentary at baseline. We excluded studies of athletes, as we were interested in the benefits of HIIT for public health, not for performance. We also excluded studies of people with overweight (body mass index (BMI) 25-29.9 kg/m²) or obesity (BMI ≥ 30 kg/m²) who were recruited as a result of a medical event or diagnosis.
Outcomes:
Our main outcomes were cardiorespiratory fitness (measured as maximum oxygen consumption (VO2max) or peak oxygen consumption), systolic blood pressure, waist circumference, waist-to-hip ratio, all-cause mortality, circulating triglycerides, and adverse events.
Risk Of Bias:
We used the Cochrane risk of bias tool (Rob 2) to assess the risk of bias in the RCTs.
Synthesis Methods:
We synthesised results for each outcome using a random-effects meta-analysis. We used GRADE to assess the certainty of the evidence.
Included Studies:
Our review included 58 RCTs (2075 participants). Thirty-five studies evaluated HIIT versus MICT, and 11 evaluated HIIT versus no exercise. Twelve studies evaluated HIIT versus MICT versus another control (e.g. no exercise, walking); we included these studies in both comparisons in our review where possible.
Synthesis Of Results:
No studies reported all-cause mortality or adverse events. The certainty of the evidence was downgraded for inconsistency, imprecision, and risk of bias (mainly due to lack of detail on randomisation and no available protocol or trial registration). High-intensity interval training versus non-exercise control HIIT compared with a non-exercise control likely increases cardiorespiratory fitness measured with VO2max (mean difference (MD) 5.98 mL/min/kg, 95% confidence interval (CI) 4.66 to 7.30; 16 studies, 517 participants; moderate-certainty evidence) and reduces waist circumference (MD -3.56 cm, 95% CI -6.14 to -0.98; 8 studies, 270 participants; high-certainty evidence). HIIT compared with a non-exercise control likely results in little to no difference in waist-to-hip ratio (MD -0.01, 95% CI -0.03 to 0.01; 6 studies, 224 participants; moderate-certainty evidence) and may result in little to no difference in circulating triglycerides (standardised mean difference (SMD) -0.22, 95% CI -0.62 to 0.17; 9 studies, 262 participants; low-certainty evidence). The evidence for the effect of HIIT on systolic blood pressure is very uncertain (MD -5.22 mmHg, 95% CI -12.27 to 1.84; 7 studies, 215 participants; very low-certainty evidence). High-intensity interval training versus moderate-intensity continuous training HIIT may result in a slight increase in cardiorespiratory fitness (VO2max) compared with MICT (MD 1.39 mL/min/kg, 95% CI 0.44 to 2.34; 37 studies, 1115 participants; low-certainty evidence). HIIT compared with MICT likely results in little to no difference in waist circumference (MD 0.06 cm, 95% CI -1.49 to 1.62; 15 studies, 407 participants; moderate-certainty evidence) and waist-to-hip ratio (MD 0.00, 95% CI -0.01 to 0.02; 5 studies, 155 participants; moderate-certainty evidence). HIIT compared with MICT may result in little to no difference in systolic blood pressure (MD -0.56 mmHg, 95% CI -3.02 to 1.90; 18 studies, 515 participants; low-certainty evidence), and circulating triglycerides (SMD 0.00, 95% CI -0.28 to 0.27; 18 studies, 526 participants; low-certainty evidence).
Authors' Conclusions:
Compared with a non-exercise control, HIIT likely increases cardiorespiratory fitness and reduces waist circumference slightly, but we found no clear difference for systolic blood pressure, waist-to-hip ratio, or circulating triglycerides. The certainty of the evidence is low for circulating triglycerides and very low for systolic blood pressure, precluding firm conclusions. Compared with MICT, HIIT may increase cardiorespiratory fitness slightly, but we found no clear difference for systolic blood pressure, waist circumference, waist-to-hip ratio, or circulating triglycerides. The certainty of the evidence is low for cardiorespiratory fitness, systolic blood pressure, and circulating triglycerides, precluding firm conclusions. No studies in either comparison reported all-cause mortality. There were no reports of adverse events, and we are unsure if the studies actively monitored for them. Our analysis included many studies, but all had relatively few participants. The evidence suggests that HIIT may be an effective alternative to MICT for sedentary populations at risk of cardiometabolic disease. There is a need for larger, higher-quality RCTs with longer follow-up to determine the long-term efficacy and effectiveness of HIIT. Future studies should investigate the feasibility and safety of unsupervised HIIT, as all studies included in this review examined supervised HIIT interventions.
Funding:
This Cochrane review was funded (in part) by the National Institute of Health Research (NIHR) and the Foreign, Commonwealth and Development Office (FCDO).
Registration:
The protocol for this Cochrane review was published in the Cochrane Library in May 2020 and is available via 10.1002/14651858.CD013617.
More Related Videos
 09:19
Short Session High Intensity Interval Training and Treadmill Assessment in Aged Mice
Published on: February 2, 2019
 07:40
Impact of High-intensity Interval Exercise and Moderate-Intensity Continuous Exercise on the Cardiac Troponin T Level at an Early Stage of Training
Published on: October 10, 2019
Related Concept Videos
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:26
Coronary Artery Disease IV: Preventive Measures
 01:26
Exercise Stress Test
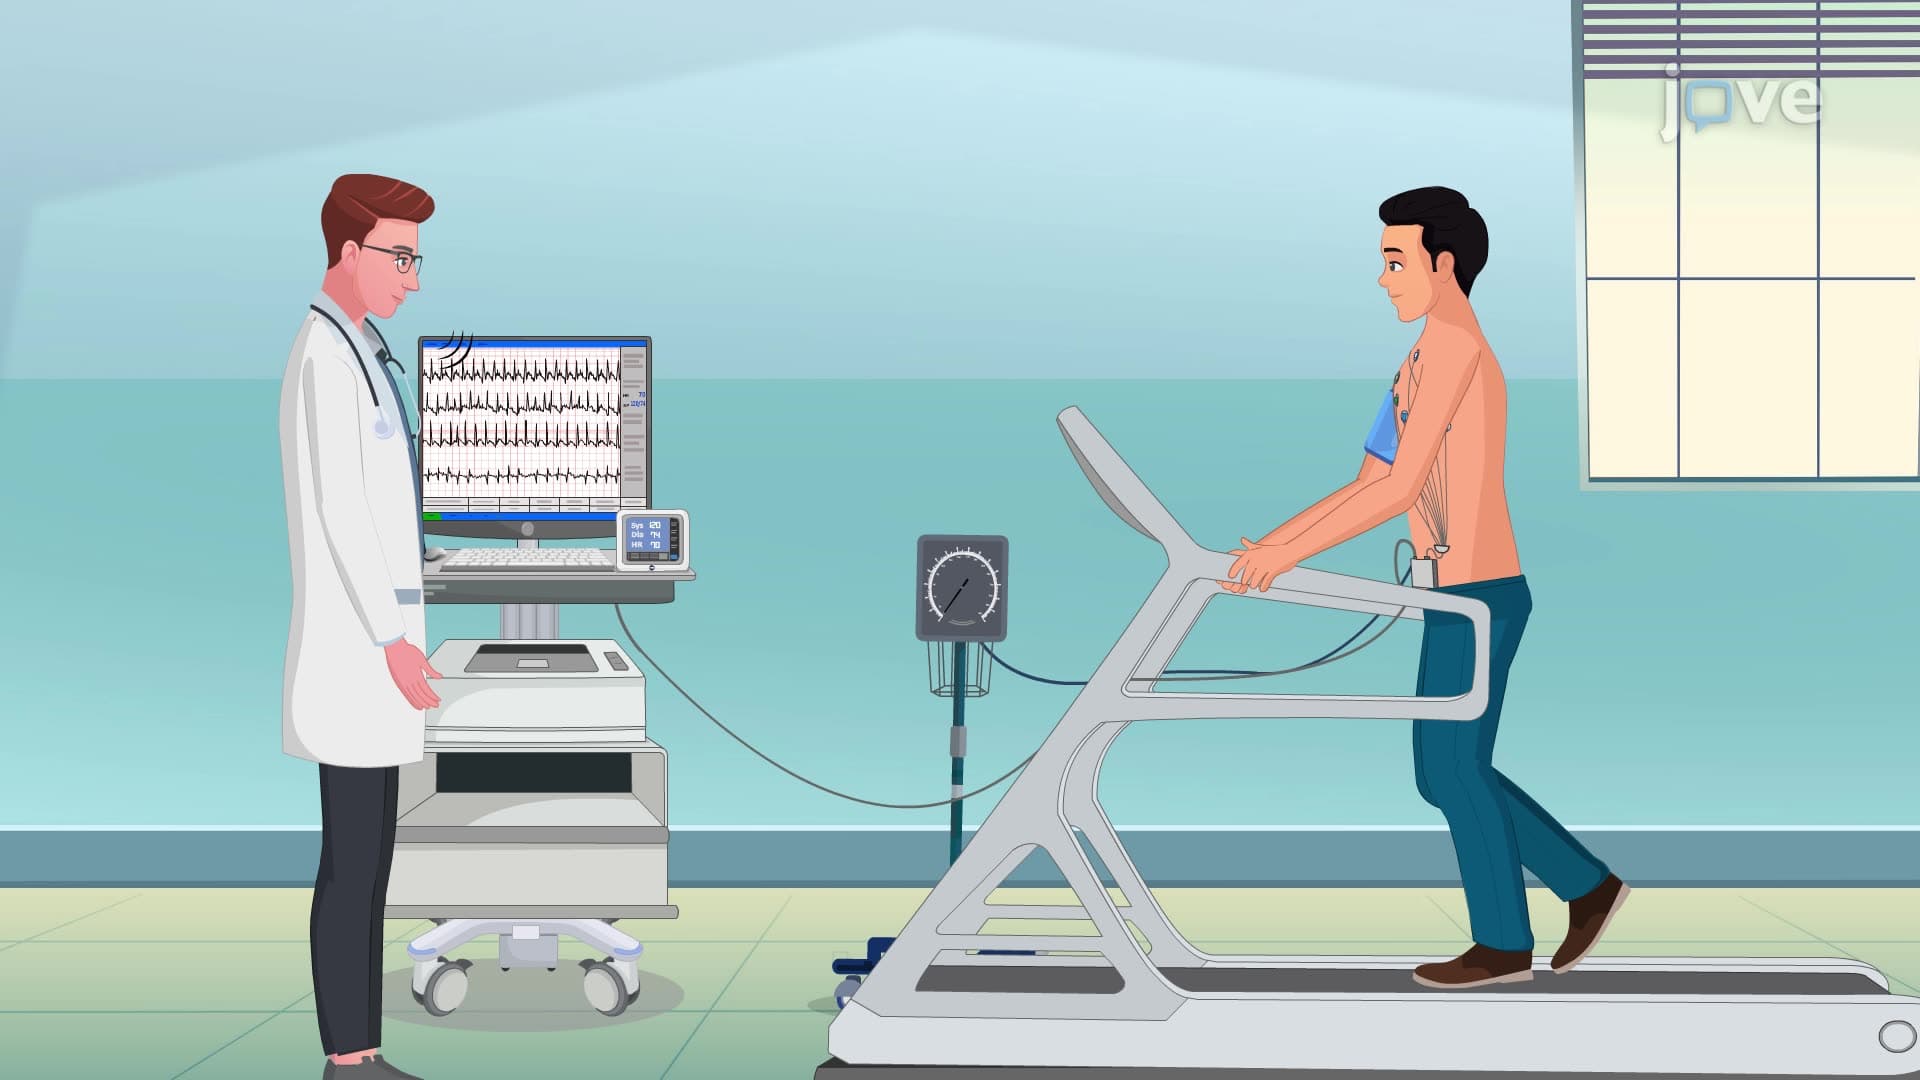
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:15
Bioavailability Study Design: Healthy Subjects Versus Patients
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...