Related Experiment Video
Updated: Mar 13, 2026

Screening of Axonal Degeneration in Carpal Tunnel Syndrome Using Ultrasonography and Nerve Conduction Studies
Published on: January 11, 2019
The Inlet Cross-sectional Area: The Most Reliable Ultrasound Parameter for the Diagnosis of Carpal Tunnel Syndrome
Zahra Soleimani-Shishavan1, Bina Eftekharsadat1, Raha Markazi-Movaghar1
1Physical Medicine and Rehabilitation Research Center, Imam Reza Hospital, Tabriz University of medical Sciences, Tabriz, Iran.

Objective:
Despite emerging interest in dynamic parameters like the ratio of median nerve-to-hamate distance for diagnosing carpal tunnel syndrome-particularly in selected populations such as hemodialysis patients-this study evaluates whether the inlet cross-sectional area retains diagnostic superiority in a general carpal tunnel syndrome population.
Design:
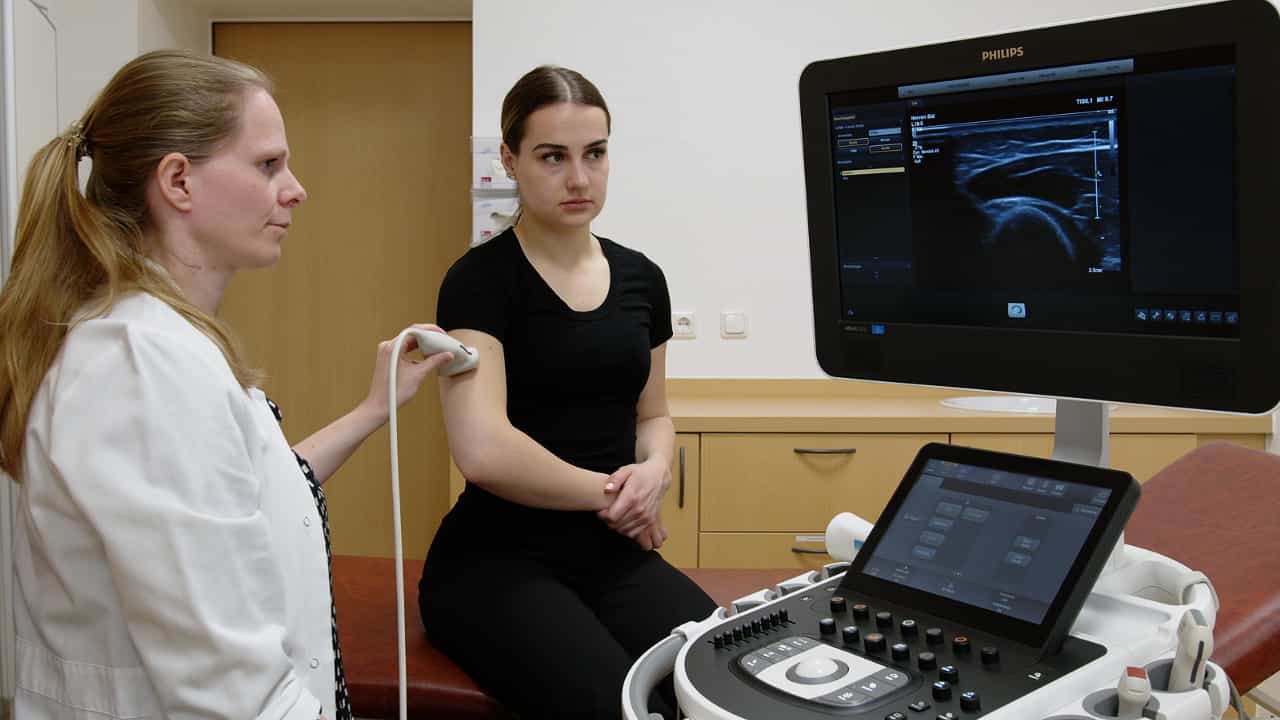
In this case-control study, 88 participants (44 carpal tunnel syndrome patients, 44 healthy controls) were recruited from a tertiary referral university hospital between November 2024 and March 2025. High-resolution ultrasonography measured median nerve parameters.
Main Outcome Measures:
Diagnostic accuracy (area under the curve, sensitivity, specificity) of inlet cross-sectional area versus outlet cross-sectional area, anteroposterior diameters (AP-I/O), flattening ratio at the outlet, and ratio of median nerve-to-hamate distance during rest/grip.
Results:
Inlet cross-sectional area demonstrated exceptional diagnostic accuracy (area under the curve = 0.93). At a cutoff of >9.5 mm 2 , inlet cross-sectional area yielded 86% sensitivity and 84% specificity. Outlet cross-sectional area showed lower accuracy (area under the curve = 0.88) and novel dynamic parameters such as ratio of median nerve-to-hamate distance performed poorly in this general population (area under the curve ≈ 0.50).
Conclusion:
Inlet cross-sectional area remains the most reliable sonographic parameter for diagnosing carpal tunnel syndrome in the general population. A inlet cross-sectional area value >9.5 mm 2 is recommended for routine clinical practice. Dynamic measures may retain value in specific subgroups but do not replace inlet cross-sectional area for general carpal tunnel syndrome evaluation.