Related Experiment Video
Updated: May 7, 2026
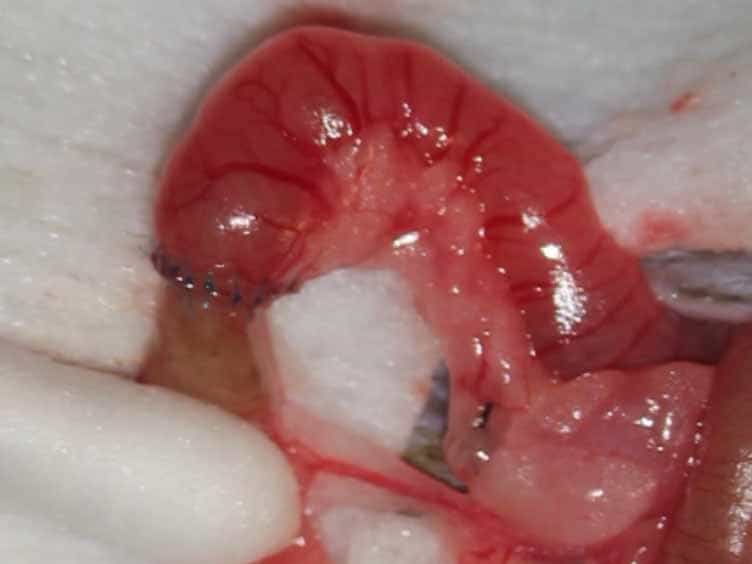
Murine Ileocolic Bowel Resection with Primary Anastomosis
Published on: October 29, 2014
Endoscopic versus surgical management for iatrogenic colonic perforations: a GRADE-assessed systematic review and
Wajahat Mirza1, Mehak Ejaz Khan2, Hania Iqbal2
1Shifa College of Medicine, Shifa Tameer-E-Millat University, Sector H-8/4, Islamabad, Pakistan. wajahatmirza.clinicalresearch@gmail.com.

Background:
Iatrogenic colonic perforation is a rare but potentially catastrophic complication of colonoscopy (0.016-0.2% diagnostic; 0.15-5% therapeutic) with reported mortality of 15-25%. Rates may increase with expanding colonoscopy volume and advanced therapeutic interventions. Endoscopic closure is increasingly used, yet comparative outcomes remain uncertain.
Methods:
Registered in PROSPERO (CRD420251233077). We searched six databases from inception to November 2025 for adult observational cohorts comparing endoscopic closure versus surgery. Outcomes included treatment success, mortality, major morbidity, reoperation, length of stay, and fasting duration. Two reviewers independently screened studies, extracted data, and assessed bias using ROBINS-I. Random-effects models pooled risk ratios (RR) and mean differences (MD); GRADE rated certainty. Sensitivity and geographic subgroup analyses assessed robustness and effect modification.
Results:
Four retrospective cohorts (n = 123; 52 endoscopic, 71 surgical) from Portugal, Korea, and Malaysia were included across care settings. Treatment success showed no clear difference (RR 1.00, 95% CI 0.94-1.06; I2 = 0%; low certainty). Mortality was rare and imprecise (8 events; RR 0.26, 95% CI 0.06-1.16; I2 = 0%; very low certainty). Hospital stay was shorter with endoscopic management (MD - 9.23 days, 95% CI - 13.74 to - 4.73; I2 = 43%; low certainty). Fasting duration did not differ significantly and was heterogeneous. No geographic subgroup effect was detected (P = 0.95). Sensitivity analysis supported robustness, except for hospital-stay heterogeneity driven by referred cases in one study.
Conclusions:
In observational cohorts, endoscopic closure was typically used for immediately recognized, smaller perforations in favorable clinical conditions, whereas surgery was preferentially used for delayed diagnosis, larger defects, or suspected contamination, introducing substantial confounding by indication. Accordingly, the pooled estimates should not be interpreted as evidence of equivalence. In carefully selected patients (immediate recognition, < 2 cm, no generalized peritonitis/instability), endoscopic closure appears to be a viable first-line strategy and may reduce length of stay. Prospective multicenter studies with standardized definitions and rigorous confounder adjustment are needed.
More Related Videos
 08:26
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
 04:05
Endoscopic Vacuum Therapy for the Treatment of Anastomotic Leakage after Total Gastrectomy with Esophagojejunostomy
Published on: August 22, 2025
Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Endoscopic Procedures II: Colonoscopy
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...