Related Experiment Video
Updated: Mar 13, 2026


Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
Extreme acidosis in hospitalised patients: A 10-year single-centre, retrospective analysis
Zoe Y Guo1, Humphrey Gm Walker1,2,3, Alastair J Brown1,2,4,5
1Department of Critical Care Medicine, St Vincent's Hospital Melbourne, Victoria, Australia.

Objective:
Acidaemia is a commonly occurring abnormality of acid-base balance. The literature assessing extreme acidosis (pH ≤ 7) is limited and is largely focused on those admitted to intensive care. Therefore, we sought to review the demographics, aetiologies, and outcomes of all hospitalised patients with extreme acidosis.
Design And Setting:
This was a retrospective cohort study conducted at a single centre, tertiary hospital in Melbourne, Australia Participants: Patients with acidosis were identified using the hospital pathology database. Exclusion criteria included hospital readmissions or samples taken in a non-inpatient setting. Main Outcome Measures: The primary outcome was 30-day mortality. Secondary outcomes included 90-day mortality and the association of mortality with type and aetiology of acidosis. Data were analysed using a Cox proportional hazards model.
Results:
Between June 2015 and June 2025, 162,697 patients had 451,788 multi-day admissions. Five hundred eighty-six admissions were identified, in which a patient had a measured pH ≤ 7.0. The final cohort consisted of 493 first admission episodes. Three hundred twenty-four (68.5 %) were male with a median age of 59.3 (interquartile range: 41.2-71.7). By day 30, 226 (45.8 %) of patients had died. Mixed acidosis (321, 65.1 %) and cardiorespiratory arrest (160, 32.5 %) were the most frequently occurring type and aetiology of acidosis. Relative to metabolic acidosis, both mixed acidosis (adjusted hazard ratio (aHR): 2.25, 95 % CI: 1.55-3.27) and respiratory acidosis (aHR: 2.08, 95 % CI: 1.01-4.27) had a higher hazard of 30-day mortality. Causes associated with the highest risk of 30-day mortality were vascular (aHR: 31.2, 95 % CI: 9.60-101) and cardiorespiratory arrest (aHR: 27.0, 95 % CI: 9.17-79.4). One hundred nine (22.1 %) patients did not require intensive care unit admission; however, 37 (33.9 %) of these patients still had died by day 30.
Conclusions:
Extreme acidosis is extremely rare in hospitalised inpatients. Mortality varies according to type and aetiology of the cause of acidosis and therefore careful consideration as to the implications of extreme acidosis when considering cessation of treatment is crucial.
More Related Videos
 05:16
Cutoff Value of Phase Angle by Bioelectrical Impedance Analysis at Admission as a Prognostic Factor in Patients with Acute Heart Failure
Published on: June 10, 2025
 11:02
Identification and Quantification of Deranged Metabolites in Critically Ill Patients Using NMR-Based Metabolomics
Published on: November 29, 2024
Related Concept Videos
 01:24
Diagnosing Acidosis and Alkalosis
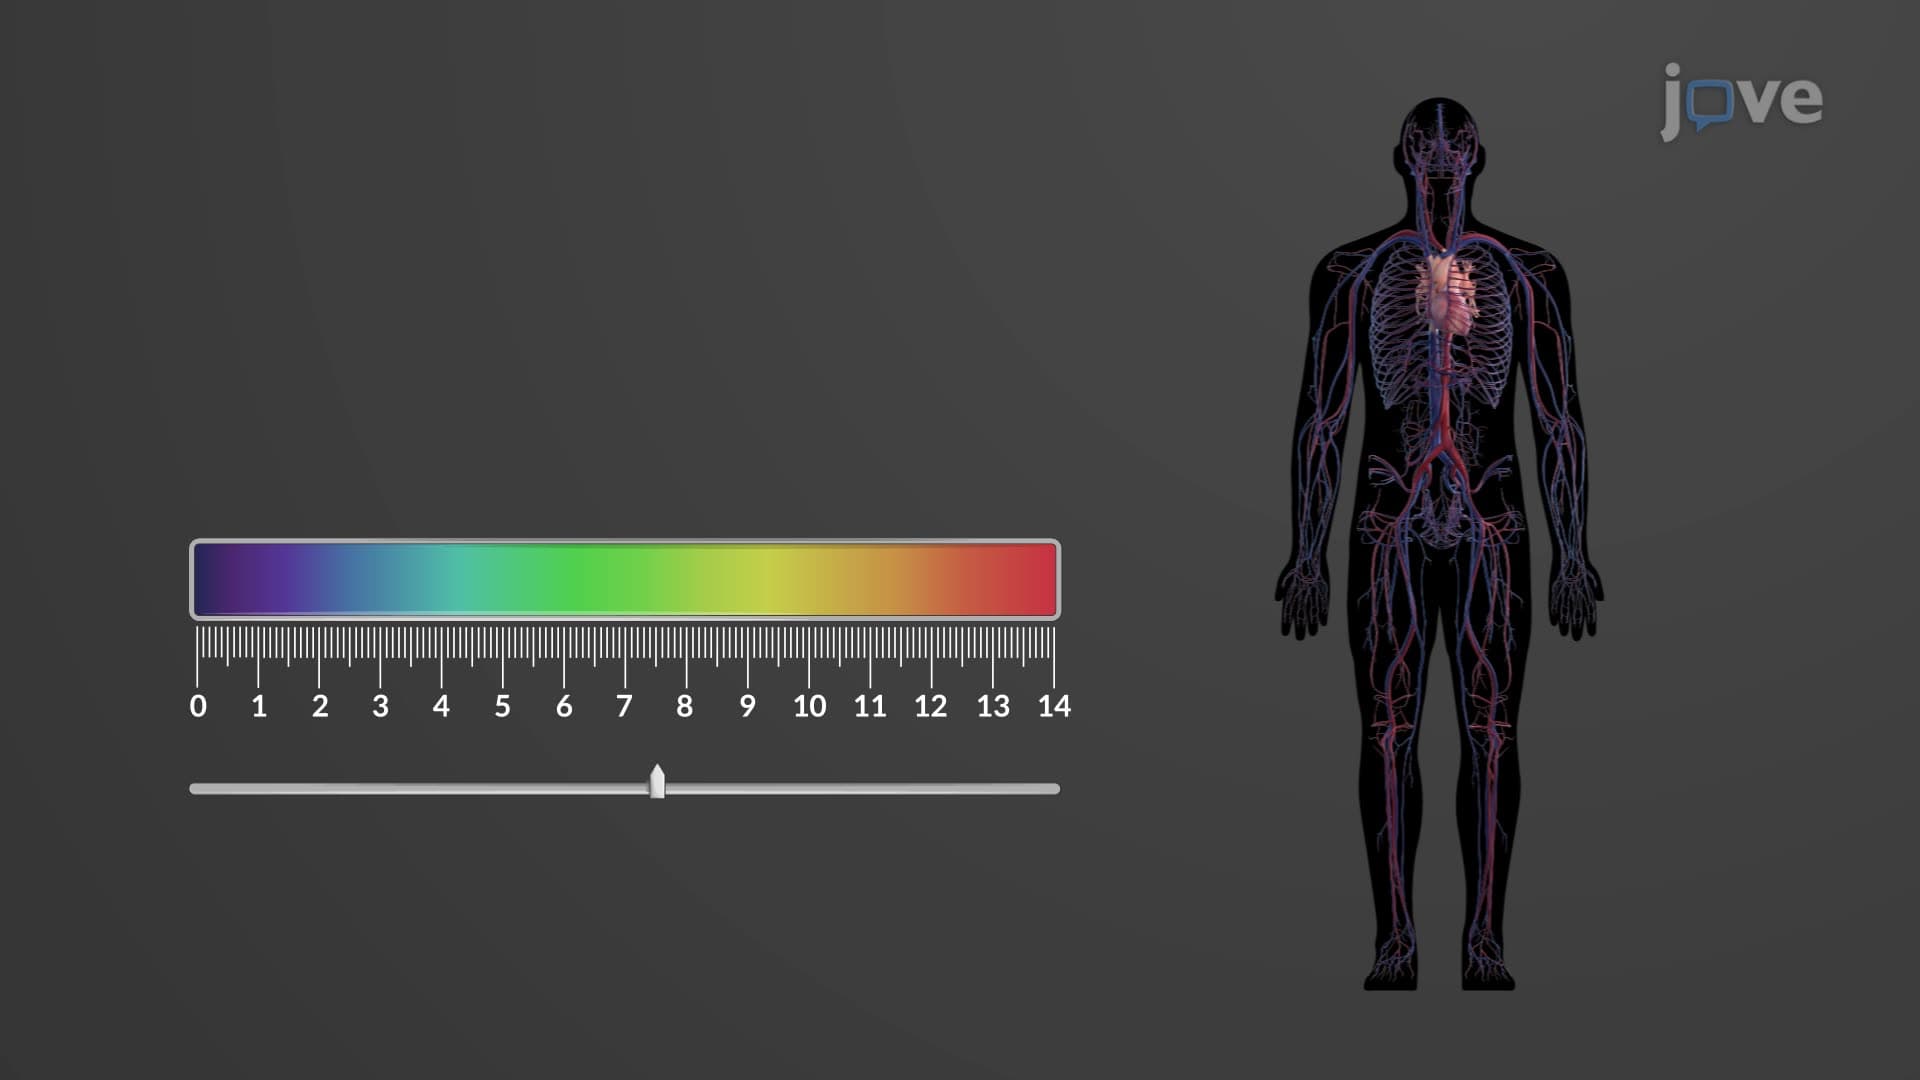
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:29
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:30
Acute Respiratory Failure-III
 01:29
Renal Regulation of Acid-Base Balance
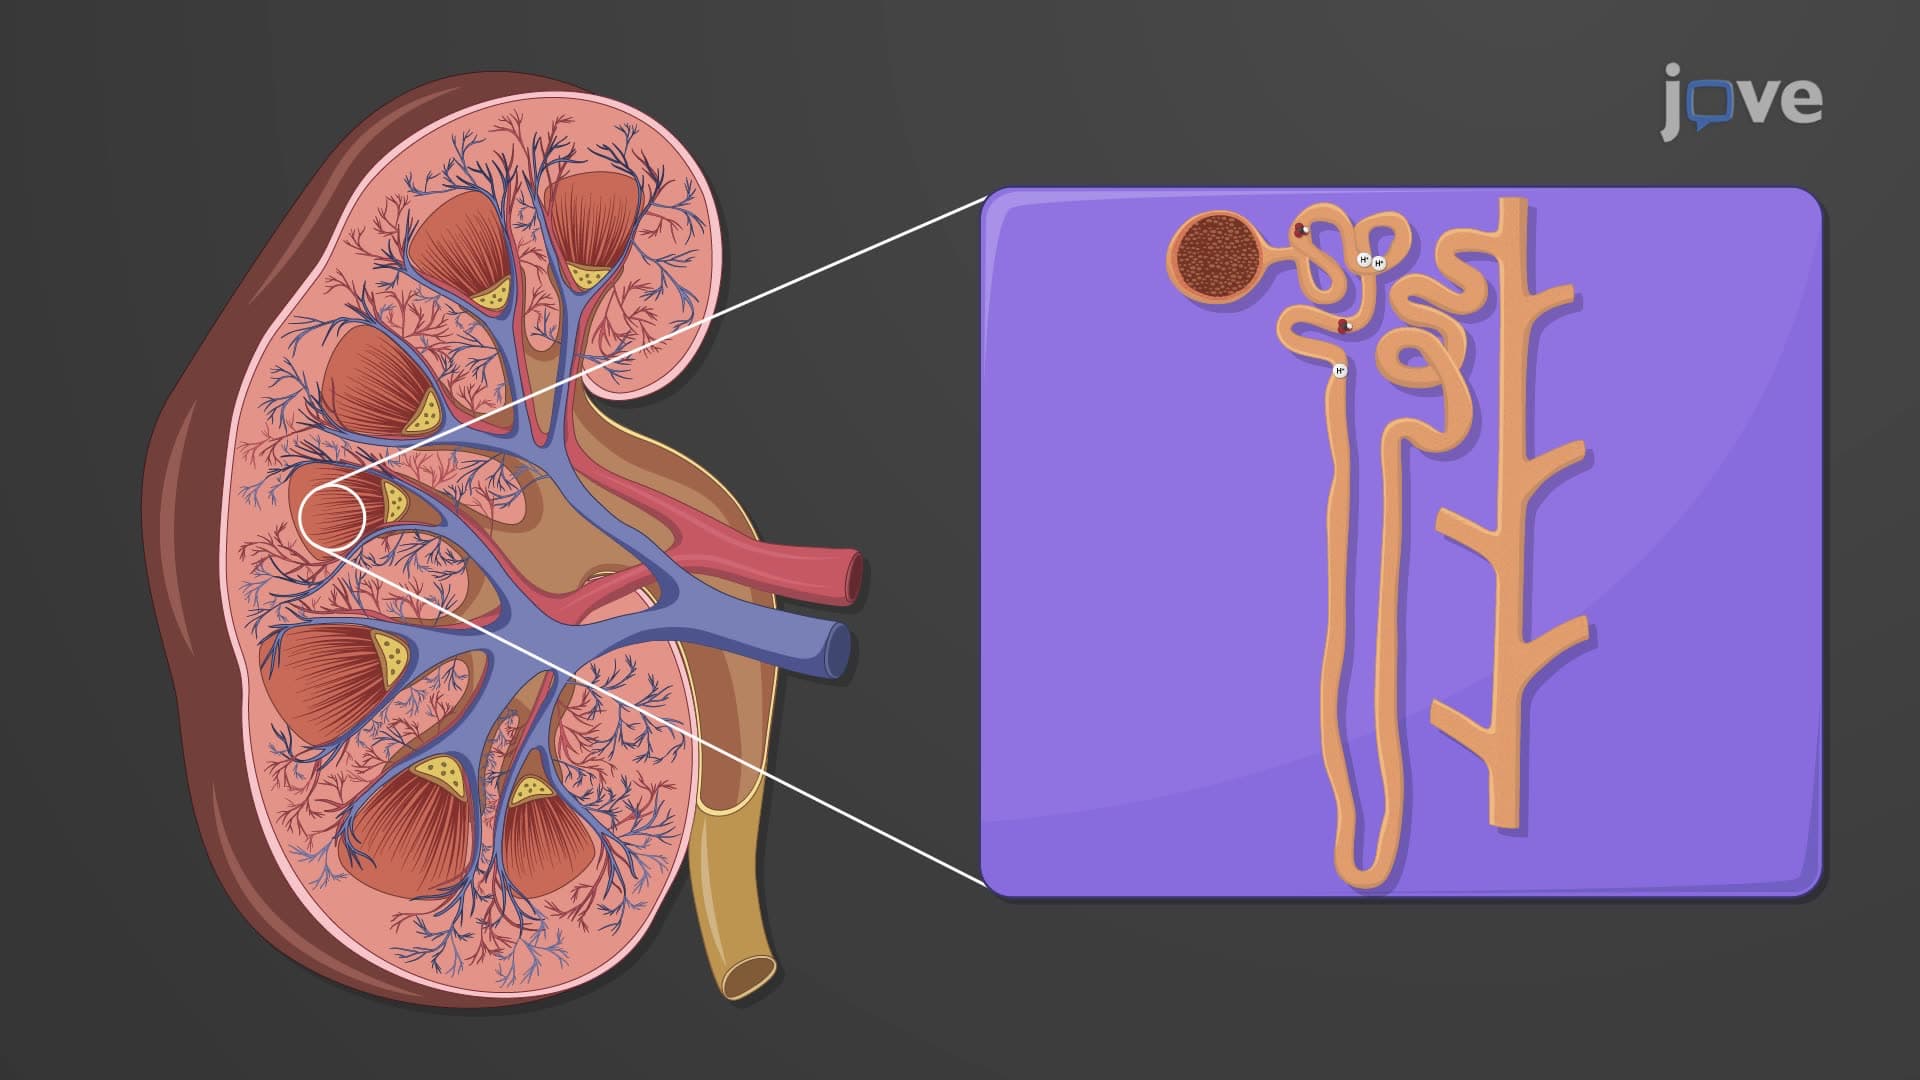
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:25
Acid-Base Balance
When the pH of arterial blood rises above 7.45, it results in a condition called alkalosis. Conversely, a drop below 7.35 leads to...
 01:18
Respiratory Regulation of Acid-Base Balance
When carbon dioxide levels increase in the blood, more H+ and HCO3⁻ are...