Related Experiment Video
Updated: May 9, 2026
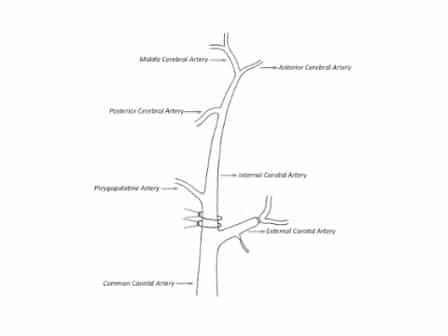
Intraluminal Middle Cerebral Artery Occlusion MCAO Model for Ischemic Stroke with Laser Doppler Flowmetry Guidance in Mice
Published on: May 8, 2011
Successful anesthesia management for middle cerebral artery thrombectomy in a patient with asynchronous
Lin Zhang1, Zhuang Liu2, Tingting Wu2
1Department of Anesthesia and Perioperative Medicine, Qingdao Central Hospital, University of Health and Rehabilitation Sciences (Qingdao Central Hospital), Qingdao, Shandong, China.

Insights
Cardio-cerebral infarction (CCI) involves stroke after heart attack. This case study details successful non-intubated anesthesia management for a patient with CCI, offering insights for similar high-risk cases.
Area of Science:
- Cardiology
- Neurology
- Anesthesiology
Background:
- Cardio-cerebral infarction (CCI) is a rare syndrome linking acute ischemic stroke (AIS) and acute myocardial infarction (AMI).
- No evidence-based guidelines exist for perioperative anesthesia in CCI patients.
- This case highlights the challenges of managing CCI with severe cardiac dysfunction and a left ventricular thrombus.
Background:
Cardio-cerebral infarction (CCI) is a rare syndrome characterized by acute ischemic stroke (AIS) occurring shortly after acute myocardial infarction (AMI). Currently, there are no evidence-based guidelines for perioperative anesthesia management in patients with CCI.
Case Summary:
A 58-year-old male underwent coronary stent implantation for acute myocardial infarction (AMI) 4 days prior and was admitted for emergency mechanical thrombectomy due to occlusion of the right middle cerebral artery. Preoperative transthoracic echocardiography revealed left ventricular systolic dysfunction (ejection fraction <40%), segmental wall motion abnormalities, and a left ventricular apical thrombus, this case extends beyond simple post-myocardial infarction thromboembolism because the patient's AIS occurred in the specific context of acute, severe cardiac dysfunction (EF <40%) with a documented left ventricular thrombus-a direct embolic source stemming from the recent AMI. This fulfills the criteria for "asynchronous cardio-cerebral infarction", where the brain insult is a direct consequence of the cardiac event within a short temporal window. Anesthesia was managed using a non-intubated general anesthesia approach, involving titration of sedation with sufentanil and remifentanil, combined with norepinephrine to maintain mean arterial pressure (MAP) within ±20% of baseline. The risk of ischemia and hemorrhage was balanced with restrictive fluid management and continuous infusion of tirofiban. Intraprocedural hemodynamics remained stable, and the procedure was successfully completed. The patient was transferred to the general ward on postoperative day three and discharged on day eleven. Troponin I and brain natriuretic peptide (BNP) levels showed a downward trend, with no evidence of heart failure, hemorrhagic transformation, or acute kidney injury.
Conclusion:
In this case of CCI patients, immediate echocardiography was helpful in quickly assessing cardiac function and determining the source of the thrombus. Non-invasive general anesthesia was beneficial in maintaining hemodynamic stability and airway safety. The multidisciplinary individualized anesthesia plan developed in this challenging scenario may provide practical references for perioperative management of similar high-risk CCI patients, but its general applicability still needs to be verified in larger-scale studies.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management