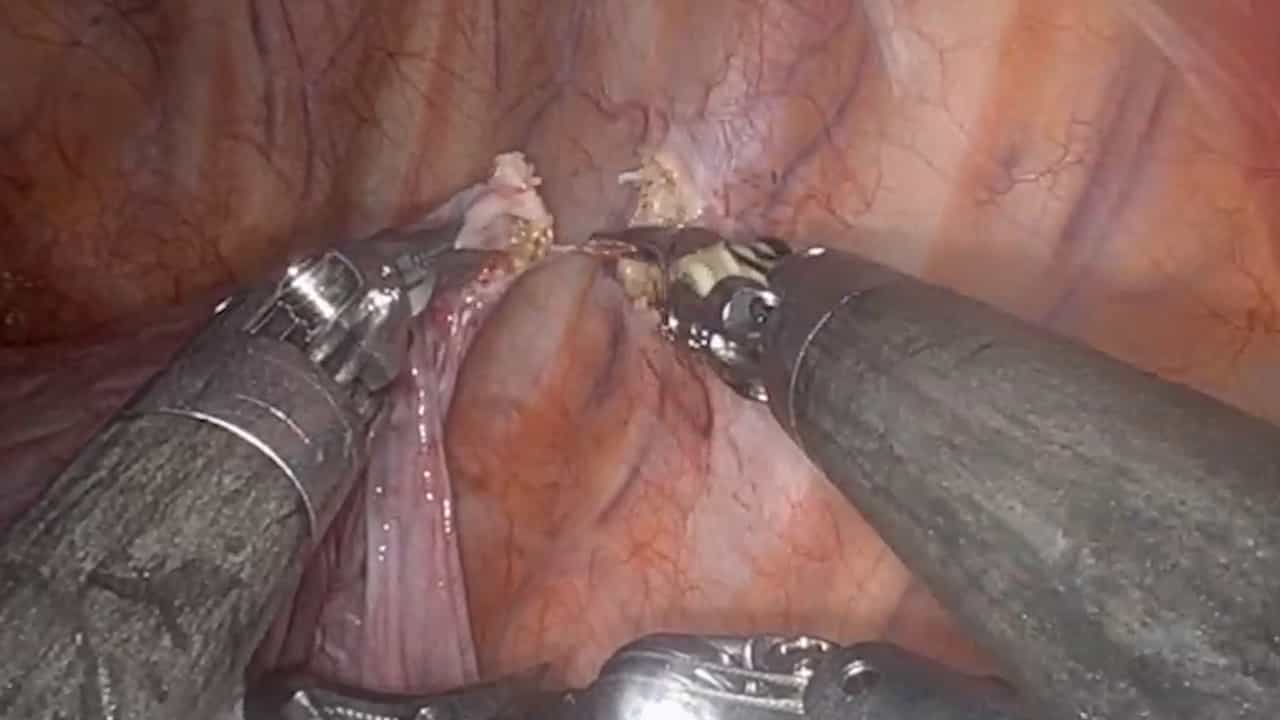
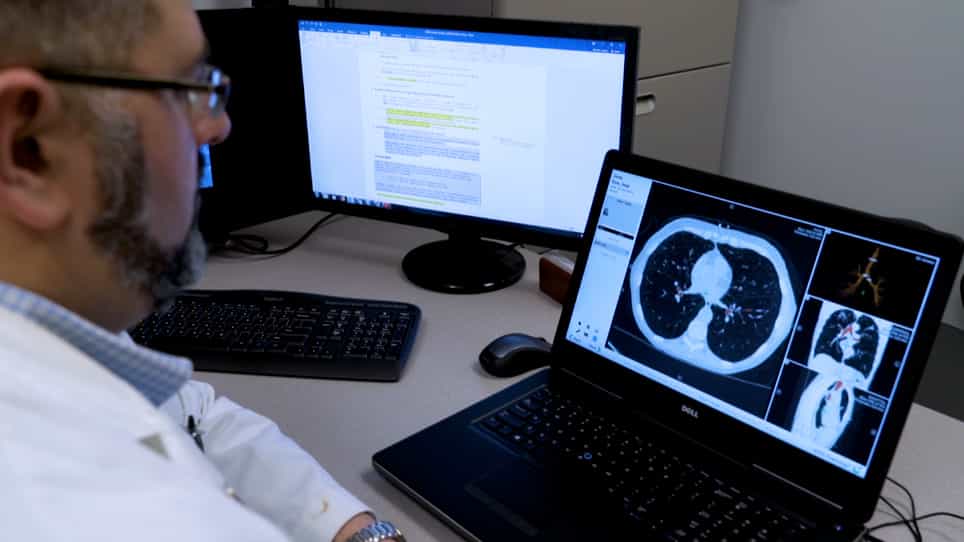
Related Experiment Video For Cavitary lung lesions
Updated: Mar 13, 2026

Author Spotlight: Expanding Interventional Pulmonology Research with Robotic-Assisted Bronchoscopy
Published on: July 19, 2024
Synergistic use of robotic navigational platform and ultrathin bronchoscopy in diagnostic yield optimization for
1Los Angeles General Medical Center + University of Southern California, Los Angeles, CA, USA.

Background:
Cavitary lung lesions represent a diagnostic challenge due to their heterogeneous etiology, which includes infectious, inflammatory, and malignant processes. Establishing an accurate diagnosis is essential, yet conventional techniques such as computed tomography-guided transthoracic biopsy, surgical biopsy and standard bronchoscopy may be limited by complication risk or suboptimal yield. Recent advances in robotic and ultrathin bronchoscopy have improved precision and reach, but their combined application remains underexplored.
Case Description:
We conducted a retrospective case series of six consecutive patients with cavitary lung lesions evaluated at a tertiary academic medical center. All procedures were performed by a single interventional pulmonologist using a standardized workflow. Pre-procedural lesion marking and airway mapping were completed in all cases with Intuitive PointPlan software to generate a virtual navigation roadmap. Ultrathin flexible bronchoscopy (Vathin disposable bronchoscope; 3.2-mm outer diameter, 1.2-mm working channel) was used in all patients to access and sample the target cavities. In four cases performed under general anesthesia, the IonTM robotic bronchoscopy platform was additionally employed for navigational guidance and fluoroscopy-assisted biopsy, followed by ultrathin bronchoscopy to allow direct intracavitary visualization and targeted sampling. Successful navigation to the cavitary lesion was achieved in all six procedures. The combined robotic-ultrathin bronchoscopy approach provided additional diagnostic information beyond robotic-guided sampling alone in two of four cases. No procedure-related pneumothorax or significant bleeding occurred. One patient developed a transient post-procedural fever that resolved with antibiotic therapy. At 3-month follow-up, all patients demonstrated radiologic or symptomatic improvement consistent with the final diagnosis.
Conclusions:
The combined use of navigational robotic and ultrathin flexible bronchoscopy is a feasible, safe, and potentially superior approach for evaluating cavitary lung lesions. This workflow integrates precise navigation with direct intracavitary visualization, optimizing diagnostic yield while minimizing procedural risk.