Related Experiment Video For Indocyanine green fluorescence (ICG fluorescence)
Updated: Jul 7, 2026

Fluorescent Laparoscopic Central Hepatectomy for Liver Cancer Using Indocyanine Green Negative Staining
Published on: March 17, 2023
CT-guided indocyanine green fluorescence localization demonstrates superior reliability over hook-wire for pulmonary
Wen-Xin Zheng1, Yi-Nan Zhang1, Chang-Yong Tong1
1Department of Thoracic Surgery, The First Affiliated Hospital of Ningbo University, Ningbo, China.

Background:
Lung cancer is the leading cause of cancer-related mortality worldwide. With the widespread use of computed tomography (CT) screening, pulmonary ground-glass nodules are increasingly detected. Video-assisted thoracoscopic surgery (VATS) enables minimally invasive resection; however, the precise intraoperative localization of these non-palpable nodules remains challenging. The current commonly used preoperative CT-guided hook-wire localization, while effective, is associated with documented risks such as dislodgement (reported in up to ~10% of cases), pneumothorax requiring intervention, and rare but serious complications (e.g., air embolism). Thus, a safer and more reliable localization technique is desirable. Indocyanine green (ICG) fluorescence guidance has emerged as a promising alternative, though further validation in standardized cohorts is valuable. This study aimed to evaluate the feasibility and safety of ICG fluorescence localization and resection of pulmonary ground-glass nodules under near-infrared (NIR) fluorescence thoracoscopy.
Methods:
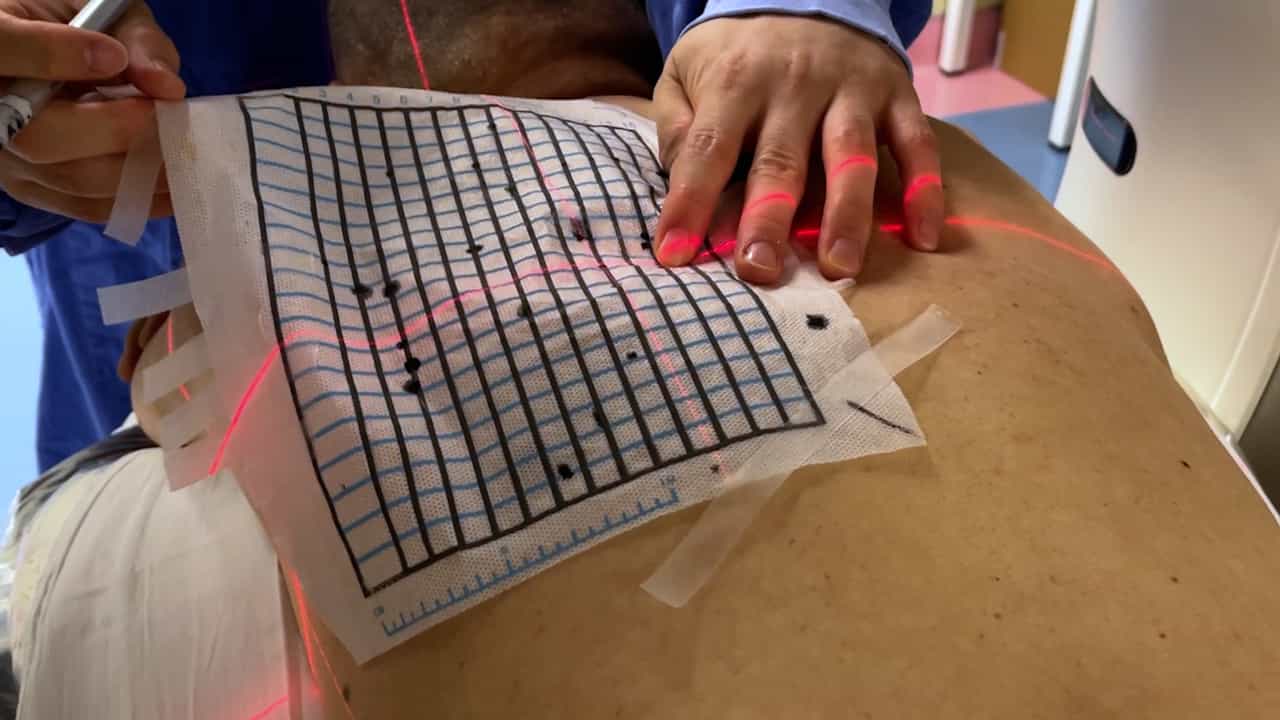
We retrospectively analyzed the data of patients with pulmonary ground-glass nodules (peripheral type, diameter <2 cm) treated at the Department of Thoracic Surgery, The First Affiliated Hospital of Ningbo University from July 2022 to September 2022 and compared these data with a historical control group (n=23) who underwent CT-guided hook-wire localization between January and July 2015. Under CT guidance, we percutaneously injected diluted ICG (0.5-1 mL) near the target nodule, and the surgical team observed the fluorescence of the ICG by NIR thoracoscopy for localization and wedge resection.
Results:
A total of 104 ground-glass nodules were identified from 94 patients who underwent resection by NIR thoracoscopic surgery. The median diameter of the nodules was 6 mm (range, 2-16 mm), and the median distance from the pleura was 9 mm (range, 2-28 mm). The median duration of the localization procedure was 15 min (range, 8-28 min). ICG fluorescence was clearly identified in 87 nodules [92.6%; 95% confidence interval (CI): 85.3-96.5%]. Minor complications occurred in 15 cases (16.0%; 95% CI: 9.9-24.5%) following puncture. The surgical margins were pathologically negative, and no further resection was required. According to postoperative pathology, there were 30 nodules (28.8%) of adenocarcinoma in situ, 53 (51.0%) of microinvasive adenocarcinoma, 6 (5.8%) of invasive adenocarcinoma, and 15 (14.4%) of benign nodules. Compared to the hook-wire control group, the ICG group exhibited a comparable overall procedural complication rate (16.0% vs. 26.1%, P=0.26). However, the ICG technique entirely eliminated the need for conversion to lobectomy due to localization device failure (0% vs. 8.7%, P=0.04), demonstrating superior reliability.
Conclusions:
CT-guided percutaneous injection of ICG combined with intraoperative NIR localization is a safe and feasible method for localizing pulmonary ground-glass nodules, demonstrating a high success rate in this cohort. This study supports the clinical utility of this technique as a practical alternative.