Related Experiment Video
Updated: Mar 13, 2026

Author Spotlight: Advancing 3D Modeling for Enhanced Diagnosis and Treatment of Pulmonary Nodules in Early-Stage Lung Cancer
Published on: October 13, 2023
Spatial classification of clinical T1a-bN0 non-small cell lung cancer in superior segment based on three-dimensional
Yihan Yang1, Qianrui Ren1, Zhibo Wang1
1Department of Thoracic Surgery, The First Affiliated Hospital of Nanjing Medical University, Nanjing, China.

Background:
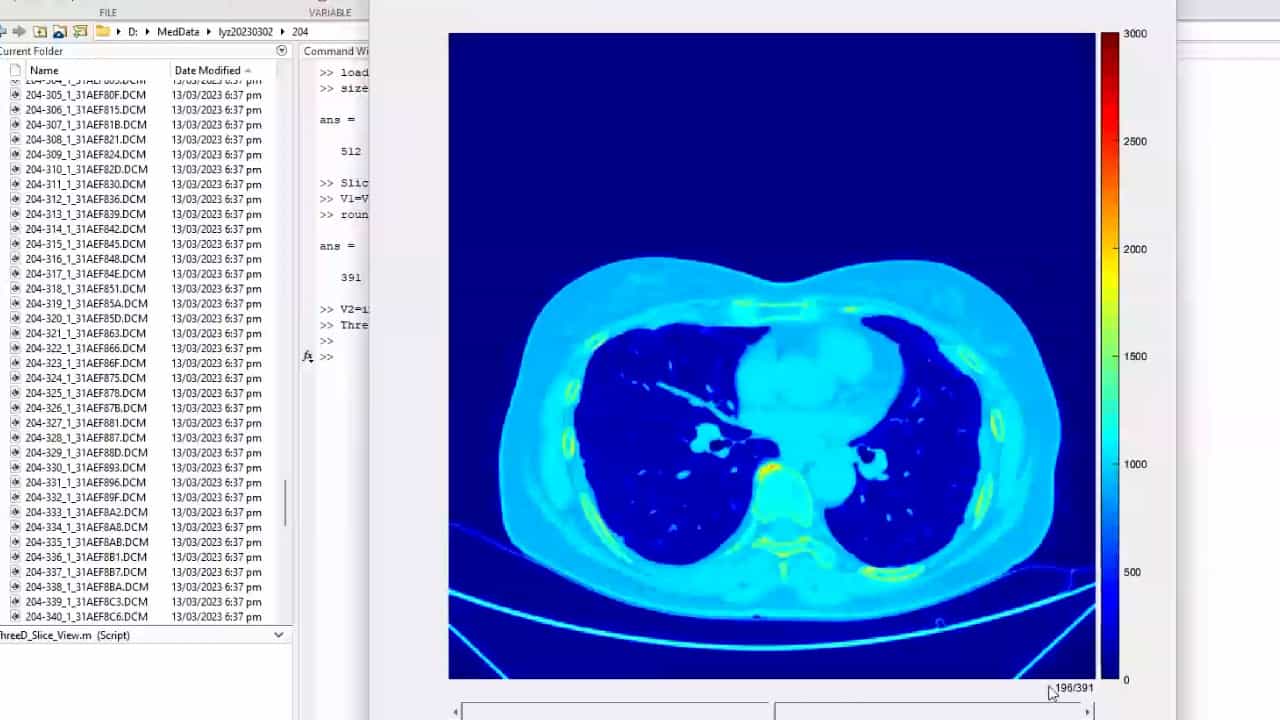
In segmentectomies of the superior segment (S6) for early-stage non-small cell lung cancer (NSCLC), inadequate surgical margins remain a critical challenge. This study aims to establish a three-dimensional (3D) spatial classification system for S6 tumors to analyze margin adequacy and optimize surgical planning.
Methods:
This retrospective cohort study included 699 patients with clinical T1a-bN0 S6 NSCLC who underwent thoracoscopic surgery between 2019 and 2023. Tumors were classified into three categories using the "InFerVision" software. S6-I had a margin sphere located above the intersegmental plane. S6-II had a margin sphere extending below the intersegmental plane and was further subdivided into S6-IIa (not involving main subsegmental structures of the basal segments) and S6-IIb (involving main subsegmental structures of the basal segments). S6-III had a margin sphere involving main trunks of the lower lobe. Primary outcomes included margin distance and the margin/diameter ratio, with the ratio ≥1 considered adequate.
Results:
The cohort comprised 388 (55.5%) S6-I, 248 (35.5%) S6-II, and 63 (9.0%) S6-III cases. Margin adequacy differed significantly among groups: S6-I exhibited a median margin of 2.50 cm [interquartile range (IQR), 2.00-3.50 cm], with 99.0% meeting margin/diameter ratio ≥1; S6-II showed a median margin of 1.80 cm (IQR, 1.30-2.20 cm) with 85.9% meeting the ratio threshold; and S6-III yielded a median margin of 1.00 cm (IQR, 0.70-1.20 cm), with only 57.1% achieving a ratio ≥1. Further analysis within the S6-II group revealed that the S6-IIb subgroup required subsegment-based S6 resection (S6c) to achieve satisfactory margins, with a median margin of 1.80 cm (IQR, 1.50-2.00 cm) compared to 0.80 cm (IQR, 0.60-1.37 cm) for segment-based S6 resection (S6n) (P<0.001).
Conclusions:
This 3D spatial classification system effectively addresses the margin insufficiency problem in S6 segmentectomies. It provides preoperative guidance for selecting surgical strategies, recommending S6c for S6-IIb tumors and lobectomy consideration for S6-III lesions.