Related Experiment Video
Updated: Mar 13, 2026


Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Dynamics of diaphragmatic endometriosis with thoracic endometriosis-related pneumothorax
Kota Ohashi1, Masatoshi Kurihara1, Kenji Tsuboshima1
1Pneumothorax Research Center and Division of Thoracic Surgery, Nissan Tamagawa Hospital, Tokyo, Japan.

Background:
Pneumothorax that occurs during menstruation is called catamenial pneumothorax; however, it is also called thoracic endometriosis-related pneumothorax (TERP) because of its etiology. Because of its high postoperative recurrence rate, TERP often remains unresolved. Diaphragmatic endometriosis is often observed with TERP, but its detailed mechanism has not yet been elucidated. This study aimed to clarify the dynamics and mechanisms of endometrial tissue engraftment on the diaphragm observed with TERP.
Methods:
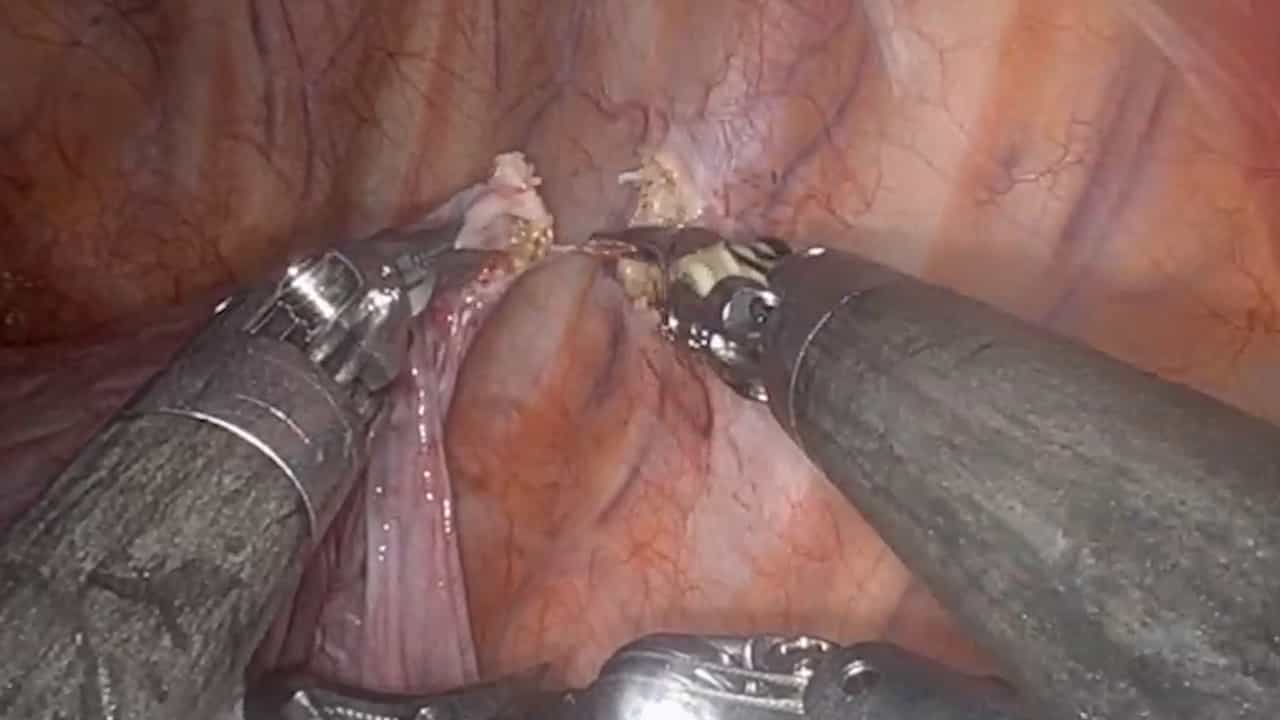
A total of 140 patients with TERP who underwent the initial video-assisted thoracic surgery (VATS) at our hospital between January 2018 and December 2023 were eligible for enrollment in this study; however, 10 patients were subsequently excluded. Diaphragmatic lesions were morphologically classified as hiatus, hematoma, and scar lesions. The diaphragmatic regions were divided into four equal areas by virtually drawing lines parallel and perpendicular to the coronary ligament in the membrane area ventral to the coronary ligament of the diaphragm. The ventral lateral part was designated as area A, and the other parts (proceeding in a counterclockwise direction) were designated as areas B, C, and D. The area dorsal to the coronary ligament was designated as area E. Endometrial tissue distribution was determined based on surgical reports and intraoperative images.
Results:
All diaphragmatic endometrial lesions were located in area A (n=130 patients; 100%), whereas the others were located in area B (52 patients; 40%) and area D (21 patients; 16%). Hiatus, hematoma, and scar lesions were found in area A in more than 60% of patients, as well as in areas B and D. Three lesions were found in area C (2%). Hematoma and scar lesions were found in area E (2%).
Conclusions:
Diaphragmatic endometriosis frequently invades the thoracic cavity at the ventral side of diaphragm membrane. Hiatus lesions are unique to diaphragmatic endometriosis. The synergistic effect of physical traction during the respiratory movement of the diaphragm and the protein dissolution phenomenon of endometrial tissue engraftment may possibly form hiatus lesions.
Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:17
Pulmonary Cycle: Exhalation
 01:25
Muscles of the Thorax
The diaphragm is at the core of thoracic musculature, the primary muscle involved in breathing. This expansive, dome-shaped muscle marks the division between the thoracic and abdominal cavities. It...
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...