Robotic credentialing and simulation-based training: An institutional perspective
Related Experiment Video
Updated: Mar 14, 2026
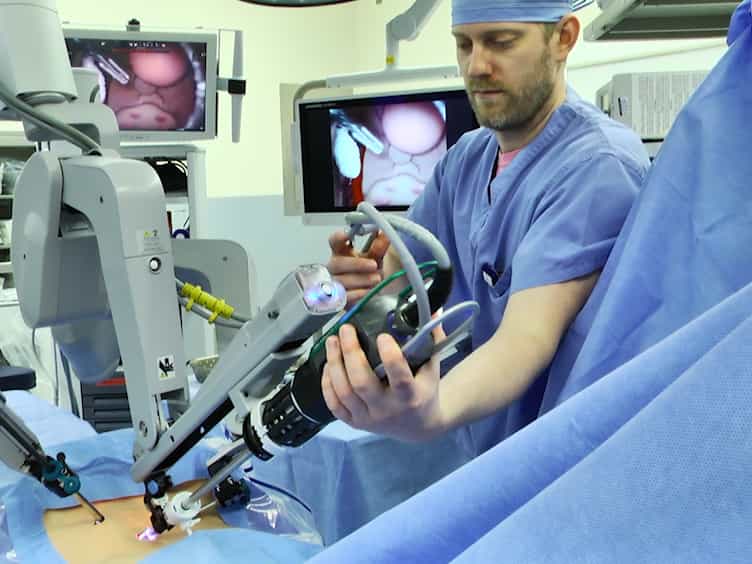
Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
1Uro-Oncology Division, Max Super Speciality Hospital, Ghaziabad, Uttar Pradesh, India.

Introduction:
Simulation-based training has emerged as a critical tool in the acquisition of robotic surgical skills, especially in urology, where procedures are highly complex and technology-intensive. My article evaluates current simulation modalities, training curricula and institutional credentialing frameworks to establish safe, reproducible and standardised pathways for robotic surgery competency. Emphasis is placed on structured simulation, mentorship and validated assessment tools.
Patients And Methods:
Literature on robotic surgical education, simulation platforms (virtual reality [VR], augmented reality [AR] and high-fidelity) and credentialing practices was reviewed (2001-2025). Institutional data from an internal credentialing framework, including simulation-based training hours, structured assessments (Global Evaluative Assessment of Robotic Skills, Robotic Objective Structured Assessment of Technical Skills) and mentored case logs, were incorporated. Intuitive's training certification pathway was described as implemented in our setting.
Results:
Institutional adoption of structured simulation (20 h on da Vinci Skills Simulator, validated assessments and 30 mentored cases) resulted in measurable improvements in surgeon performance. Trainees credentialed through simulation-based pathways demonstrated 45% fewer console-related errors in their early independent cases and a 30% reduction in operative time compared to non-simulation-trained counterparts (unpublished data). Simulation enhanced confidence, standardisation and reproducibility in skill acquisition. Challenges identified included high costs, limited access in resource-constrained settings, variability in validation across simulators and incomplete assessment of non-technical skills.
Conclusion:
Simulation-based training is a cornerstone for robotic credentialing in urology, enabling safe skill acquisition and reducing early learning curve-related complications. Institutional credentialing frameworks integrating structured curricula, validated assessment tools and supervised operative exposure provide a reproducible model for competency. Future directions should emphasise artificial intelligence-driven adaptive feedback, integration of VR/AR 'digital twins', cloud-based training ecosystems and harmonised global standards for credentialing.