Related Experiment Video
Updated: Mar 14, 2026

Dynamic Lung Tumor Tracking for Stereotactic Ablative Body Radiation Therapy
Published on: June 7, 2015
Respiratory motion effects and plan robustness for lattice radiation therapy
Rachael M Martin-Paulpeter1, Peter A Balter1, Luis A Perles1
1Department of Radiation Physics, The University of Texas MD Anderson Cancer Center, Houston, TX, United States.

Introduction:
Lattice radiation therapy (LRT), a form of spatially fractionated radiation therapy (SFRT), has shown promise in treating bulky tumors. It consists of hot and cold spots within the tumor, and the ratio between these doses is thought to be important in clinical outcomes. Respiratory motion is expected to degrade these peak-to-valley dose ratios (PVDRs) but has largely been ignored in LRT literature and clinical practice. This work aims to quantify the response of LRT dose distributions to motion to better inform motion management decisions and improve clinical outcomes.
Methods:
Respiratory motion of peak-to-peak amplitudes from 0.3 to 2 cm was simulated in 1 and 1.5 cm sphere lattice plans in a uniform phantom using dose perturbations. A similar analysis was repeated with retrospective patient plans to understand the effect of anatomical variation in motion response. Finally, deformed and rigid dose transformations were compared to understand the effect of tumor deformation on motion response.
Results:
Hot spheres (VTVH) lost coverage with increasing motion, while cold spheres (VTVL) experienced either an increase (anterior-posterior motion) or a decrease (superior-inferior motion). The ratio of the two (VTVH/VTVL D95%) decreased with increasing motion. Patient data results generally agreed with phantom results; 1.5 cm sphere plans were less sensitive to motion than 1 cm sphere plans, with statistical differences between the two responses. Mean (standard deviation) percent changes from no motion to 1 cm superior-inferior motion for patient plans are as follows with phantom values listed after: VTVH D80% change was -13.8 (1.2), -12.7 for 1.5 cm spheres and -15.8 (1.8), -13.8 for 1 cm spheres; and VTVH/VTVL D95% change was -7.1 (4.0), -15.0 and -13.0 (3.5), -12.0, respectively. Generally, no significant difference was observed between deformed and perturbed dose distributions.
Discussion:
Large tumor motion can degrade LRT dose distributions, which could lead to less effective treatments. Suggested cutoffs of 1 cm motion for 1.5 cm sphere plans and 0.5 cm motion for 1 cm sphere plans are proposed above which motion limiting strategies should be applied. Caution should be applied for tumors with large deformations, as these may change the dose distributions in unexpected ways.
More Related Videos
 08:54
Treatment of Liver Metastases Using an Internal Target Volume Method for Stereotactic Body Radiotherapy
Published on: May 8, 2018
 06:53
Management of Respiratory Motion Artefacts in 18F-fluorodeoxyglucose Positron Emission Tomography using an Amplitude-Based Optimal Respiratory Gating Algorithm
Published on: July 23, 2020
Related Concept Videos
 01:22
Planar Rigid-Body Motion
Planar motion is typically divided into three distinct categories. The first is rectilinear translation, demonstrated by a subway train that moves along...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:17
Radiation: Applications
The average...
 01:15
Respiratory Volumes
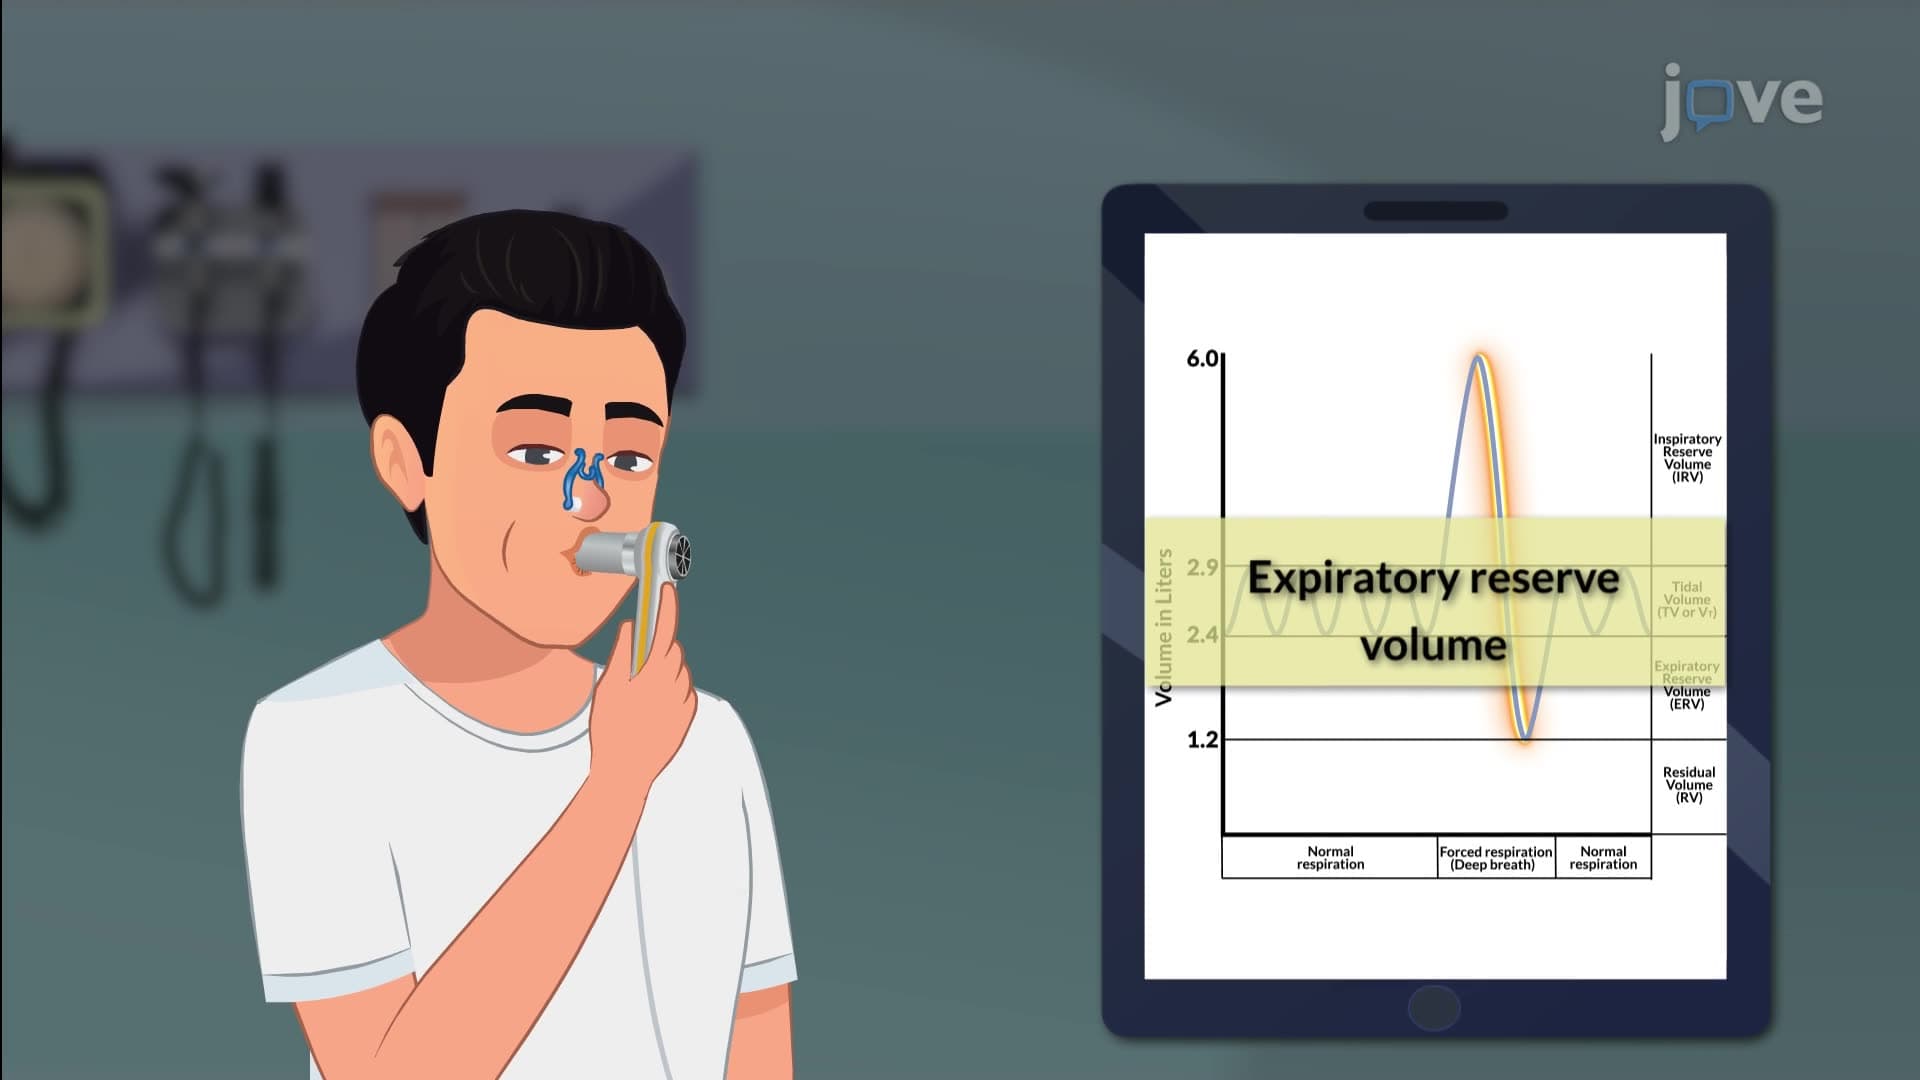
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:26
Respiratory Volumes and Capacities I
 01:09
Radiation Pressure: Problem Solving
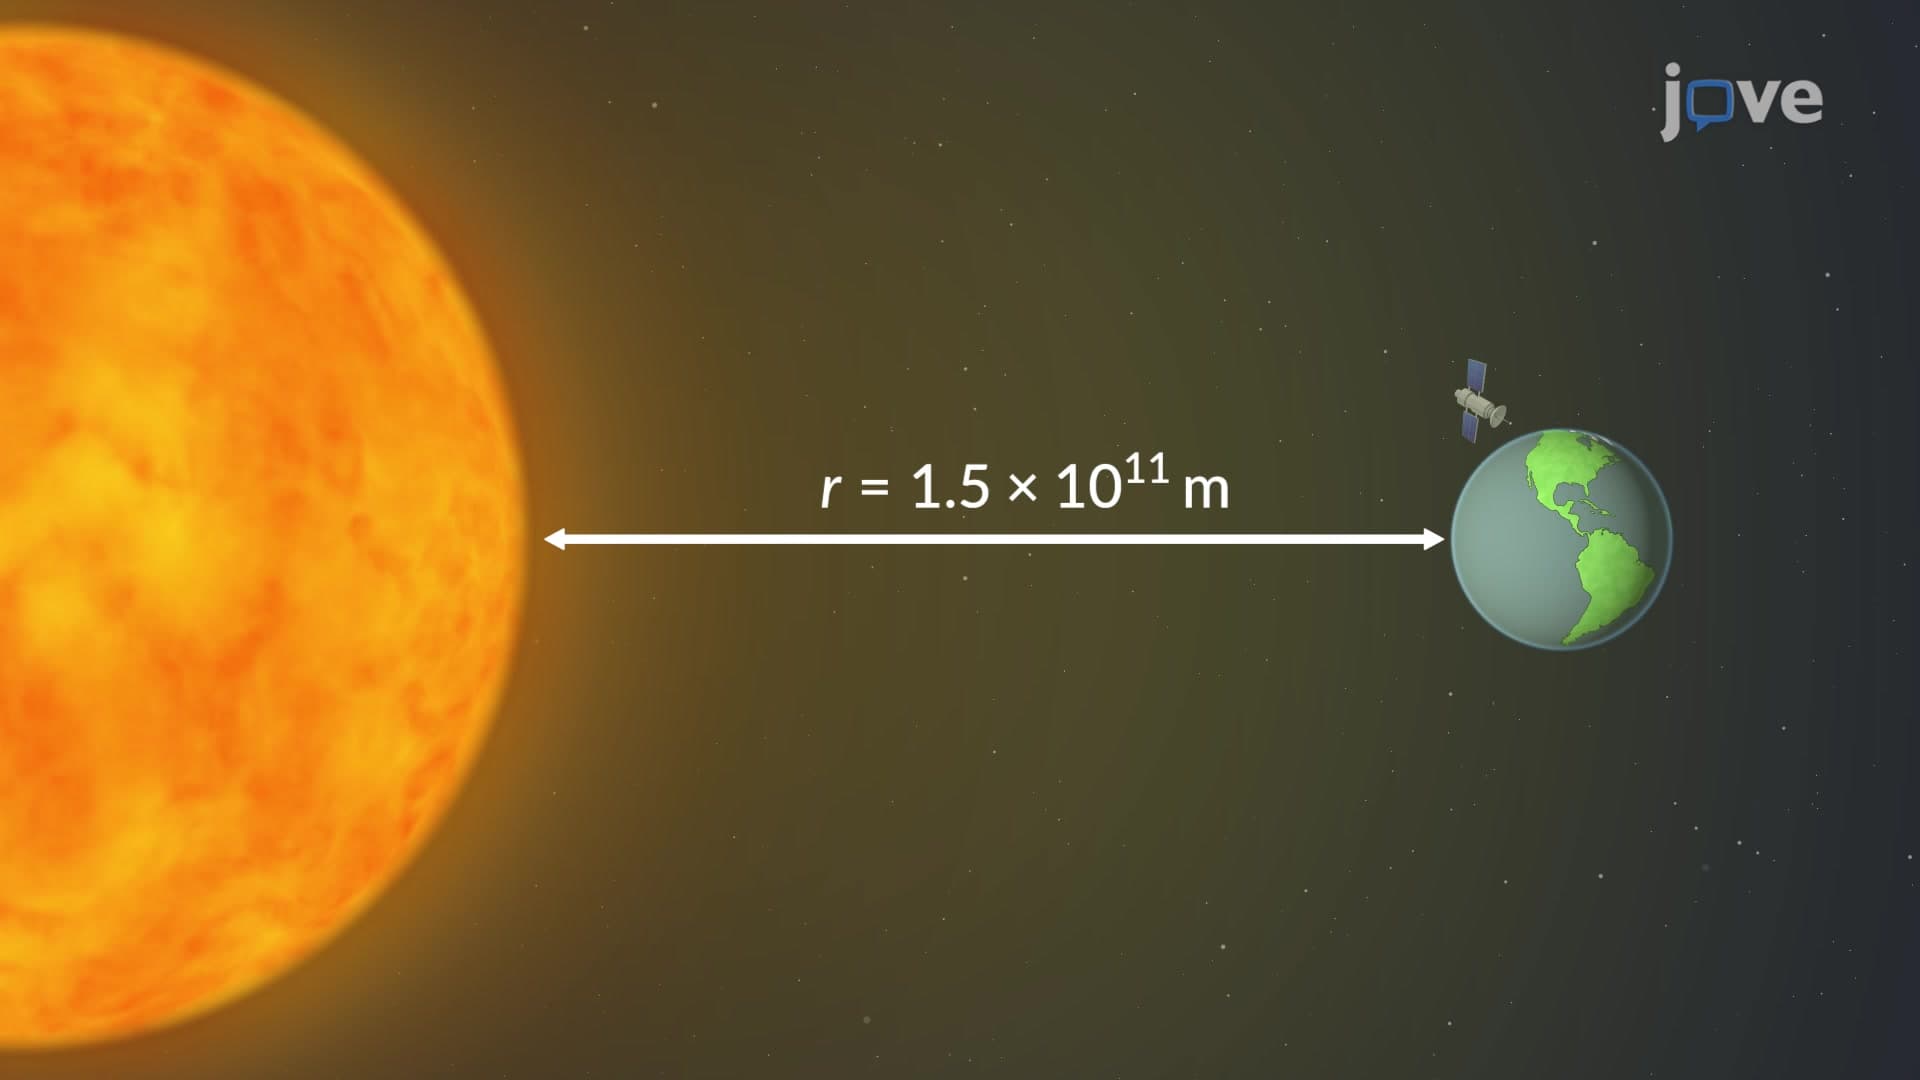
The average value of the rate of momentum transfer divided by the absorbing area represents the average force...