Related Experiment Video
Updated: Mar 15, 2026
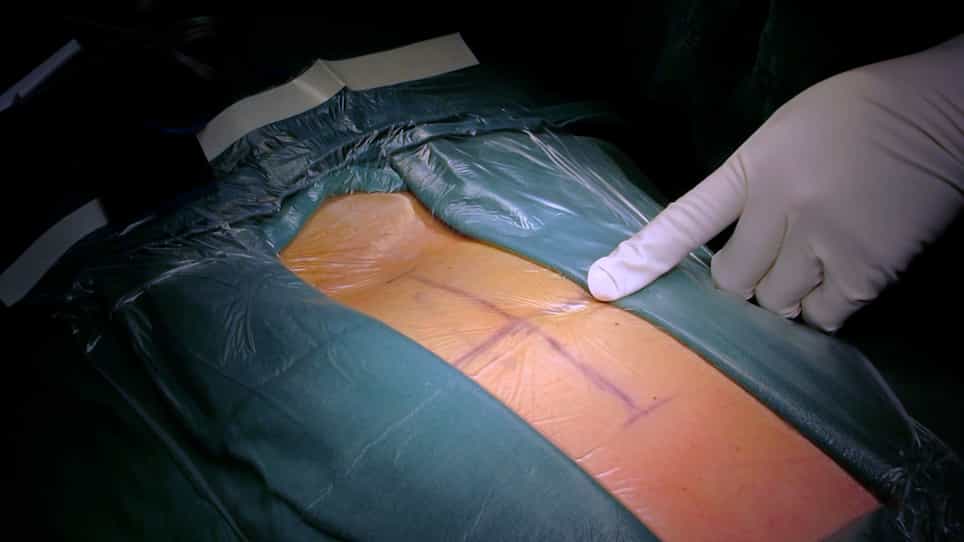

Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Necessary cervical kyphosis correction angle (NeckCA) for ideal alignment in cervical spinal deformity
Sun Woo Jang1, Hong Kyung Shin2, Sangjoon Chong2
11Department of Neurological Surgery, Gangneung Asan Hospital, University of Ulsan College of Medicine, Gangneung.

Objective:
The authors propose a formula to calculate the angle required for cervical kyphosis correction and validate its utility in achieving and maintaining optimal cervical alignment.
Methods:
The authors introduce a novel radiographic parameter, the necessary cervical kyphosis correction angle (NeckCA), defined as NeckCA = C2 slope (C2S) + center of gravity - T1 tilt (COG-T1 tilt) - 15. Using this formula, the authors retrospectively reviewed 29 cervical spinal deformity (CSD) correction surgical procedures performed at a single center from 2012 to 2024. Patients were categorized into two groups based on their radiological outcome: favorable (F group) and unfavorable (U group). The following criteria defined the U group: 1) T1 slope (T1S) - cervical lordosis (CL) > 25°; 2) C2-7 sagittal vertical axis (SVA) > 70 mm; or 3) segmental angle change > 10°. The authors compared clinical and radiological parameters between the groups and evaluated the discriminatory capacity of NeckCA using receiver operating characteristic (ROC) curve analysis.
Results:
Among the 29 patients (19 degenerative, 6 oncological, and 4 infectious etiologies), 17 were classified into the F group and 12 into the U group. Preoperative radiological parameters such as CL, C2S, and segmental angle did not differ significantly between groups, except for C2-7 SVA, which was much greater in the U group. ROC curve analysis showed that NeckCA served as a critical predictor of radiological outcomes, with an area under the curve of 0.806 (p = 0.006).
Conclusions:
In CSD correction, increasing CL alone to meet a T1S - CL < 15° often results in compensatory increases in T1S, leading to undercorrection. To counteract this, preoperative planning should include an additional corrective angle represented by the COG-T1. The authors' analysis of 29 cases confirms the use of NeckCA as a practical and predictive parameter for achieving optimal cervical alignment.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 07:01
Clinical Efficacy of Ultrasound-Assisted Scoliosis-Specific Exercise in Mild-Grade Adolescent Idiopathic Scoliosis
Published on: December 2, 2025
Related Concept Videos
 01:16
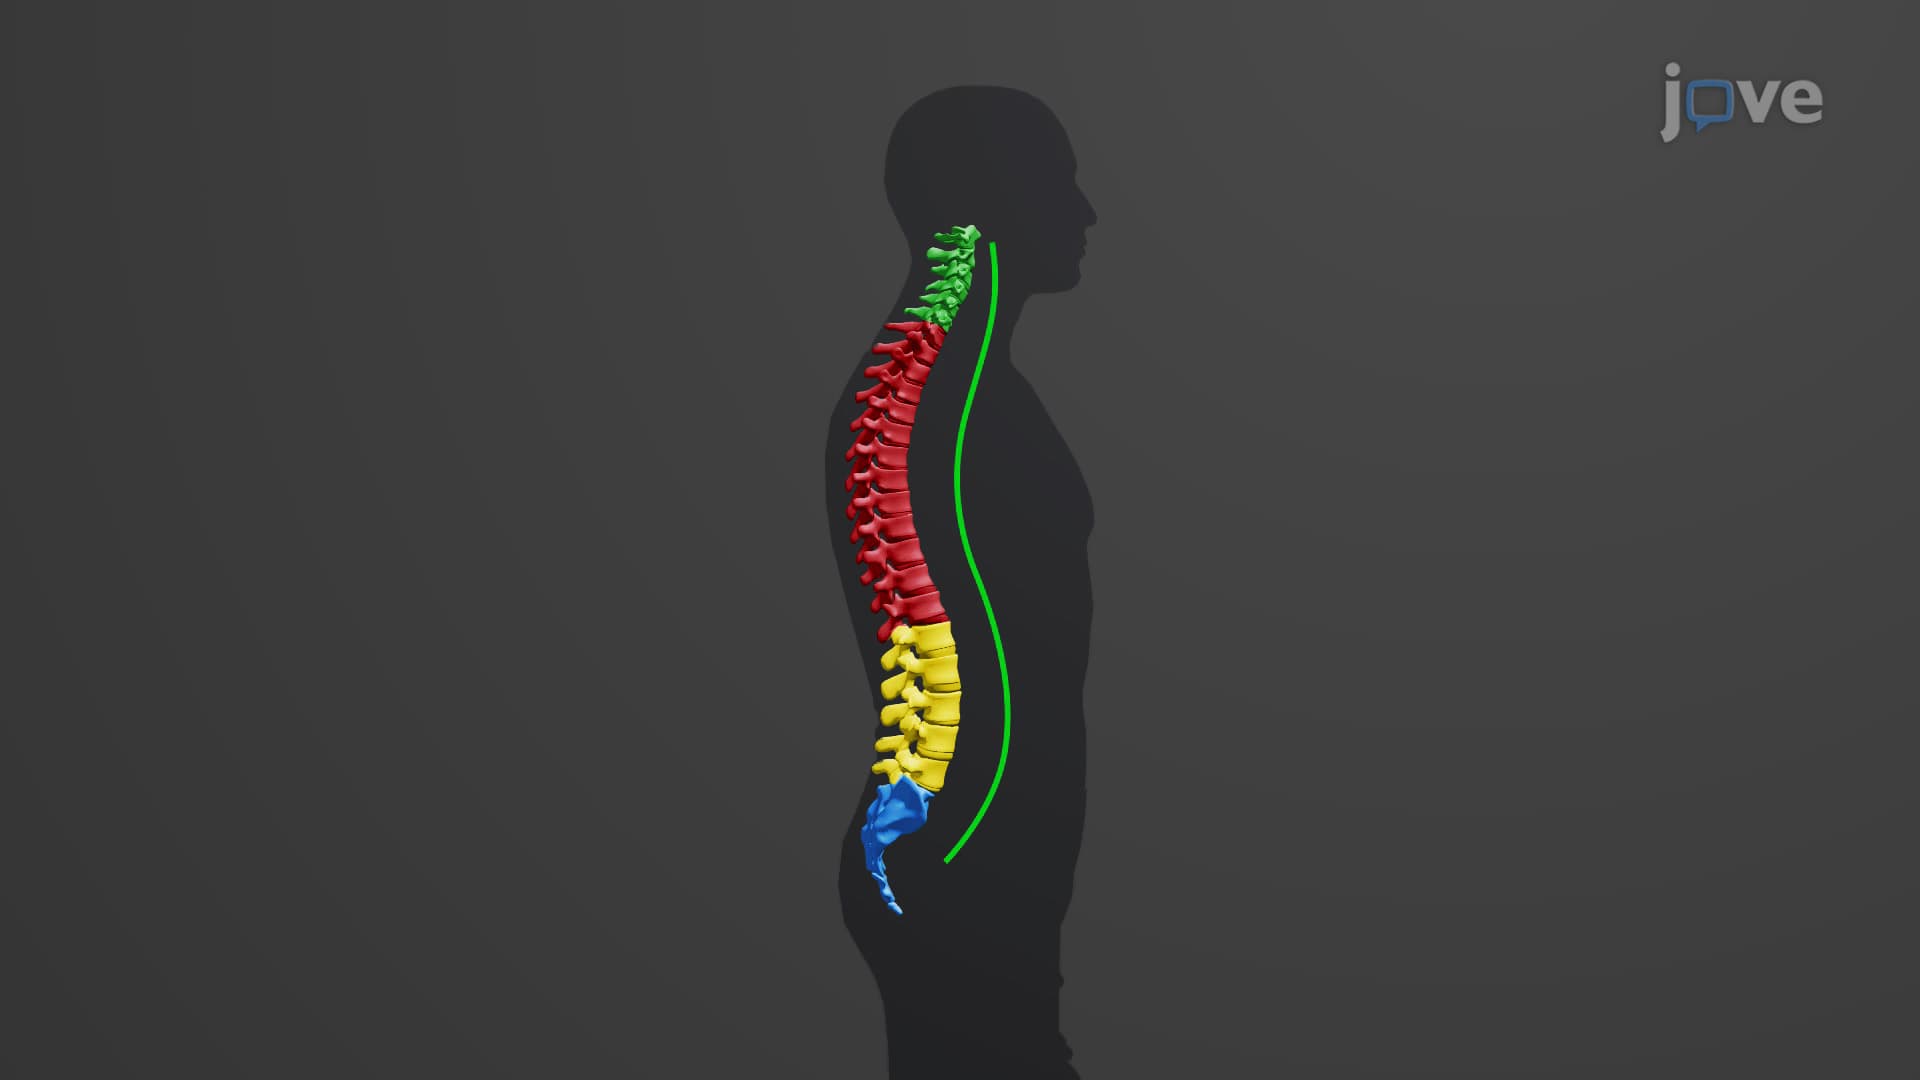
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:15
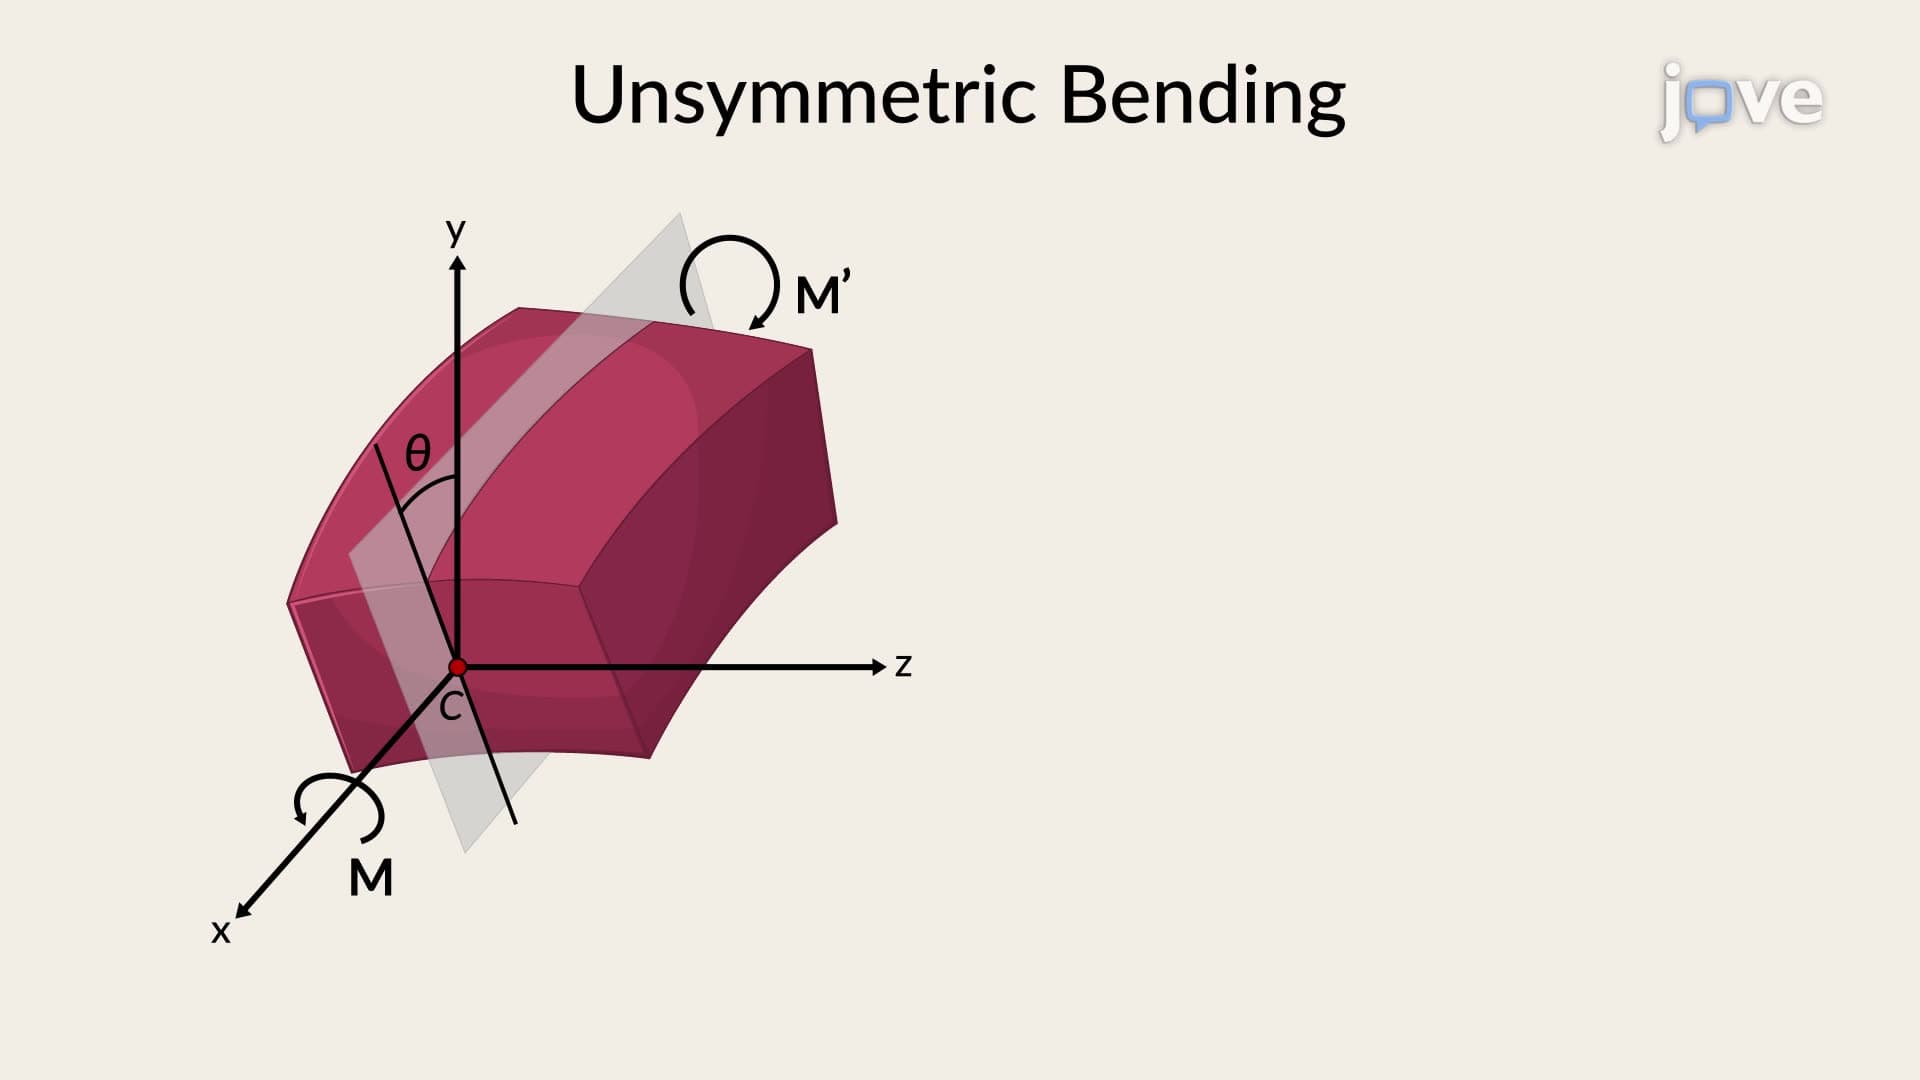
Unsymmetric Bending - Angle of Neutral Axis
When a bending moment is applied at an angle θ concerning the vertical axis of a symmetrical member, it can be resolved into components along the member's principal...
 01:18
Deformations in a Symmetric Member in Bending
When the member is segmented into tiny cubic elements, it is observed that the primary stress...