[Latent class analysis of ICU-acquired weakness in mechanically ventilated patients and its influencing factors]
Related Experiment Video
Updated: Mar 17, 2026
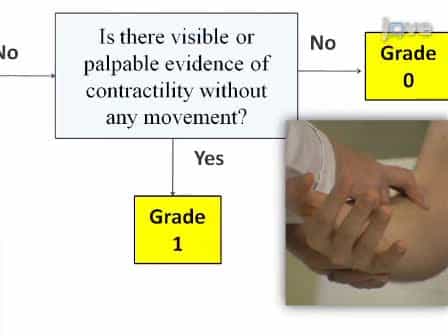
Manual Muscle Testing: A Method of Measuring Extremity Muscle Strength Applied to Critically Ill Patients
Published on: April 12, 2011
Jiayue Zhang1,2, Zhijie Du1, Jianxiang Wang1
1Department of ICU, the First People's Hospital of Kunming, Kunming 650051, China.

Objective:
To apply latent class analysis (LCA) to explore the latent classes of ICU-acquired weakness (ICU-AW) in mechanically ventilated patients and to analyze their influencing factors.
Methods:
A prospective observational study was conducted. From June 2024 to April 2025, 360 mechanically ventilated patients admitted to the intensive care unit (ICU) of the First People's Hospital of Kunming were enrolled. Consciousness was assessed using the Richmond Agitation-Sedation Scale (RASS). Muscle strength of six muscle groups (shoulder abductors, elbow flexors, wrist extensors, hip flexors, knee extensors, and ankle dorsiflexors) was evaluated using the Medical Research Council (MRC) score across, with a total score<48 indicating ICU-AW. Clinical data were collected via a self-designed ICU-AW risk factor scale, covering 21 items: demographic characteristics (gender, age), clinical interventions (total length of ICU stay, norepinephrine use or not, mechanical ventilation duration, immobilization time, neuromuscular blocker use duration, sedative/analgesic use or not, pre-ICU mechanical ventilation duration, invasive blood pressure monitoring or not, aminoglycoside use or not), underlying diseases and complications [combined with multiple organ dysfunction syndrome (MODS) or not, combined with sepsis or not, diabetes or not, hypertension or not, Acute Physiology And Chronic Health Evaluation II (APACHE II) score], and laboratory indicators (blood oxygen saturation, calcium, albumin, lactic acid, glucose). LCA was used to optimize the number of classes. The optimal model was selected based on the minimization of Akaike information criterion (AIC), Bayesian information criterion (BIC), and adjusted Bayesian information criterion (aBIC), an entropy value > 0.8, and significant results from the Lo-Mendell-Rubin test and the Bootstrap likelihood ratio test. Patients were classified and named based on LCA results. Univariate analysis and unordered multivariate Logistic regression analysis were used to identify influencing factors of latent class of ICU-AW in mechanically ventilated patients.
Results:
After deleting entries with missing values for both total length of ICU stay and pre-ICU mechanical ventilation duration exceeding 50%, latent class modeling was ultimately performed based on 19 risk factor variables. The results showed that when the number of classes was 3, AIC (9 179), BIC (9 455), and aBIC (9 467) were all superior to other class numbers, achieving a better balance between goodness of fit and complexity. Additionally, the entropy value (0.937) was higher than that of other class numbers, indicating the highest classification accuracy. Therefore, the final number of classes was determined to be 3. Based on the conditional probability distribution of risk factors for ICU-AW patients, combined with the clinical significance of the variables, the three potential categories were named as follows: treatment intensity-dominant type (characterized by mechanical ventilation duration>7 days, norepinephrine dependence, and invasive procedures), metabolic disorder-dominant type (characterized by hyperglycemia, hypocalcemia, and sepsis combined with metabolic diseases), and organ failure-related type (characterized by high APACHE II score, multiple organ dysfunction, and prolonged immobilization). Based on the number of ICU-AW categories and their characteristics determined by LCA, 360 patients undergoing mechanical ventilation were categorized into three potential ICU-AW categories. Among them, 234 (65.0%) were treatment intensity-dominant type, 26 (7.2%) were metabolic disorder-dominant type, and 100 (27.8%) were organ failure-related type. Univariate analysis showed significant differences among the three classes in gender, age, mechanical ventilation duration, neuromuscular blocker use duration, combined with sepsis or not, and APACHE II score (all P<0.05). Unordered multivariate Logistic regression indicated that patients who were male, had a long duration of mechanical ventilation, and a long duration of neuromuscular blocking agent use were more likely to be classified as treatment intensity-dominant type or metabolic disorder-dominant type. Combined with sepsis was more strongly associated with treatment intensity-dominant type.
Conclusions:
LCA identified three heterogeneous latent classes of ICU-AW in mechanically ventilated patients named treatment intensity-dominant type, metabolic disorder-dominant type, and organ failure-dominant type. Gender, mechanical ventilation duration, neuromuscular blocker use duration, and combined with sepsis or not were independent predictors of subtype stratification.
More Related Videos
Related Concept Videos
 01:30
Acute Respiratory Failure-III
 01:23
Acute Respiratory Failure-IV
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Pneumonia III: Complications and Assessment
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: