Related Experiment Video
Updated: Mar 17, 2026

Rapid Viscoelastic Characterization of Airway Mucus Using a Benchtop Rheometer
Published on: April 21, 2022
Mucus and inflammation in the HEMT Era: Persistent barriers to complete airway normalization in cystic fibrosis
Camille Ehre1, Marcus A Mall2, Gerard N McElvaney3
1Department of Pediatrics, University of North Carolina at Chapel Hill, Chapel Hill, NC, USA; Marsico Lung Institute, University of North Carolina at Chapel Hill, Chapel Hill, NC, USA; Department of Microbiology and Immunology, University of North Carolina at Chapel Hill, Chapel Hill, NC, USA.

Abstract:
Cystic fibrosis (CF) is an epithelial ion transport disorder that dehydrates the airway surface, concentrates mucus, and disrupts mucociliary clearance (MCC). Beyond reduced chloride/bicarbonate secretion and elevated ENaC activity, shifts in the composition, structure, and packaging of the gel-forming mucins MUC5AC and MUC5B reshape mucus viscoelasticity and adhesion, promoting stasis, infection, and inflammation. We synthesize mechanistic advances showing how CFTR dysfunction and microenvironmental cues, particularly epithelial hypoxia with HIF-driven ENaC activation and IL-1 cytokine signaling, reinforce hyperconcentration, alter MUC5AC/MUC5B balance, impede submucosal gland discharge, and foster a self-perpetuating cycle of protease-rich inflammation. Highly effective CFTR modulator therapies, such as elexacaftor/tezacaftor/ivacaftor, improve hydration, MCC, and inflammation; however, residual rheologic abnormalities, inflammation, persistent or recurrent infection, and regional heterogeneity are common, indicating that CFTR restoration alone does not uniformly normalize the airway milieu. We highlight methodological advances that enable quantitative, surface-level readouts in patient-derived air-liquid-interface cultures (e.g., FRAP and magnetic micro-wire rheology) linking thin-layer mucus viscosity, network mechanics, and transport to cellular physiology. Integrating these assays with clinical measures (e.g., MCC, segmental pathogen and protease burden) supports a comprehensive model in which CFTR loss initiates mucus hyperconcentration that is subsequently enhanced by mucin entanglement/interactions and hypoxia-inflammatory feedback. Finally, we propose an integrated therapeutic framework that pairs CFTR correction with mechanism-guided, mucus-targeted interventions and data-driven anti-infective/anti-inflammatory strategies to optimize personalized treatment approaches.
More Related Videos
 06:57
The WinCF Model - An Inexpensive and Tractable Microcosm of a Mucus Plugged Bronchiole to Study the Microbiology of Lung Infections
Published on: May 8, 2017
 10:18
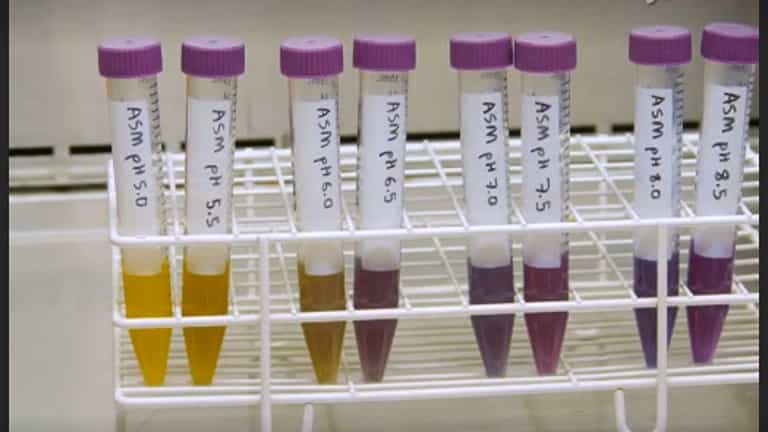
Real-Time, Semi-Automated Fluorescent Measurement of the Airway Surface Liquid pH of Primary Human Airway Epithelial Cells
Published on: June 13, 2019
Related Concept Videos
 01:24
Cystic Fibrosis: Management
Sinus disease and chronic...
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation,...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:16
Drugs Used in Upper Respiratory Disorders: Overview
Antihistamines (e.g., Benadryl) block histamines from binding. Histamines are chemicals released during an allergic reaction in the body. As a...
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:30
Chronic Obstructive Pulmonary Disease-V: Nursing Management
Assessment